Related Experiment Video
Updated: Mar 26, 2026


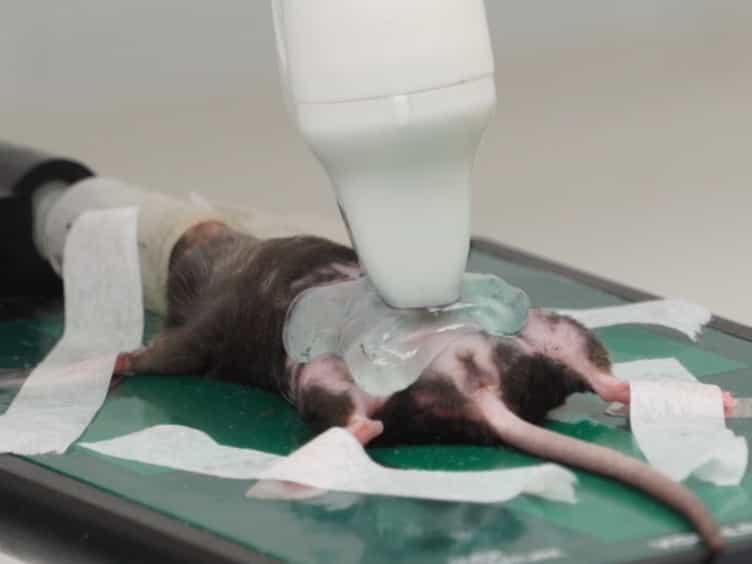
Fetal Echocardiography and Pulsed-wave Doppler Ultrasound in a Rabbit Model of Intrauterine Growth Restriction
Published on: June 29, 2013
First-trimester screening with specific algorithms for early- and late-onset fetal growth restriction
F Crovetto1,2, S Triunfo1, F Crispi1
1BCNatal - Barcelona Center for Maternal-Fetal and Neonatal Medicine (Hospital Clínic and Hospital Sant Joan de Deu), IDIBAPS, University of Barcelona, and Centre for Biomedical Research on Rare Diseases (CIBER-ER), Barcelona, Spain.

Insights
This study developed distinct first-trimester screening algorithms for early and late fetal growth restriction (FGR). Tailored prediction models improve early detection of FGR, enhancing prenatal care.
Area of Science:
- Obstetrics and Gynecology
- Maternal-Fetal Medicine
- Diagnostic Ultrasound
Background:
- Fetal growth restriction (FGR) is a major cause of perinatal morbidity and mortality.
- Current first-trimester screening methods for FGR lack optimal predictive accuracy.
- Developing distinct algorithms for early and late FGR is crucial for timely intervention.
Purpose of the Study:
- To create optimized first-trimester prediction algorithms for early and late fetal growth restriction (FGR).
- To evaluate the efficacy of maternal characteristics, mean arterial pressure (MAP), uterine artery pulsatility index (UtA-PI), placental growth factor (PlGF), and soluble fms-like tyrosine kinase-1 (sFlt-1) in FGR prediction.
Main Methods:
- A prospective cohort study involving 9150 singleton pregnancies undergoing first-trimester screening.
- FGR defined by ultrasound-estimated fetal weight <10th percentile with Doppler abnormalities or birth weight <3rd percentile.
- Logistic regression models incorporating maternal factors, MAP, UtA-PI, PlGF, and sFlt-1 were developed.
Main Results:
- Early FGR (0.6%) prediction model achieved 86.4% detection rate (DR) at 10% false-positive rate (FPR) (AUC: 0.93).
- Late FGR (4.4%) prediction model achieved 65.8% DR at 10% FPR (AUC: 0.76).
- Prediction accuracy varied for FGR with and without pre-eclampsia (PE) for both early and late FGR.
Conclusions:
- Distinct screening algorithms are optimal for early versus late fetal growth restriction.
- Separate screening approaches for early and late FGR support clinical differentiation and management.
- These findings can inform the development of more effective first-trimester FGR screening protocols.
Objective:
To develop optimal first-trimester algorithms for the prediction of early and late fetal growth restriction (FGR).
Methods:
This was a prospective cohort study of singleton pregnancies undergoing first-trimester screening. FGR was defined as an ultrasound estimated fetal weight < 10(th) percentile plus Doppler abnormalities or a birth weight < 3(rd) percentile. Logistic regression-based predictive models were developed for predicting early and late FGR (cut-off: delivery at 34 weeks). The model included the a-priori risk (maternal characteristics), mean arterial pressure (MAP), uterine artery pulsatility index (UtA-PI), placental growth factor (PlGF) and soluble fms-like tyrosine kinase-1 (sFlt-1).
Results:
Of the 9150 pregnancies included, 462 (5%) fetuses were growth restricted: 59 (0.6%) early and 403 (4.4%) late. Significant contributions to the prediction of early FGR were provided by black ethnicity, chronic hypertension, previous FGR, MAP, UtA-PI, PlGF and sFlt-1. The model achieved an overall detection rate (DR) of 86.4% for a 10% false-positive rate (area under the receiver-operating characteristics curve (AUC): 0.93 (95% CI, 0.87-0.98)). The DR was 94.7% for FGR with pre-eclampsia (PE) (64% of cases) and 71.4% for FGR without PE (36% of cases). For late FGR, significant contributions were provided by chronic hypertension, autoimmune disease, previous FGR, smoking status, nulliparity, MAP, UtA-PI, PlGF and sFlt-1. The model achieved a DR of 65.8% for a 10% false-positive rate (AUC: 0.76 (95% CI, 0.73-0.80)). The DR was 70.2% for FGR with PE (12% of cases) and 63.5% for FGR without PE (88% of cases).
Conclusions:
The optimal screening algorithm was different for early vs late FGR, supporting the concept that screening for FGR is better performed separately for the two clinical forms. Copyright © 2016 ISUOG. Published by John Wiley & Sons Ltd.