Related Experiment Video
Updated: Mar 26, 2026
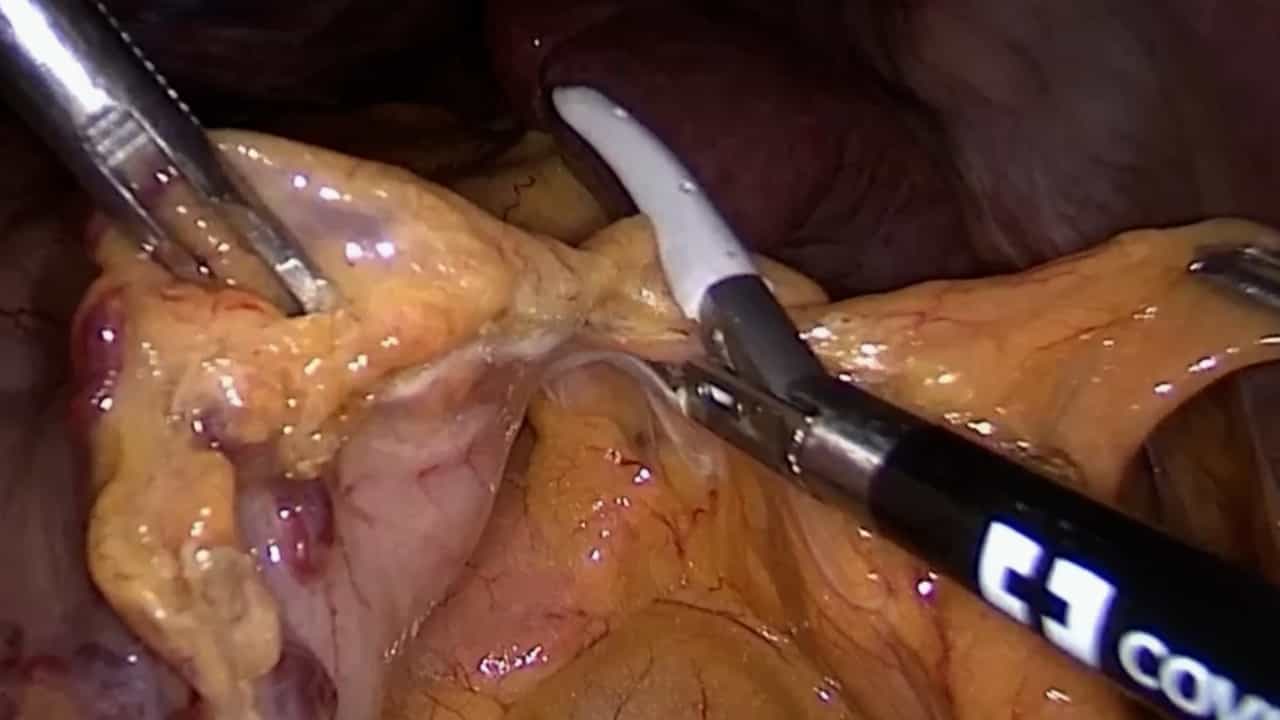

Application of Laparoscopic Partial Splenectomy with Total Blood Flow Occlusion in Benign Splenic Lesions
Published on: December 20, 2024
Nonoperative management of splenic injuries: significance of age
Adrian W Ong1, Kirsten E Eilertson2, Eugene F Reilly1
1Department of Surgery, Section of Trauma, Reading Hospital and the University of Pennsylvania Perelman School of Medicine, Reading, Pennsylvania.

Insights
Age increases the risk of failure in nonoperative management (NOM) for blunt splenic injuries (BSI). This effect is most significant in older patients with severe injuries, highlighting the need for further research into NOM success factors for this demographic.
Area of Science:
- Trauma Surgery
- Emergency Medicine
- Surgical Outcomes
Background:
- Nonoperative management (NOM) is a common approach for blunt splenic injuries (BSI).
- The impact of patient age on the success of NOM for BSI has not been extensively investigated.
Purpose of the Study:
- To evaluate age as a risk factor for failure in the nonoperative management of blunt splenic injuries.
- To determine the relationship between patient age, injury severity, and NOM outcomes.
Main Methods:
- Analysis of the 2011 National Trauma Data Bank data set.
- Stratification of patients by age (13-54, 55-74, ≥75 years) and BSI severity (AIS 1-2, 3, ≥4).
- Utilized a semiparametric proportional odds model to assess NOM outcomes.
Main Results:
- 15.3% of patients failed NOM.
- Failure odds increased by 1.014 for each year of age and 1.5 for older age groups.
- Higher BSI severity (AIS 3 and ≥4) significantly increased failure odds (3.9x and 13x, respectively).
- Age's impact was most pronounced in older patients with high-grade BSI, showing >50% failure rates.
- Both age and NOM failure independently predicted mortality.
Conclusions:
- Age is a significant factor associated with NOM failure in BSI.
- The clinical relevance of age is most pronounced in high-grade blunt splenic injuries.
- Further research is needed to identify factors influencing NOM success in elderly patients with severe BSI.
Background:
In the nonoperative management (NOM) of blunt splenic injuries (BSI), the clinical relevance of age as a risk factor has not been well studied.
Methods:
Using the 2011 National Trauma Data Bank data set, age was analyzed both as a continuous variable and a categorical variable (group 1 [13-54 y], group 2 [55-74 y], and group 3 [≥75 y]). BSI severity was stratified by abbreviated injury scale (AIS): group 1 (AIS ≤2), group 2 (AIS 3), and group 3 (AIS ≥4). A semiparametric proportional odds model was used to model NOM outcomes and effects due to age and BSI severity.
Results:
Of 15,113 subjects, 15.3% failed NOM. The odds of failure increased by a factor of 1.014 for each year of age, or factor of 1.5 for groups 2 and 3 each. BSI severity groups 2 and 3 had increases in the odds of failure by factors of 3.9 and 13, respectively, compared with those of group 1. Most failures occurred by 48 h irrespective of age. The effect of age was most pronounced in age groups 2 and 3 with the most severe BSI, where a NOM failure rate of >50% was seen. Both age and failure of NOM were independent predictors of mortality.
Conclusions:
Age is associated with failure of NOM but its effect seems more clinically relevant only in high-grade BSI. Factors that could influence NOM success in elderly patients with high-grade injuries deserve further study.

Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:22
Aneurysm IV: Nursing Management
 01:26
Aneurysm III: Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: