Related Experiment Video
Updated: Aug 14, 2026
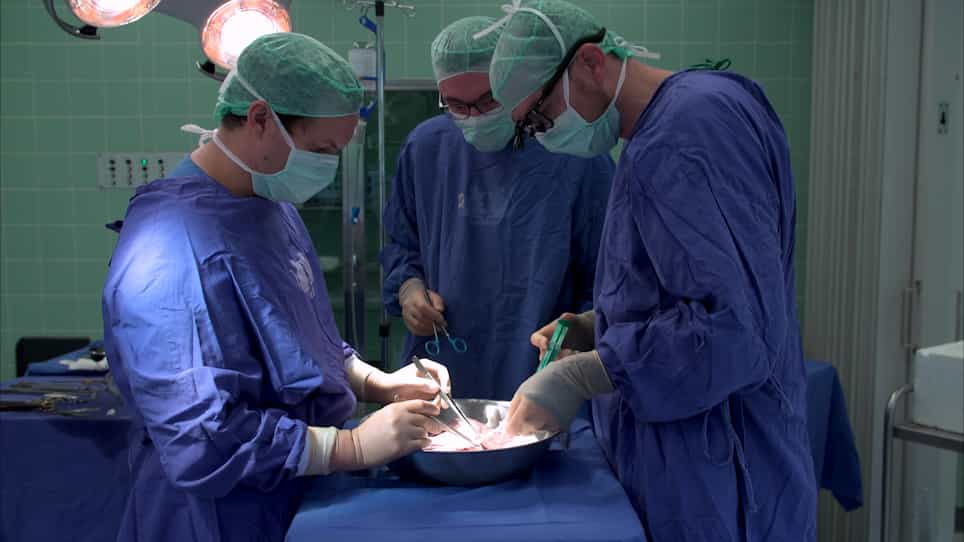
Technique of Porcine Liver Procurement and Orthotopic Transplantation using an Active Porto-Caval Shunt
Published on: May 7, 2015
Arrhythmogenic potential develops rapidly at graft reperfusion before the start of hypotension during living-donor
Hwa-Mi Lee1, Soo-Kyoung Park2, Young-Jin Moon3
1Department of Anesthesiology and Pain Medicine, Laboratory for Cardiovascular Dynamics, Asan Medical Center, University of Ulsan College of Medicine, Seoul, Korea.; Department of Anesthesiology and Pain Medicine, Gangneung Asan Hospital, University of Ulsan College of Medicine, Gangneung, Korea.

Background:
Detailed profiles of acute hypothermia and electrocardiographic (ECG) manifestations of arrhythmogenicity were examined to analyze acute hypothermia and ventricular arrhythmogenic potential immediately after portal vein unclamping (PVU) in living-donor liver transplantation (LT).
Methods:
We retrospectively analyzed electronically archived medical records (n = 148) of beat-to-beat ECG, arterial pressure waveforms, and blood temperature (BT) from Swan-Ganz catheters in patients undergoing living-donor LT. The ECG data analyzed were selected from the start of BT drop to the initiation of systolic hypotension after PVU.
Results:
On reperfusion, acute hypothermia of < 34℃, < 33℃ and < 32℃ developed in 75.0%, 37.2% and 11.5% of patients, respectively. BT decreased from 35.0℃ ± 0.8℃ to 33.3℃ ± 1.0℃ (range 35.8℃-30.5℃). The median time to nadir of BT was 10 s after PVU. Difference in BT (ΔBT) was weakly correlated with graft-recipient weight ratio (GRWR; r = 0.22, P = 0.008). Compared to baseline, arrhythmogenicity indices such as corrected QT (QTc), Tp-e (T wave peak to end) interval, and Tp-e/QTc ratio were prolonged (P < 0.001 each). ST height decreased and T amplitude increased (P < 0.001 each). However, no correlation was found between ΔBT and arrhythmogenic indices.
Conclusions:
In living-donor LT, regardless of extent of BT drop, ventricular arrhythmogenic potential developed immediately after PVU prior to occurrence of systolic hypotension.