Related Experiment Video
Updated: Mar 25, 2026


Mouse Model of Surgical Uterine Injury and Subsequent Pregnancy Outcomes
Published on: June 27, 2025
A Rare Cause of Placental Abruption: Uterine Torsion
Ipek Ulu1, Muhammed Siraç Güneş1, Gürkan Kiran1
1Faculty, Department of Obstetrics and Gynecology, Ümraniye Medical and Research Hospital , Istanbul, Turkey .

Uterine torsion is defined as a rotation on its long axis and it is a dangerous, unexpected obstetric emergency. We report a case of uterine torsion at 32 weeks of gestation in a singleton pregnancy. A 37-year-old woman with multiple prior cesarean deliveries referred to emergency unit of our hospital at 32 weeks of gestation with severe abdominal pain and mild vaginal bleeding. Ultrasonography showed a single fetus in vertex position, with a normal amniotic fluid. Fetal biometer was appropriate for 32 weeks of gestation. Placental location was anterior with a subchorionic hypoechogenic small area which was suspected to be a sign of placental abruption. An emergency cesarean section was performed under general anesthesia. The 180° uterine torsion was diagnosed and it was not possible to perform detorsion of the gravid uterus by exteriorization by pfannenstiel incision. Posterior hysterotomy was performed and a male baby of 1830 grams weight was delivered. The newborn was transported to Neonatal Intensive Care Unit (NICU) of another hospital and discharged within two weeks. Patient recovered well and was discharged on second postoperation day. Uterine torsion is a very rare and life threatening situation. In unexpected cases posterior low transuerse hysterotomy is generally performed and it is suggested as a safe choice when detorsion was not accomplished. It is not easy to keep in mind the possibility of uterine torsion in cases of abdominal pain during pregnancy. Because it generally causes abruption, management of abruption is vitally important to prevent fetal mortality.
Uterine torsion is defined as a rotation on its long axis and it is a dangerous, unexpected obstetric emergency. We report a case of uterine torsion at 32 weeks of gestation in a singleton pregnancy. A 37-year-old woman with multiple prior cesarean deliveries referred to emergency unit of our hospital at 32 weeks of gestation with severe abdominal pain and mild vaginal bleeding. Ultrasonography showed a single fetus in vertex position, with a normal amniotic fluid. Fetal biometer was appropriate for 32 weeks of gestation. Placental location was anterior with a subchorionic hypoechogenic small area which was suspected to be a sign of placental abruption. An emergency cesarean section was performed under general anesthesia. The 180° uterine torsion was diagnosed and it was not possible to perform detorsion of the gravid uterus by exteriorization by pfannenstiel incision. Posterior hysterotomy was performed and a male baby of 1830 grams weight was delivered. The newborn was transported to Neonatal Intensive Care Unit (NICU) of another hospital and discharged within two weeks. Patient recovered well and was discharged on second postoperation day. Uterine torsion is a very rare and life threatening situation. In unexpected cases posterior low transuerse hysterotomy is generally performed and it is suggested as a safe choice when detorsion was not accomplished. It is not easy to keep in mind the possibility of uterine torsion in cases of abdominal pain during pregnancy. Because it generally causes abruption, management of abruption is vitally important to prevent fetal mortality.


Related Concept Videos
 01:07
Teratogenicity
 01:18
Uterus and Cervix
The uterus is securely anchored within the pelvic cavity by paired broad ligaments on either side. It is further stabilized by three pairs...
 01:16
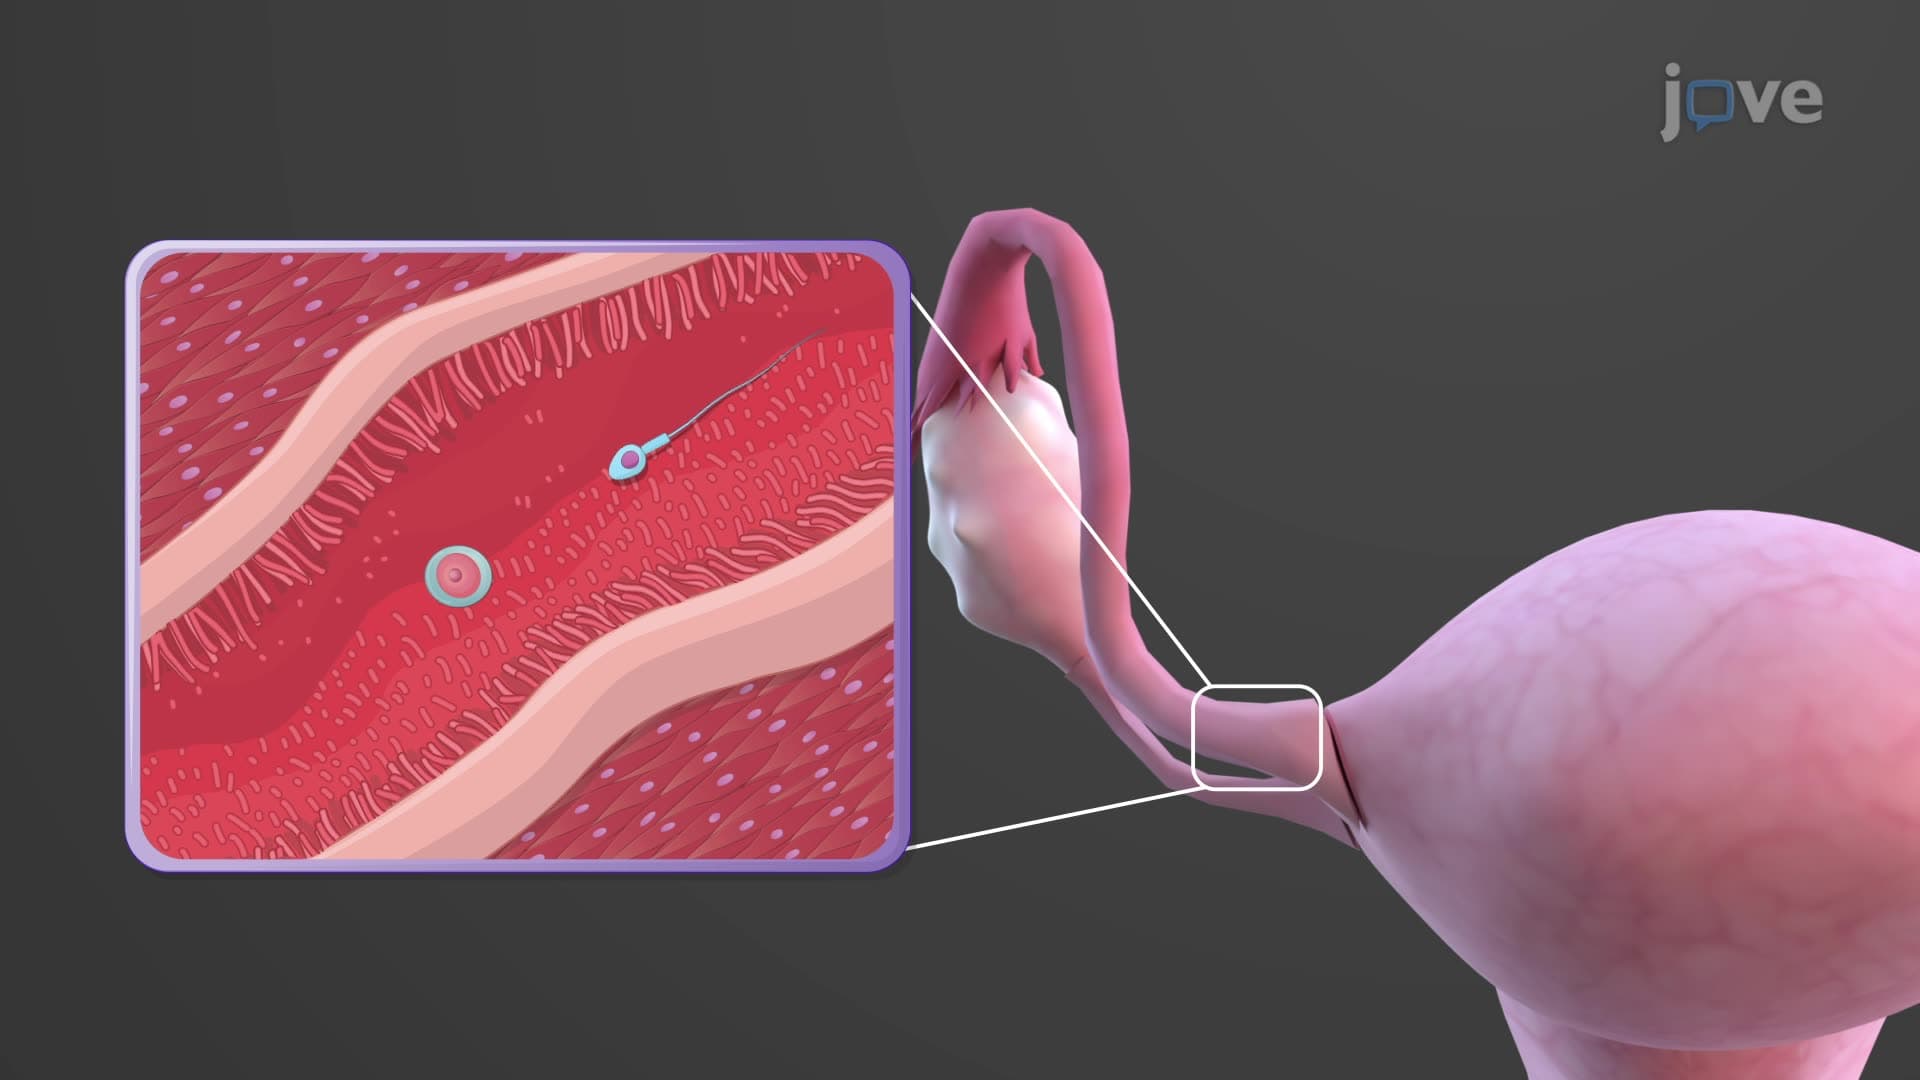
Uterine Tubes
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...