Related Experiment Video
Updated: Mar 25, 2026
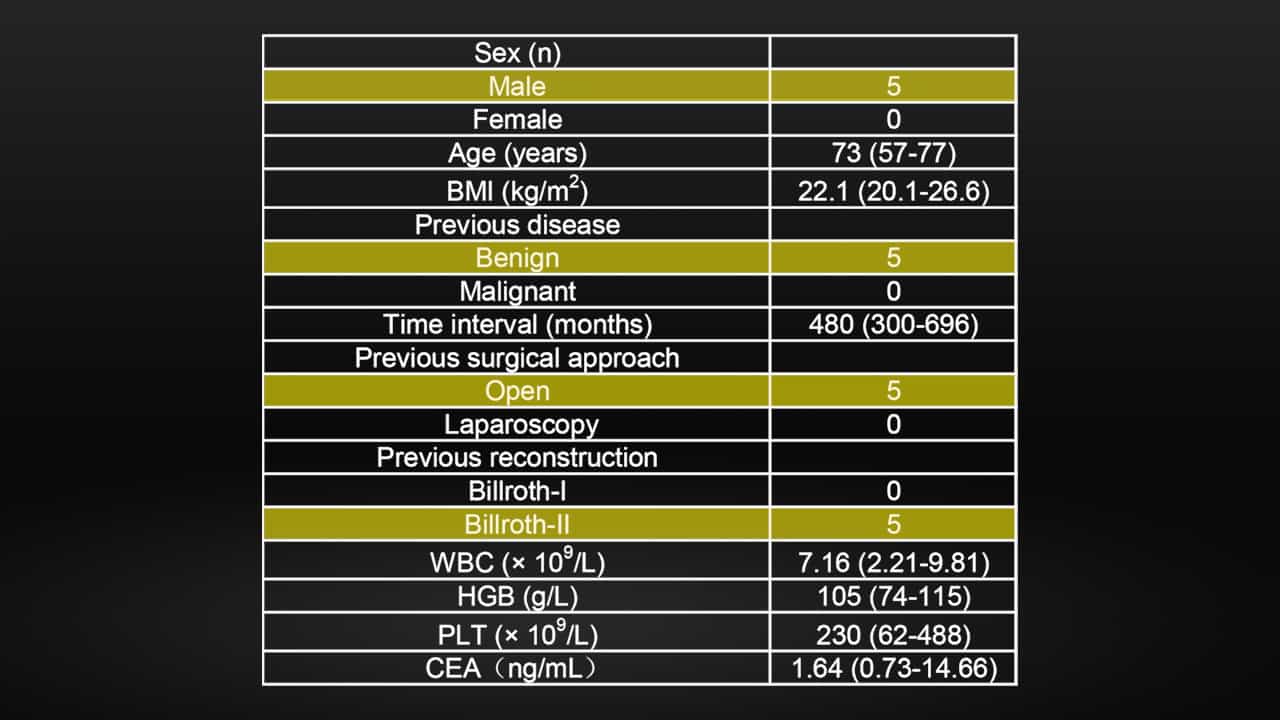

Laparoscopic Radical Gastrectomy for Remnant Gastric Cancer
Published on: October 31, 2025
Morbidity and Mortality of Laparoscopic Versus Open D2 Distal Gastrectomy for Advanced Gastric Cancer: A Randomized
Yanfeng Hu1, Changming Huang1, Yihong Sun1
1Yanfeng Hu, Hao Liu, Jiang Yu, and Guoxin Li, Nanfang Hospital, Southern Medical University; Hongbo Wei, The Third Affiliated Hospital of Sun Yat-Sen University; Pingyan Chen, Southern Medical University, Guangzhou; Changming Huang, Chaohui Zheng, and Ping Li, Fujian Medical University Union Hospital; Mingang Ying, Fujian Provincial Cancer Hospital, Fuzhou; Yihong Sun and Fenglin Liu, Zhongshan Hospital, Fudan University; Hui Cao and Gang Zhao, Renji Hospital, Shanghai Jiao Tong University School of Medicine; Weiguo Hu, Ruijin Hospital, Shanghai Jiao Tong University School of Medicine, Shanghai; Xiaohui Du, General Hospital of the People's Liberation Army; Xiangqian Su, Ziyu Li, and Jiadi Xing, Key Laboratory of Carcinogenesis and Translational Research (Ministry of Education), Peking University Cancer Hospital & Institute, Beijing; Jiankun Hu and Xinzu Chen, West China Hospital, Sichuan University, Chengdu; Yingwei Xue and Kuan Wang, The Affiliated Tumor Hospital of Harbin Medical University, Harbin; Jian Suo, The First Hospital, Jilin University, Changchun; Kaixiong Tao, Union Hospital, Tongji Medical College, Huazhong University of Science and Technology, Wuhan; and Xianli He, Tangdu Hospital, Fourth Military Medical University, Xi'an, China.

Purpose:
The safety and efficacy of radical laparoscopic distal gastrectomy (LG) with D2 lymphadenectomy for the treatment of advanced gastric cancer (AGC) remain controversial. We conducted a randomized controlled trial to compare laparoscopic and conventional open distal gastrectomy with D2 lymph node dissections for AGC.
Patients And Methods:
Between September 2012 and December 2014, 1,056 patients with clinical stage T2-4aN0-3M0 gastric cancer were eligible for inclusion. They were randomly assigned to either the LG with D2 lymphadenectomy group (n = 528) or the open gastrectomy (OG) with D2 lymphadenectomy group (n = 528). Fifteen experienced surgeons from 14 institutions in China participated in the study. The morbidity and mortality within 30 days after surgery between the LG (n = 519) and the OG (n = 520) groups were compared on the basis of the modified intention-to-treat principle. Postoperative complications were stratified according to the Clavien-Dindo classification.
Results:
The compliance rates of D2 lymphadenectomy were similar between the LG and OG groups (99.4% v 99.6%; P = .845). The postoperative morbidity was 15.2% in the LG group and 12.9% in OG group with no significant difference (difference, 2.3%; 95% CI, -1.9 to 6.6; P = .285). The mortality rate was 0.4% for the LG group and zero for the OG group (difference, 0.4%; 95% CI, -0.4 to 1.4; P = .249). The distribution of severity was similar between the two groups (P = .314).
Conclusion:
Experienced surgeons can safely perform LG with D2 lymphadenectomy for AGC.
More Related Videos
 03:32
Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
 10:31
Intraoperative Gastroscopy for Tumor Localization in Laparoscopic Surgery for Gastric Adenocarcinoma
Published on: August 9, 2016