Related Experiment Video
Updated: Mar 25, 2026
Transcorporal Artificial Urinary Sphincter Cuff Placement in a Case Requiring Revision for Urethral Atrophy
Published on: June 16, 2022
Laparoscopic implantation of artificial urinary sphincter: An option for treating recurrent female urinary
J V Baldissera-Aradas1, L Rodríguez-Villamil1, I González-Rodríguez1
1Departamento de Urología, Hospital de Cabueñes, Gijón, España.

Introduction:
The failure rate for anti-incontinence surgery ranges from 5% to 80%. There is not actual consensus on the use of artificial urinary sphincter (AUS) as treatment for recurrent urinary incontinence in women. Several authors have shown that AUS can be useful, if the intrinsic sphincteric deficiency is checked. We present the first case in Spain, to our knowledge, of laparoscopic implantation of AUS as treatment for female recurrent urinary incontinence.
Material And Methods:
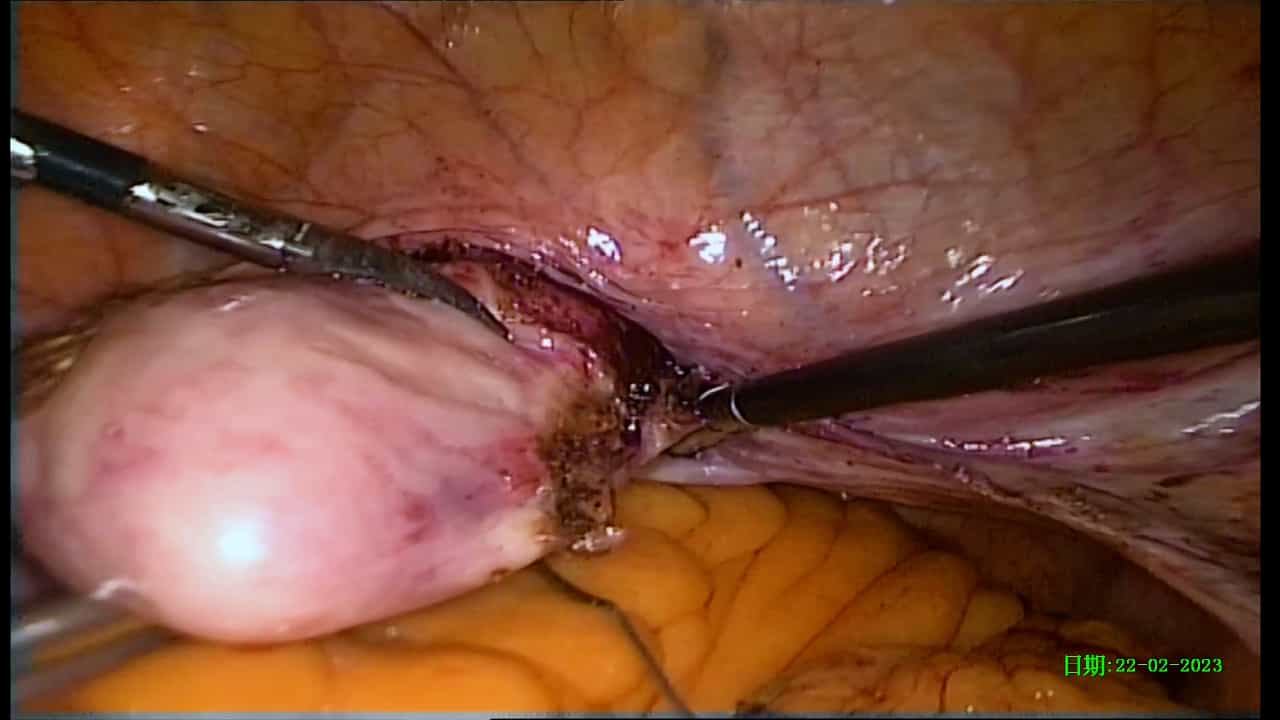
Under general anaesthesia, patient was placed in supine decubitus with slight Trendelenburg, access to the vagina was verified. Through a transperitoneal pelvic laparoscopic approach, Retzius space was opened and then the laterovaginal spaces up to the endopelvic fascia. To facilitate the dissection of the bladder neck, we inserted a swab into the vagina, performing simultaneous traction and countertraction manoeuvres. As an access port for the AUS, we widened the incision of the lower trocar. We adjusted the periurethral cuff and then placed the reservoir and the pump in the laterovesical space and the labia majora of the vulva, respectively. Lastly, we connected the 3 AUS elements and peritoneum was closed to isolate AUS from the intestine.
Results:
The surgical time was 92min, the estimated blood loss was <100cc(3) and the hospital stay was 48h. There were no intraoperative or postoperative complications. The AUS was activated at 6 weeks. At 24 months, patient managed the AUS adequately and total continence was achieved.
Conclusions:
Laparoscopic implantation of AUS is a feasible technique. Transvaginal traction and countertraction manoeuvres can prevent intraoperative lesions.

Related Concept Videos
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD: