Related Experiment Video
Updated: Mar 25, 2026

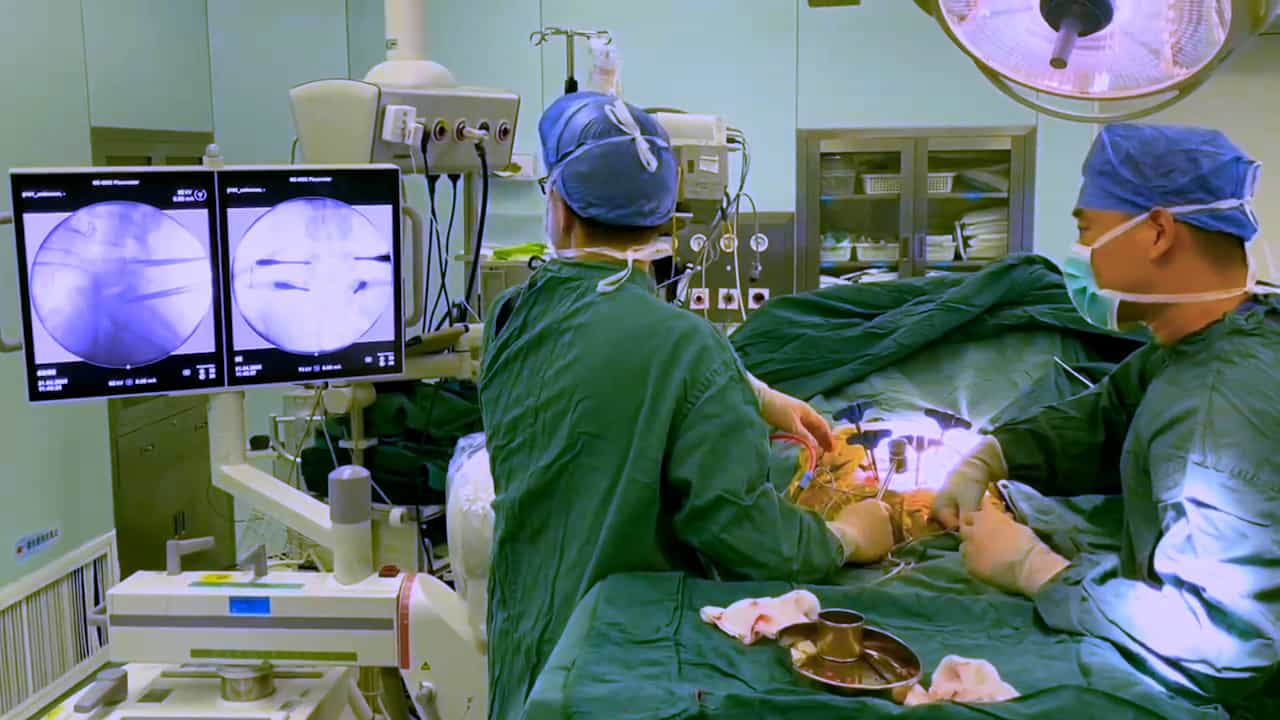
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
A comparison of three different surgical procedures in the treatment of type A thoracolumbar fractures: a randomized
Jianhua Lyu1, Kai Chen2, Zhaohui Tang2
1Department of Orthopaedics, The 92 Hospital of the People's Liberation Army, Nanping, Fujian Province, China.

Purpose:
The aim of the study was to evaluate the efficacy of three different surgical procedures in the treatment of type A thoracolumbar fractures.
Materials And Methods:
Between September 2012 and January 2015, a total of 90 patients with type A thoracolumbar fractures were randomly assigned into three groups of 30 each. Patients in group A, B, and C were treated with three-level percutaneous fixation, two-level percutaneous fixation, and three-level open fixation, respectively. Blood loss, duration of surgery, VAS scores, Cobb angles, and anterior height ratios of fractured vertebrae were collected for statistical analysis.
Results:
The average follow-up was 17.7 months. Post-operative Cobb angles were significantly corrected and anterior height ratios of fractured vertebrae were well restored in all three groups (p < 0.01). Back pain was efficiently relieved according to VAS score change (p < 0.01). There were significant differences in values of blood loss and post-operative VAS scores (at three months) between group A and group C (p < 0.01). No significant difference concerning post-operative anterior height ratios of fractured vertebrae, Cobb angles and correction losses was observed between group A and group B (p = 0.580, 0.840, 0.215, respectively).
Conclusion:
Percutaneous fixation not only provides the same reduction effect as open fixation, but also has an advantage of causing less operation related trauma which is beneficial to post-operative rehabilitation. The efficacy of three-level percutaneous fixation and two-level percutaneous fixation in the treatment of type A thoracolumbar fractures is not significantly different.