Related Experiment Video
Updated: Mar 25, 2026
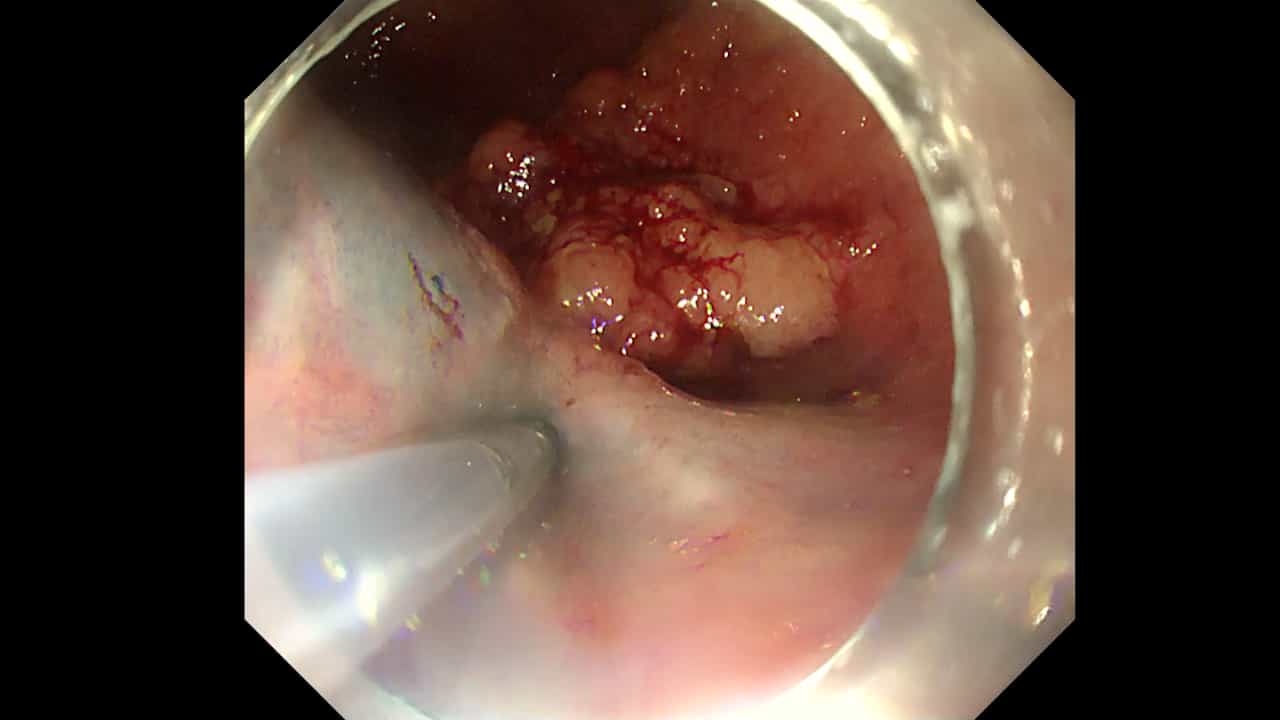

The Pocket-Creation Procedure of Endoscopic Submucosal Dissection for Large Rectal Laterally Spreading Tumors
Published on: February 13, 2026
Endoscopic predictors of deep submucosal invasion in colorectal laterally spreading tumors
Masayoshi Yamada1, Yutaka Saito1, Taku Sakamoto1
1Endoscopy Division, National Cancer Center Hospital, Tokyo, Japan.

Background And Study Aims:
The depth of invasion of the bowel wall influences the treatment of colorectal laterally spreading tumors (LSTs). The aim of this study was to evaluate the risk factors and patterns of submucosal invasion in a large series of LSTs that were removed en bloc.
Patients And Methods:
Prospectively collected endoscopic and pathological data on a total of 822 LSTs, ≥ 10 mm in size and removed en block by endoscopic submucosal dissection (n = 670) or surgery (n = 152), were retrospectively analyzed.
Results:
In 414 LSTs of the granular type, submucosal invasion was detected in 80 cases (19 %; 95 % confidence interval [CI] 16 - 23) and was deep (≥ 1000 μm) in 79 % of cases. The invasion site was under a large (≥ 10 mm) nodule (56 %), depression (28 %), or was multifocal (16 %). Risk factors for deep submucosal invasion on multivariate analysis were the presence of a large nodule (odds ratio [OR] 12, 95 %CI 2 - 59), depression (OR 59, 95 %CI 9 - 387), and invasive pit pattern (OR 33, 95 %CI 12 - 88). The sensitivity and specificity of invasive pit pattern for detection of deep submucosal invasion were 52 % (95 %CI 40 % - 64 %) and 98 % (95 %CI 96 % - 99 %), respectively.In 408 LSTs of the nongranular type, submucosal invasion was detected in 159 cases (39 %; 95 %CI 34 - 44) and was deep in 54 % of cases. The invasion site was under a submucosal mass-like elevation (10 %), depression (45 %), or was multifocal (45 %). Risk factors for deep submucosal invasion were the presence of a submucosal mass-like elevation (OR 8, 95 %CI 1 - 61), depression (OR 28, 95 %CI 8 - 97), and invasive pit pattern (OR 79, 95 %CI 25 - 256).
Conclusions:
Because of a substantial risk of submucosal invasion and multifocal invasion, granular type LSTs with a large nodule or depression and nongranular type LSTs should be endoscopically removed en bloc.
More Related Videos
 07:13
Comparison of Predictive Performance of Three Lymph Node Staging Systems in Colorectal Signet Ring Cell Carcinoma Based on Machine Learning Model
Published on: April 18, 2025
 06:46
Competing-Risk Nomogram for Predicting Cancer-Specific Survival in Multiple Primary Colorectal Cancer Patients after Surgery
Published on: September 27, 2024