Related Experiment Video
Updated: Mar 25, 2026
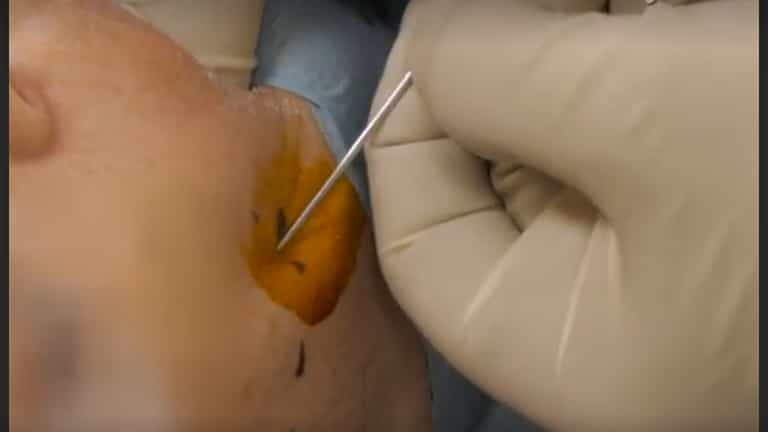

Network Analysis of Foramen Ovale Electrode Recordings in Drug-resistant Temporal Lobe Epilepsy Patients
Published on: December 18, 2016
Integrity of the corpus callosum in patients with benign temporal lobe epilepsy
Maria Eugenia Caligiuri1, Angelo Labate1,2, Andrea Cherubini1
1Institute of Molecular Bioimaging and Physiology of the National Research Council (IBFM-CNR), Catanzaro, Italy.

Objective:
Corpus callosum (CC) abnormalities are frequently reported in patients with refractory mesial temporal lobe epilepsy (rMTLE). However, whether CC structural alterations are related to the epileptic syndrome itself or to refractoriness is still unknown. Thus, we aimed to compare patterns of CC change in patients with rMTLE and benign MTLE (bMTLE), the latter of which represents a useful resource to better disentangle factors that contribute to refractoriness.
Methods:
The study group included 79 patients with bMTLE (mean age 43.2 ± 14. 8 years), 61 with rMTLE (mean age 45.2 ± 12.4 years) and 134 healthy volunteers. Structural magnetic resonance imaging (MRI) and diffusion tensor imaging (DTI) were performed to measure thickness, mean diffusivity (MD), and fractional anisotropy (FA) over 50 regions of interest along the cross-sectional CC profile. Statistical analysis comprised analysis of variance (ANOVA) followed by post hoc Tukey's Honest Significant Difference test.
Results:
We found that all imaging metrics of the CC splenium were altered in rMTLE patients compared to bMTLE and controls. We also found significantly reduced thickness and FA of the anterior CC in rMTLE compared to controls and that FA was reduced only in rMTLE compared to bMTLE. Patients with bMTLE did not differ from controls. Differences between disease subgroups were found in the midbody composed of sensorimotor fibers.
Significance:
We found altered multimodal imaging metrics of the CC in rMTLE but not in bMTLE. These findings were independent of the radiologic presence of hippocampal sclerosis, suggesting that differences in the distribution of such alterations might be related to refractoriness.
Insights
Refractory mesial temporal lobe epilepsy (rMTLE) shows corpus callosum (CC) changes, unlike benign MTLE. These CC alterations may indicate epilepsy refractoriness, independent of hippocampal sclerosis.
Area of Science:
- Neuroimaging
- Epilepsy Research
- Structural Brain Analysis
Background:
- Corpus callosum (CC) abnormalities are common in refractory mesial temporal lobe epilepsy (rMTLE).
- It remains unclear if CC changes are due to the epilepsy syndrome or treatment refractoriness.
- Comparing rMTLE with benign MTLE (bMTLE) can help identify factors contributing to refractoriness.
Purpose of the Study:
- To compare corpus callosum (CC) structural alterations in patients with rMTLE and bMTLE.
- To investigate if CC changes are associated with epilepsy refractoriness.
- To differentiate CC alterations related to the epilepsy syndrome versus refractoriness.
Main Methods:
- Included 79 bMTLE patients, 61 rMTLE patients, and 134 healthy controls.
- Utilized structural MRI and diffusion tensor imaging (DTI) to assess CC thickness, mean diffusivity (MD), and fractional anisotropy (FA).
- Analyzed 50 regions along the CC profile using ANOVA and post hoc tests.
Main Results:
- rMTLE patients exhibited altered CC splenium imaging metrics compared to bMTLE and controls.
- Reduced anterior CC thickness and FA were observed in rMTLE versus controls.
- FA was reduced in rMTLE compared to bMTLE, with differences in the midbody correlating with sensorimotor fibers.
Conclusions:
- Multimodal imaging metrics of the CC are altered in rMTLE but not in bMTLE.
- These corpus callosum alterations in rMTLE are independent of hippocampal sclerosis.
- The distribution of CC changes may be linked to epilepsy refractoriness.

Related Concept Videos
 01:05
Cerebral Hemispheres
 01:13
Seizures: Classification
Seizures are typically classified into two main categories: focal and generalized seizures.
Focal Seizures
Focal seizures originate from specific regions of the brain. These seizures are further sub-classified into two types: