Related Experiment Video
Updated: Mar 24, 2026


Homogeneous Time-resolved Förster Resonance Energy Transfer-based Assay for Detection of Insulin Secretion
Published on: May 10, 2018
Determination of Insulin Secretory Defect and Insulin Sensitivity in Type 2 Diabetic Subjects in Bangladesh
1Dr Jannatul Ferdous, Assistant Professor, Department of Biochemistry, Northern Medical College, Dhaka, Bangladesh.

Abstract:
Diabetes mellitus (DM) is defined as a group of metabolic diseases characterized by hyperglycemia resulting from defects in insulin secretion, insulin action, or both. This study was undertaken to explore the basic defect in type 2 diabetes patients in Bangladesh. This was an observational study with case control design, was conducted in the Biomedical Research Group, Research Division, Bangladesh Institute of Research and Rehabilitation in Diabetes, Endocrine Metabolic Disorders (BIRDEM), Dhaka, Bangladesh, during the period of July 2008 to June 2009. A total of 153 subjects were included in study of which 63 belonged to type 2 diabetes mellitus group and 90 were healthy controls. Fasting and 2 hours postprandial blood glucose, serum insulin, HOMA%B, HOMA%S, QuickI, Glucose /insulin ratio, TG were measured and age, BMI, WHR were recorded. Waist-hip ratio (WHR), was significantly higher in T2DM as compared to control subjects [WHR, mean±SD, 0.94±0.12 vs. 0.88±0.06, p<0.001]; Glucose and insulin ratio of T2DM was significantly higher as compared to control subject [Glu: Ins, Median (range) of 0.54 (0.17-2.33) vs. 0.37(0.06-1.52)]. Insulin secretion (HOMA%B) was significantly lower in diabetic as compared to control subjects [HOMA%B, median (range), 71(4.90-391) vs. 180(59-634) p<0.001]; The quantitative insulin sensitivity check Index (QUICKI) of diabetic subjects were significantly higher as compared to control [QUICKI median (range) 39.90(4.80-138.10) vs. 0.55(0.36-0.85), <0.001]. Triglyceride (TG) and cholesterol (Chol) were significantly higher [(mg/dl), (mean±SD), TG (142±80.14) vs. (142±80.14); Chol (189±50.76) vs. (172±45), p=0.029] in T2DM as compared to control subjects. Those with diabetes showed significant association with insulin secretory defect (HOMA%B, p=0.006) and insulin resistance as assessed by GINR (p<0.001) and QuickI (p<0.001) but not by HOMA%S (p=0.127). The present data suggest that both insulin secretory defect and insulin sensitivity are present in T2 diabetic subjects of Bangladesh.
Related Concept Videos
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:36
Carbohydrate Metabolism
Starch accounts for approximately 60% of the carbohydrates consumed by humans. Since amylase enzymes cannot function in the stomach's acidic environment, starch can only be digested in the mouth and small intestine. Simple sugars are found naturally in milk and fruits in...
 01:25
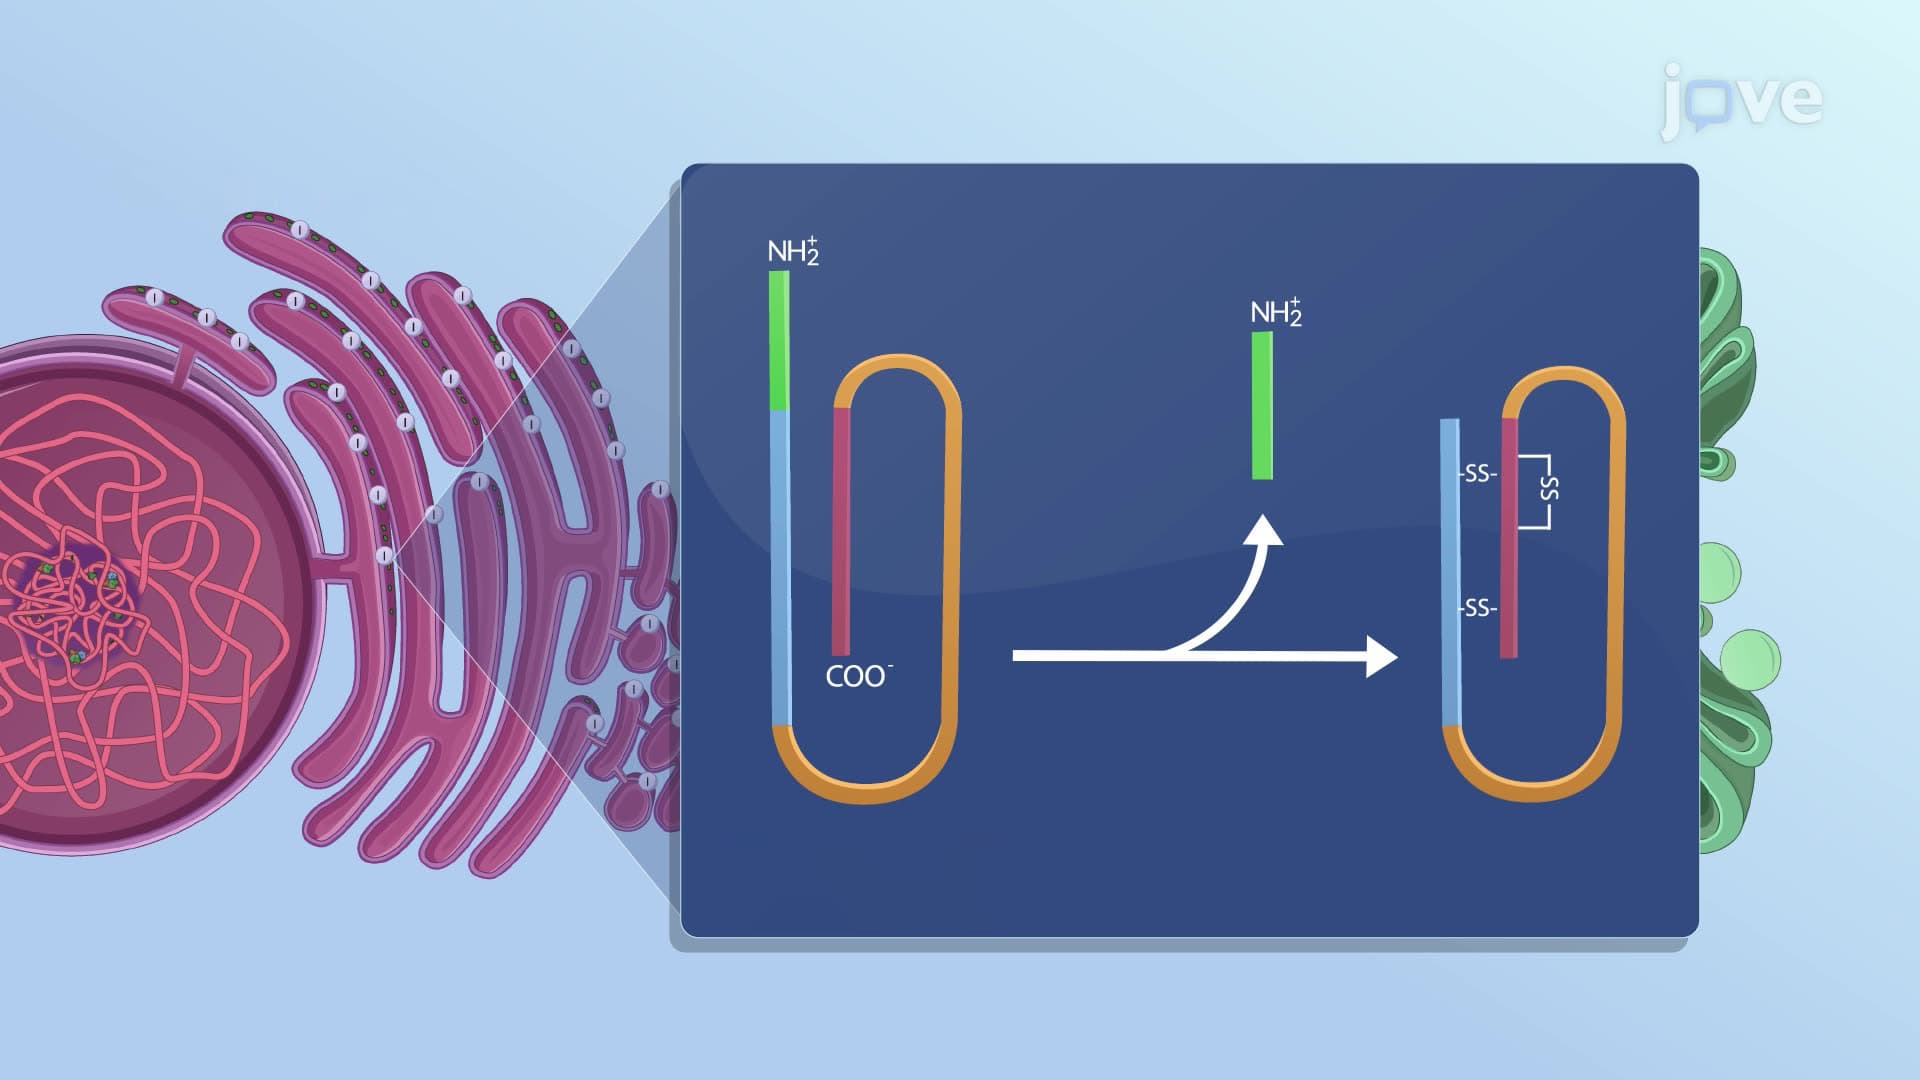
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment...
 01:15
Diabetes: Symptoms, Diagnosis, and Complications