Related Experiment Video
Updated: Mar 24, 2026
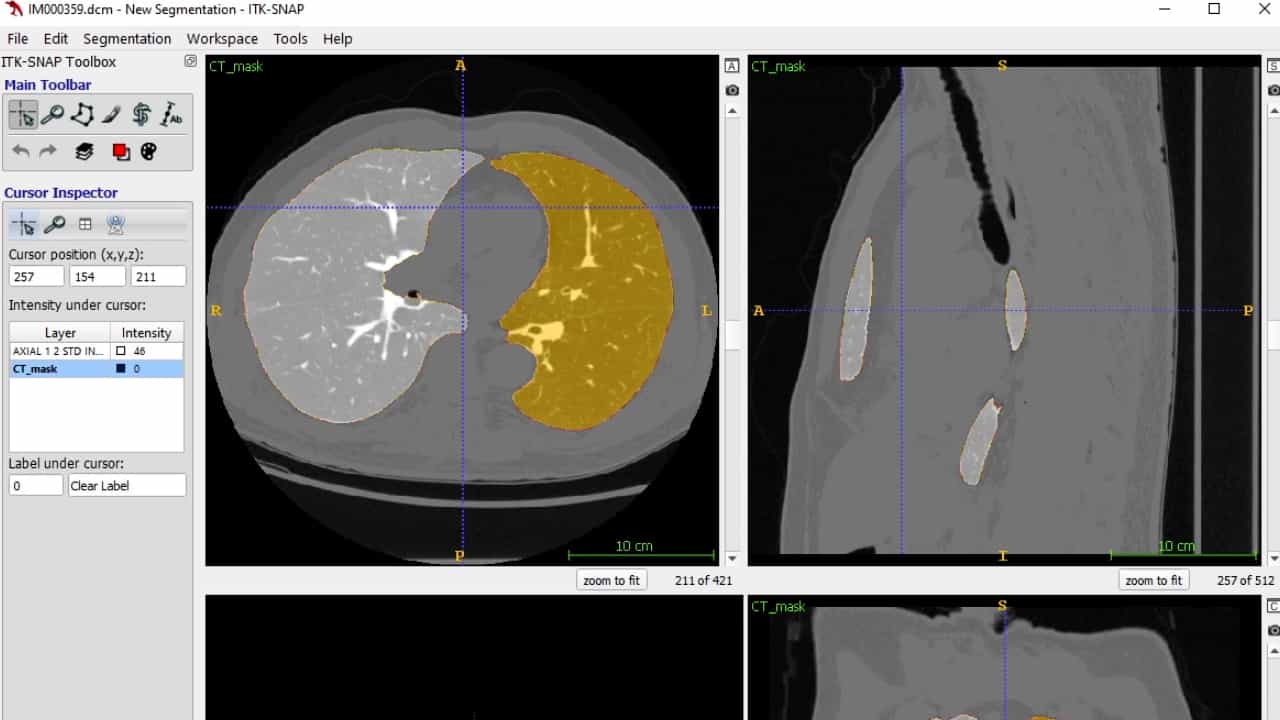
Multi-modal Pulmonary Imaging: Using Complementary Information from CT and Hyperpolarized 129Xe MRI to Evaluate Lung Structure-Function
Published on: April 12, 2024
Correlation between clinical characteristics, spirometric indices and high resolution computed tomography findings in
Anubhuti Singh1, Santosh Kumar1, Ashwini Kumar Mishra1
1Department of Pulmonary Medicine, King George Medical University, Lucknow, Uttar Pradesh, India.

Introduction:
Chronic obstructive pulmonary disease (COPD) is a chronic inflammatory disease affecting the airways, leading to significant morbidity and mortality throughout the world. There is a need to have a holistic evaluation of COPD patients, other than just measuring the level of obstruction as performed by spirometry. High resolution computed tomography (HRCT) scan of thorax partly fulfills this requirement.
Materials And Methods:
Fifty patients of COPD (confirmed on spirometry as per the GOLD guidelines 2014 guidelines) were enrolled, out of which 35 patients got a HRCT done. Complete clinical evaluation was done. The Philips computer program for lung densitometry was used with these limits (-800/-1, 024 Hounsfield unit [HU]) to calculate densities, after validating densitometry values with phantoms. We established the area with a free hand drawing of the region of interest, then we established limits (in HUs) and the computer program calculated the attenuation as mean lung density (MLD) of the lower and upper lobes.
Results:
There was a significant correlation between smoking index and anteroposterior tracheal diameter (P = 0.036). Tracheal index was found to be decreasing with increasing disease severity which was statistically significant (P = 0.037). Mean upper lobe MLD was -839.27 HU, mean lower lobe MLD was -834.91 HU and the mean MLD was -837.08 HU. The lower lobes MLD were found to be decreasing with increasing disease severity. A mild linear correlation of pre forced expiratory volume in the first second (FEV1) was observed with lower lobe and total average MLD while a mild linear correlation of Post-FEV1 was observed with both coronal (P = 0.042) and sagittal (P = 0.001) lower lobes MLD. In addition, there was a linear correlation between both pre (P = 0.050) and post (P = 0.024) FEV1/forced vital capacity with sagittal lower lobe MLD. A predictive model can be derived to quantify obstruction severity (FEV1).
Conclusion:
HRCT may be an important additional tool in the holistic evaluation of COPD. HRCT can well be correlated with the spirometric and clinical features and the level of obstruction can be indirectly derived from it by measuring the MLD.

Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD: