Related Experiment Video
Updated: Mar 24, 2026


Multimodality Diagnosis of Mesenteric Ischemia
Published on: July 21, 2023
Mycotic aneurysm of the superior and inferior mesenteric artery
Ali Kordzadeh1, James Watson1, Yiannis P Panayiotopolous1
1Department of Vascular and Endovascular Surgery, Broomfield Hospital, Mid Essex Hospital Services NHS Trust, Chelmsford, United Kingdom.

Objective:
Visceral artery aneurysms as a result of arterial degenerative disease are rare (0.1%-2%), and the superior mesenteric artery (SMA) accounts for 3.2% of all reported series. The current incidence of inferior mesenteric artery (IMA) aneurysm is unknown. However, infective causes (mycotic) of SMA and IMA aneurysm as a result of primary, secondary, and cryptogenic etiology remain a separate entity and attain fewer cases in the literature. Currently, there is no consensus on their presentation, diagnosis, and overall management.
Methods:
A systematic review and meta-aggregation of literature from 1944 to March 2015 in the English language and of adult subjects in MEDLINE, Ovid, CINAHL, and the Cochrane database was conducted.
Results:
The median age of patients with SMA aneurysm was 36 (range, 14-92) years, with a significant male predominance (73% vs 27%). In order of prevalence, abdominal pain (n = 25; 65%), low-grade fever (n = 23; 60%), malaise (n = 10; 26%), weight loss (n = 9; 23%), and nausea and vomiting (n = 8; 20%) were the most common presenting signs and symptoms. The most common microorganism was Streptococcus (n = 18; 47%), followed by Staphylococcus (n = 11; 28%). The investigative modality of choice was computed tomography (n = 22; 57.8%), followed by ultrasonography of the abdomen (n = 9; 23%). Primary etiology was noted in 5.4%, secondary in 71%, and cryptogenic in 13% of all cases. Aneurysmectomy alone was associated with bowel resection in four cases (10.5%), whereas aneurysmectomy with interposition vein grafting required no further intervention. The inpatient mortality after surgery was 7.8%, and the overall mortality was 15%. The median follow-up was 12 months (range, 2-120 months). The median age of patients with IMA aneurysm was 48 (range, 22-64) years, with a male predominance of 2:1 and abdominal pain in all cases (n = 3; 100%). The most common microorganism was Streptococcus (n = 2; 66.6%), and the operation of choice was aneurysmectomy (n = 2; 66.6%) after computed tomography scan (n = 3; 100%) as an investigative modality of choice.
Conclusions:
The pentad of abdominal pain, pyrexia of unknown origin, malaise, weight loss, and nausea remains the most convincing presentation of mycotic aneurysms of the SMA and IMA. Computed tomography is the investigative modality of choice, and such patients are best served with aneurysmectomy alone in IMA aneurysms and interposition vein grafting in SMA aneurysms after initiation of antimicrobial therapy on suspicion of the diagnosis.
Insights
Mycotic aneurysms of the superior mesenteric artery (SMA) and inferior mesenteric artery (IMA) present with abdominal pain and fever. Computed tomography is key for diagnosis, with surgery and antimicrobial therapy guiding treatment.
Area of Science:
- Vascular Surgery
- Infectious Diseases
- Radiology
Background:
- Visceral artery aneurysms, particularly those of the superior mesenteric artery (SMA) and inferior mesenteric artery (IMA), are rare, often stemming from degenerative arterial disease.
- Infective (mycotic) causes of SMA and IMA aneurysms are distinct entities with limited reported cases and no established consensus on management.
- The incidence of inferior mesenteric artery (IMA) aneurysm remains largely unknown.
Purpose of the Study:
- To systematically review and meta-aggregate existing literature on mycotic aneurysms of the SMA and IMA.
- To elucidate the presentation, diagnostic modalities, and management strategies for these rare conditions.
- To identify optimal surgical interventions and assess outcomes.
Main Methods:
- A systematic review and meta-aggregation of English-language literature from 1944 to March 2015.
- Inclusion criteria comprised adult subjects from MEDLINE, Ovid, CINAHL, and the Cochrane databases.
- Data extraction focused on patient demographics, clinical presentation, causative microorganisms, diagnostic imaging, treatment, and outcomes.
Main Results:
- SMA aneurysms occurred in a median age of 36 years, predominantly in males (73%), with common symptoms including abdominal pain (65%) and fever (60%). Streptococcus and Staphylococcus were the most frequent pathogens.
- Computed tomography (CT) was the preferred diagnostic tool (57.8%). Surgical management varied, with aneurysmectomy alone associated with bowel resection (10.5%), while interposition vein grafting showed better outcomes.
- IMA aneurysms presented in older patients (median 48 years), with all cases reporting abdominal pain. Streptococcus was the commonest microorganism, and CT was the primary diagnostic modality.
Conclusions:
- The classic presentation of mycotic SMA and IMA aneurysms includes abdominal pain, pyrexia of unknown origin, malaise, weight loss, and nausea.
- Computed tomography is the recommended imaging modality for diagnosis.
- Optimal management involves aneurysmectomy for IMA aneurysms and interposition vein grafting for SMA aneurysms, following initiation of antimicrobial therapy.


Related Concept Videos
 01:25
Abdominal Aorta
The celiac trunk, a singular artery, divides into the left gastric artery, which...
 01:30
Aneurysm I: Introduction
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:26
Aneurysm III: Interprofessional Care
 01:10
The Arch of Aorta
Encircling the heart, the coronary arteries form a ring-like structure before...
 01:16
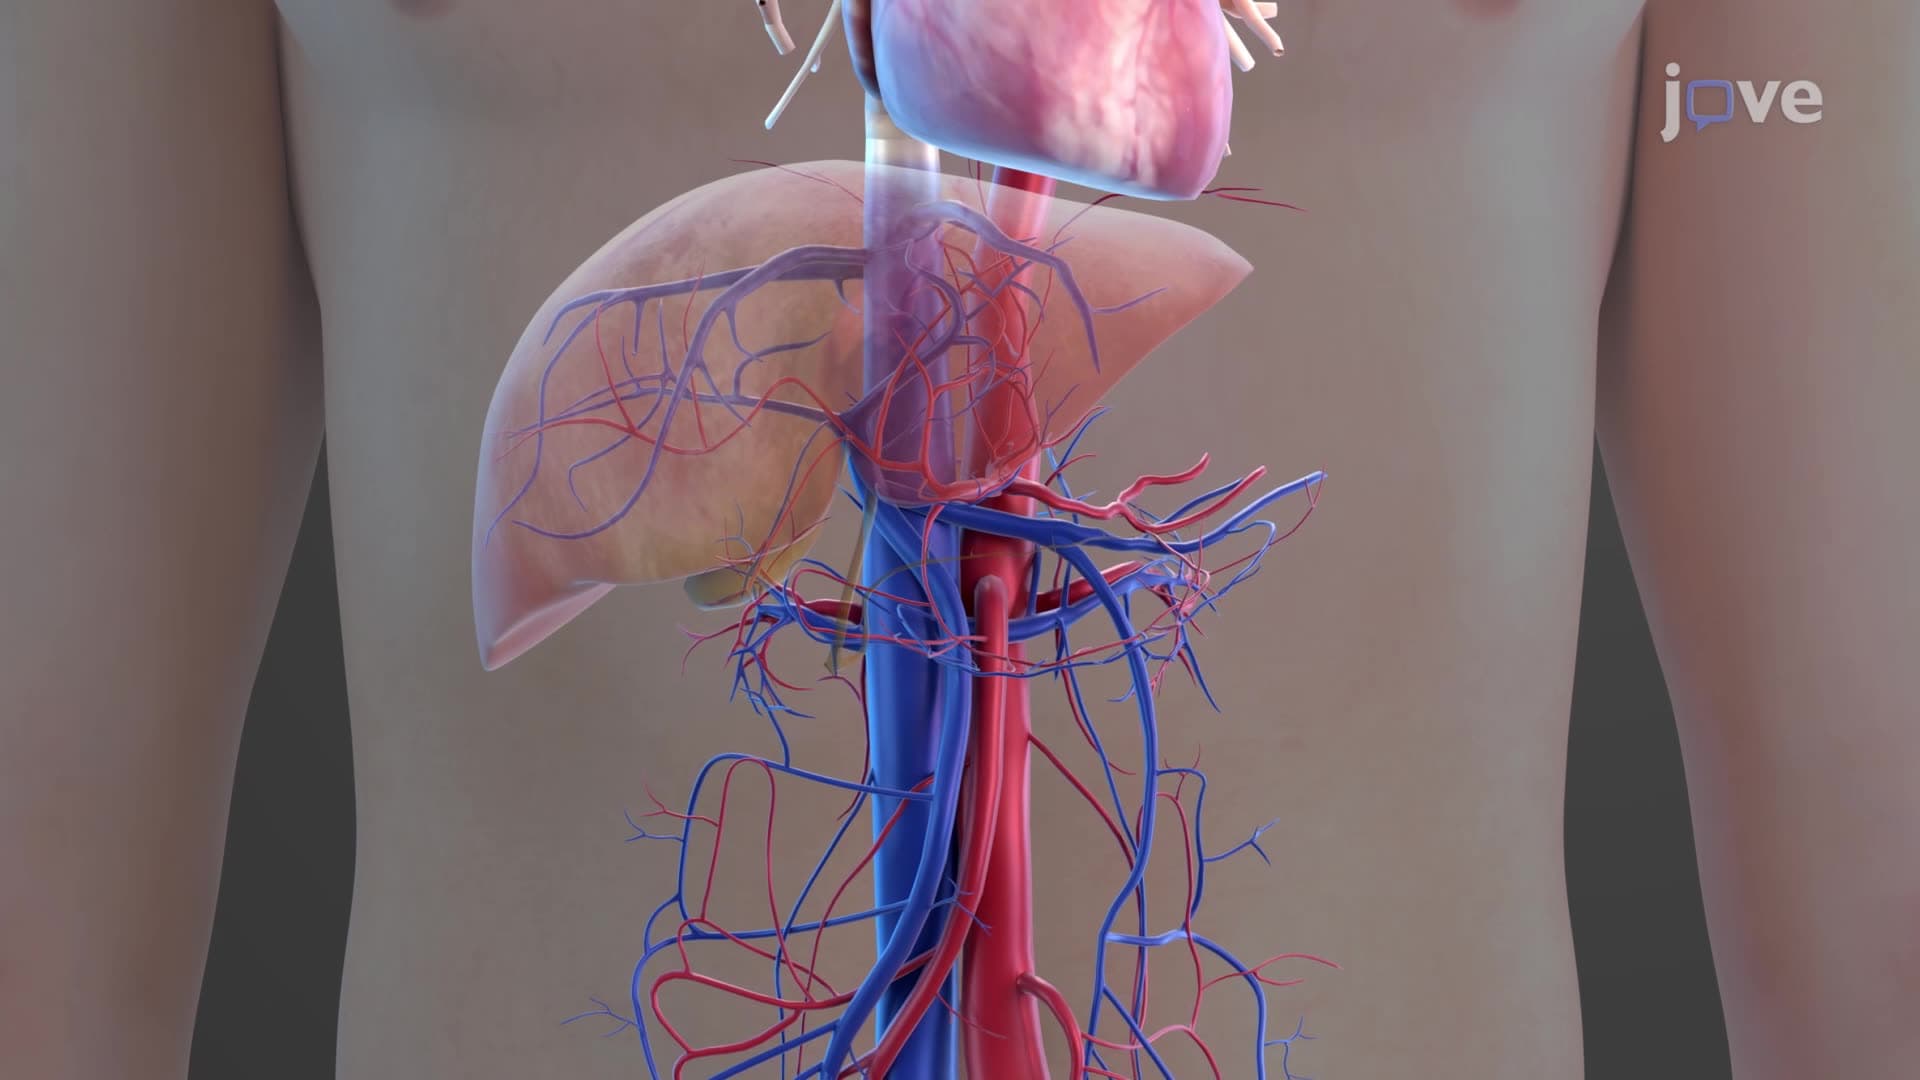
Blood Supply to the Digestive System
Blood Supply to the Digestive System: The splanchnic circulation involves three main arteries: the celiac artery (also known as the celiac trunk) and the superior and inferior mesenteric...