Related Experiment Video
Updated: Mar 24, 2026

Endobronchial Ultrasound-guided Intratumoral Injection of Cisplatin for the Treatment of Isolated Mediastinal Recurrence of Lung Cancer
Published on: February 12, 2017
Dose escalation for unresectable locally advanced non-small cell lung cancer: end of the line?
Julian C Hong1, Joseph K Salama1
1Department of Radiation Oncology, Duke University, Durham, NC, USA.

Abstract:
Radiation Therapy Oncology Group (RTOG) 0617 was a randomized trial that investigated both the impact of radiation dose-escalation and the addition of cetuximab on the treatment of non-small cell lung cancer (NSCLC). The results of RTOG 0617 were surprising, with the dose escalation randomization being closed prematurely due to futility stopping rules, and cetuximab ultimately showing no overall survival benefit. Locally advanced unresectable NSCLC has conventionally been treated with concurrent chemoradiation. Though advances in treatment technology have improved the ability to deliver adequate treatment dose, the foundation for radiotherapy (RT) has remained the same since the 1980s. Since then, progressive studies have sought to establish the safety and efficacy of escalating radiation dose to loco-regional disease. Though RTOG 0617 did not produce the anticipated result, much interest remains in dose escalation and establishing an explanation for the findings of this study. Cetuximab was also not found to provide a survival benefit when applied to an unselected population. However, planned retrospective analysis suggests that those patients with high epidermal growth factor receptor (EGFR) expression may benefit, suggesting that cetuximab should be applied in a targeted fashion. We discuss the results of RTOG 0617 and additional findings from post-hoc analysis that suggest that dose escalation may be limited by normal tissue toxicity. We also present ongoing studies that aim to address potential causes for mortality in the dose escalation arm through adaptive or proton therapy, and are also leveraging additional concurrent systemic agents such as tyrosine kinase inhibitors (TKIs) for EGFR-activating mutations or EML4-ALK rearrangements, and poly (ADP-ribose) polymerase (PARP) inhibitors.
More Related Videos
 09:38
Establishing Dual Resistance to EGFR-TKI and MET-TKI in Lung Adenocarcinoma Cells In Vitro with a 2-step Dose-escalation Procedure
Published on: August 11, 2017
 11:17
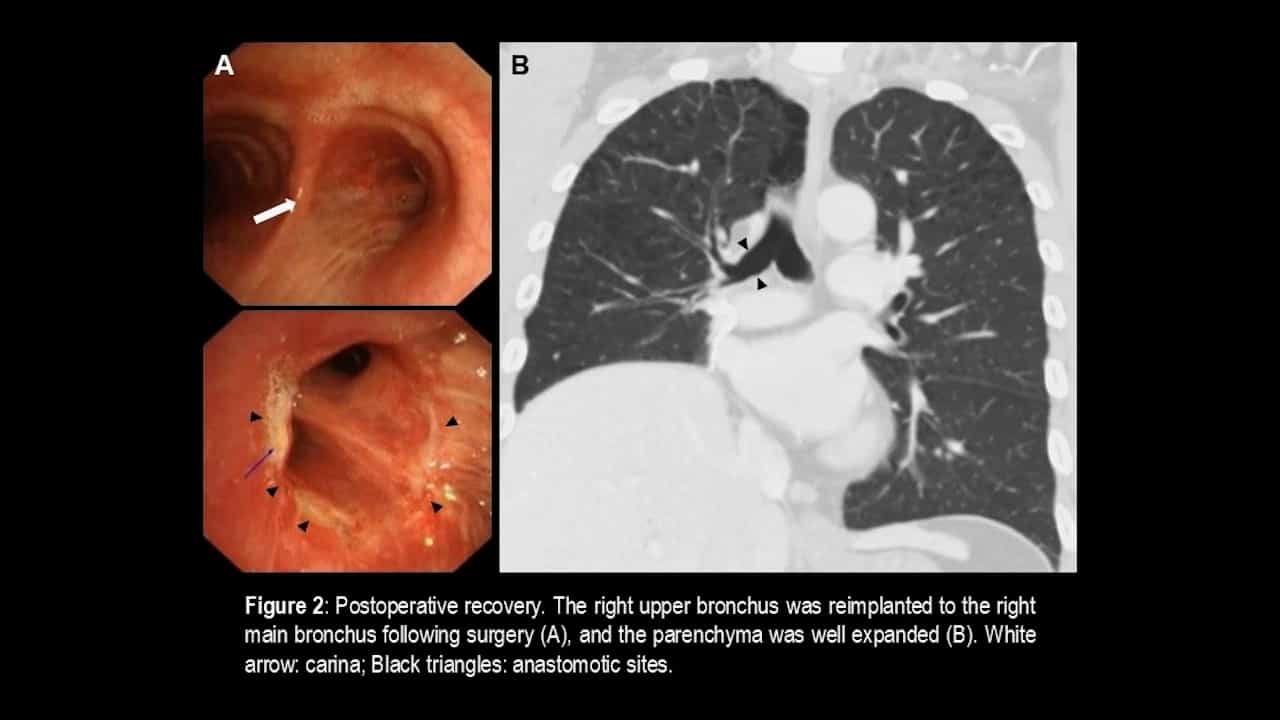
Thoracoscopic Extended Right Middle Plus Lower Sleeve Lobectomy for Non-Small-Cell Lung Cancer
Published on: February 27, 2026
