

Pre-hospital electrocardiographic severity and acuteness scores predict left ventricular function in patients with ST
Yama Fakhri1, Mads Ersbøll2, Lars Køber2
1Department of Cardiology, Rigshospitalet, Copenhagen University Hospital, Copenhagen, Denmark; Department of Medicine, Division of Cardiology, Nykøbing F Hospital, Copenhagen University Hospital, Nykøbing F, Denmark.

Insights
System delay impacts left ventricular function in ST-segment elevation myocardial infarction (STEMI) patients. Early intervention is crucial for those with severe and acute ischemia, improving outcomes.
Area of Science:
- Cardiology
- Medical Diagnostics
- Clinical Research
Background:
- System delay in ST-segment elevation myocardial infarction (STEMI) correlates with adverse outcomes.
- Left ventricular function (LVF) is a key predictor of prognosis post-STEMI.
- Pre-hospital electrocardiogram (ECG) findings can indicate ischemia severity and acuteness.
Purpose of the Study:
- To assess the impact of system delay on LVF in STEMI patients.
- To evaluate this impact based on combined pre-hospital ECG indicators of ischemia severity and acuteness.
- To identify patient subgroups who may benefit most from reduced system delay.
Main Methods:
- Secondary analysis of a prospective study involving 262 STEMI patients.
- Pre-hospital ECGs were scored for ischemia severity (Sclarovsky-Birnbaum grades) and acuteness (Anderson-Wilkins scores).
- LVF was assessed using global longitudinal strain (GLS) within 48 hours; adjusted linear regression analyzed system delay's association with GLS.
Main Results:
- Patients with severe and non-acute ischemia exhibited the most impaired LVF.
- System delay weakly correlated with GLS in the entire cohort but strongly in the severe and acute ischemia group.
- Adjusted analysis revealed system delay predicted impaired GLS exclusively in the severe and acute ischemia subgroup.
Conclusions:
- Pre-hospital ECG-based risk stratification can identify STEMI patients at higher risk for reduced LVF.
- Patients with severe and acute ischemia are particularly vulnerable to the negative effects of system delay on LVF.
- Optimizing reperfusion times in this high-risk group is critical for improving clinical outcomes after STEMI.
Objectives:
System delay (time from first medical contact to primary percutaneous coronary intervention) is associated with heart failure and mortality in patients with ST segment elevation myocardial infarction (STEMI). We evaluated the impact of system delay on left ventricular function (LVF) according to the combination of ischemia severity (Sclarovsky-Birnbaum grades) and acuteness (Anderson-Wilkins scores) in the pre-hospital electrocardiogram (ECG).
Methods:
In a predefined secondary analysis of a prospective study, the severity and acuteness scores were performed on the pre-hospital ECG. Patients were assessed with respect to 4 classifications which were not mutually exclusive: severe ischemia (+SI) or non-severe ischemia (-SI) and acute ischemia (+AI) or non-acute ischemia (-AI). LVF was assessed by global longitudinal strain (GLS) within 48hours of admission. Adjusted linear regression investigated the association of system delay with GLS in each group.
Results:
In total 262 patients were eligible for analysis of the ECG, which resulted in 42 (16%) with (+SI, -AI), 110 (42%) with (-SI, -AI), 90 (34%) with (-SI, +AI), and 20 (8%) patients with (+SI, +AI). Although system delay did not differ between groups, patients with severe and non-acute ischemia had the most impaired LVF. System delay correlated weakly with GLS in the entire population (r=0.133, p=0.031), and well with GLS in the (+SI, +AI) group (r=0.456, p=0.04), while there was no correlation in the other groups. By adjusted analysis, system delay predicted impaired GLS only in the (+SI, +AI) group (β=0.578, p=0.002).
Conclusion:
Pre-hospital risk stratification by ECG identifies patients with acute and severe ischemia who are at increased risk for reduced ventricular function (assessed by GLS) after STEMI. Optimizing reperfusion delays in these patients can therefore be of particular benefit in improving clinical outcome after STEMI.
More Related Videos


Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:30
Acute Coronary Syndrome I: Introduction
 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and...
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:26
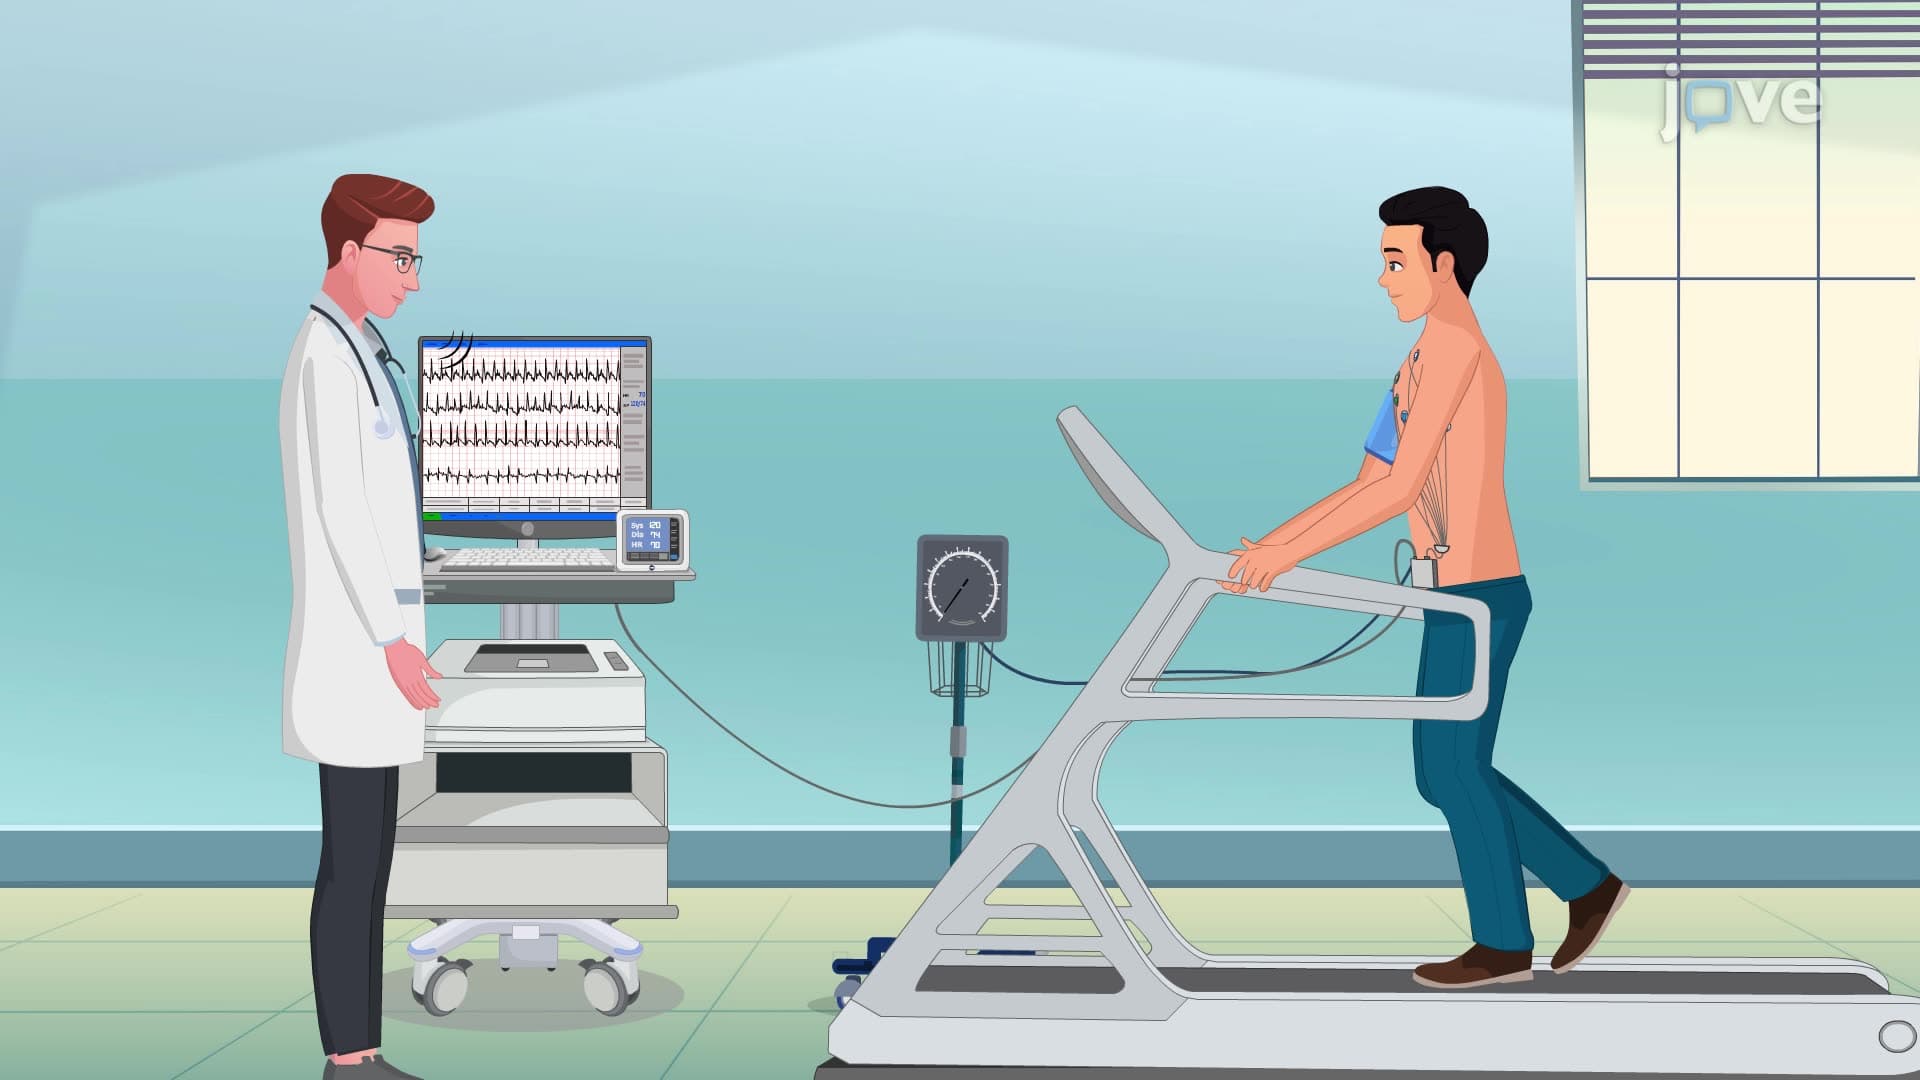
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes