

Successful management of chylous ascites: A report of two cases
Shaan E Alam, Sunny M Kar, Pran M Kar1
1Department of Nephrology, Veterans Affairs Medical Center, Orlando, Florida, USA.

Abstract:
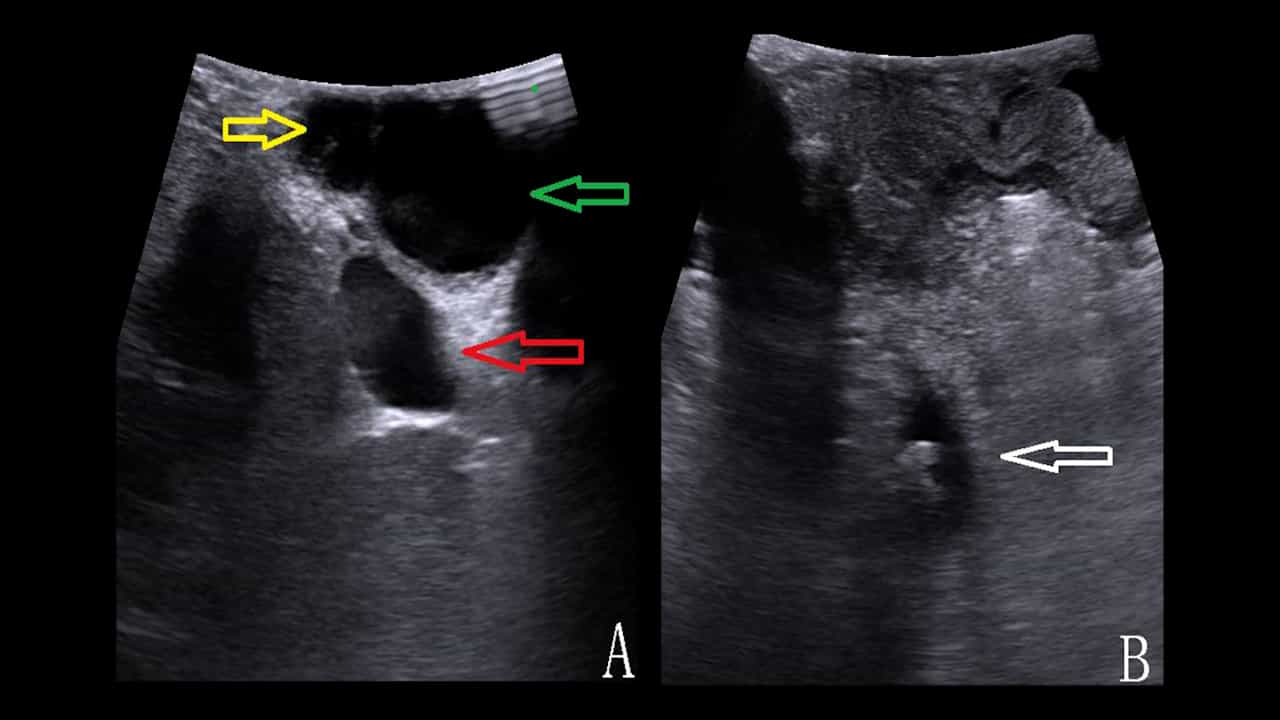
Chylous ascites consists of the accumulation of chyle in the peritoneal cavity. Diagnosis is established by cytochemical analysis of the fluid revealing fat globules and high triglyceride content. The majority of cases are caused by pathology that interferes with abdominal retroperitoneal lymphatic drainage. We present two cases of postoperative chylous ascites, one following a bilateral nephrectomy, the other following orthotopic heart transplantation. Treatment is typically conservative with the aim to alleviate abdominal distension and reduce the flow of lymph into the mesenteric lymph nodes. Postsurgical chylous ascites has high cure rate with conservative therapy alone. Therapeutic paracentesis, diuretics, salt restriction, a high-protein, low-fat, mediumchain triglyceride diet, and parenteral nutrition are considered in chronic cases. The effects of longterm paracentesis on patients remains to be seen. In patients requiring renal replacement therapy, removal of chyle during peritoneal dialysis is often attempted.
Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:24
Nephrotic Syndrome III : Nursing Management
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:26
Nephrotic Syndrome II : Assessment and Medical Management