Related Experiment Video
Updated: Mar 23, 2026

Author Spotlight: Advancing Early Detection and Treatment of Gastrointestinal Tumors
Published on: February 16, 2024
Risk factors determining the need for second-look endoscopy for peptic ulcer bleeding after endoscopic hemostasis and
Hsiu-Chi Cheng1, Chung-Tai Wu1, Wei-Ying Chen1
1Institute of Clinical Medicine, National Cheng Kung University Hospital, College of Medicine, National Cheng Kung Univeristy, Tainan, Taiwan; Department of Internal Medicine, National Cheng Kung University Hospital, College of Medicine, National Cheng Kung University, Tainan, Taiwan.

Background And Study Aims:
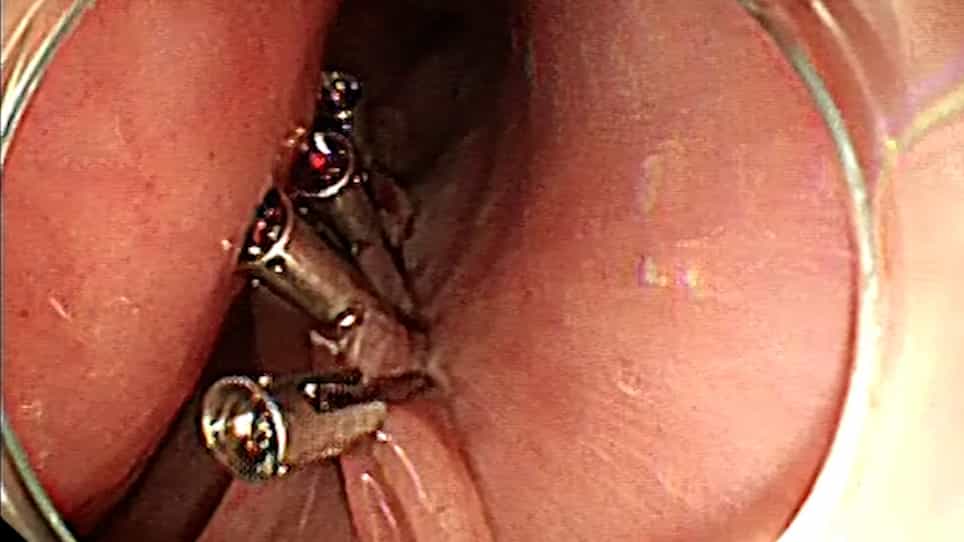
The need for routine second-look endoscopy in cases of peptic ulcer bleeding remains uncertain. We investigated risk factors related to the need for second-look endoscopy after endoscopic hemostasis and proton pump inhibitor (PPI) infusion.
Patients And Methods:
We prospectively enrolled 316 patients with peptic ulcer bleeding after endoscopic hemostasis. Second-look endoscopy was scheduled after 72-hour PPI infusion (Day-3 subgroup) or one day early (Day-2 subgroup). If early rebleeding developed within 3 days, emergent second-look endoscopy was conducted. Risk factors for early rebleeding (use of E2(nd) score to predict the need for early second-look endoscopy) and persistent major stigmata in the Day-3 subgroup (use of R2(nd) score to predict the need for routine second-look endoscopy) were analyzed using univariable and multivariable regression.
Results:
Excluding 10 of 316 patients with early rebleeding, the rate of persistent major stigmata was lower in the Day-3 subgroup than in the Day-2 subgroup (4.8 % vs. 15.4 %, P = 0.002). Endoscopic epinephrine-injection monotherapy and hypoalbuminemia < 3.0 g/dL were two independent risk factors for early rebleeding (P ≤ 0.05). The Forrest Ia-Ib type and hypoalbuminemia < 3.5 g/dL were two independent risk factors for persistent major stigmata on the day-3 second-look endoscopy (P < 0.05). The E2(nd) score was highly accurate for prediction of early rebleeding (AUROC 0.86; 95 % CI, 0.73~0.99), and the R2(nd) score could predict persistent major stigmata at second-look endoscopy (AUROC 0.84; 95 % CI, 0.69~0.99).
Conclusions:
For patients with peptic ulcer bleeding, E2(nd) and R2(nd) scores can indicate the need for early and routine second-look endoscopy, respectively (Trial registration identifier: NCT02197039).
Related Concept Videos
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:24
Pathophysiology of Peptic Ulcer Disease: Mucosal Defense Factors
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds...
 01:13
Acid Suppressive Drugs for Peptic Ulcer Disease: Proton Pump Inhibitors
Gastric acid, a potent cocktail of hydrogen and chloride ions, is produced in specialized parietal cells within the...