Related Experiment Video
Updated: Mar 23, 2026

Author Spotlight: A Non-Intubated Video-Assisted Thoracoscopic Surgery with Multimodal Analgesia and Sevoflurane Inhalation Anesthesia
Published on: May 26, 2023
Management of One-lung Ventilation: Impact of Tidal Volume on Complications after Thoracic Surgery
Randal S Blank1, Douglas A Colquhoun, Marcel E Durieux
1From the Department of Anesthesiology (R.S.B., D.A.C., M.E.D., B.I.N.) and Department of Surgery (B.D.K.), University of Virginia Health System, Charlottesville, Virginia; Department of Public Health Sciences, University of Virginia, Charlottesville, Virginia (T.L.M.); and Department of Anesthesiology, University of Vermont College of Medicine, Burlington, Vermont (S.P.B.).

Background:
The use of lung-protective ventilation (LPV) strategies may minimize iatrogenic lung injury in surgical patients. However, the identification of an ideal LPV strategy, particularly during one-lung ventilation (OLV), remains elusive. This study examines the role of ventilator management during OLV and its impact on clinical outcomes.
Methods:
Data were retrospectively collected from the hospital electronic medical record and the Society of Thoracic Surgery database for subjects undergoing thoracic surgery with OLV between 2012 and 2014. Mean tidal volume (VT) during two-lung ventilation and OLV and ventilator driving pressure (ΔP) (plateau pressure - positive end-expiratory pressure [PEEP]) were analyzed for the 1,019 cases that met the inclusion criteria. Associations between ventilator parameters and clinical outcomes were examined by multivariate linear regression.
Results:
After the initiation of OLV, 73.3, 43.3, 18.8, and 7.2% of patients received VT greater than 5, 6, 7, and 8 ml/kg predicted body weight, respectively. One hundred and eighty-four primary and 288 secondary outcome events were recorded. In multivariate logistic regression modeling, VT was inversely related to the incidence of respiratory complications (odds ratio, 0.837; 95% CI, 0.729 to 0.958), while ΔP predicted the development of major morbidity when modeled with VT (odds ratio, 1.034; 95% CI, 1.001 to 1.068).
Conclusions:
Low VT per se (i.e., in the absence of sufficient PEEP) has not been unambiguously demonstrated to be beneficial. The authors found that a large proportion of patients continue to receive high VT during OLV and that VT was inversely related to the incidence of respiratory complications and major postoperative morbidity. While low (physiologically appropriate) VT is an important component of an LPV strategy for surgical patients during OLV, current evidence suggests that, without adequate PEEP, low VT does not prevent postoperative respiratory complications. Thus, use of physiologic VT may represent a necessary, but not independently sufficient, component of LPV.


Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:15
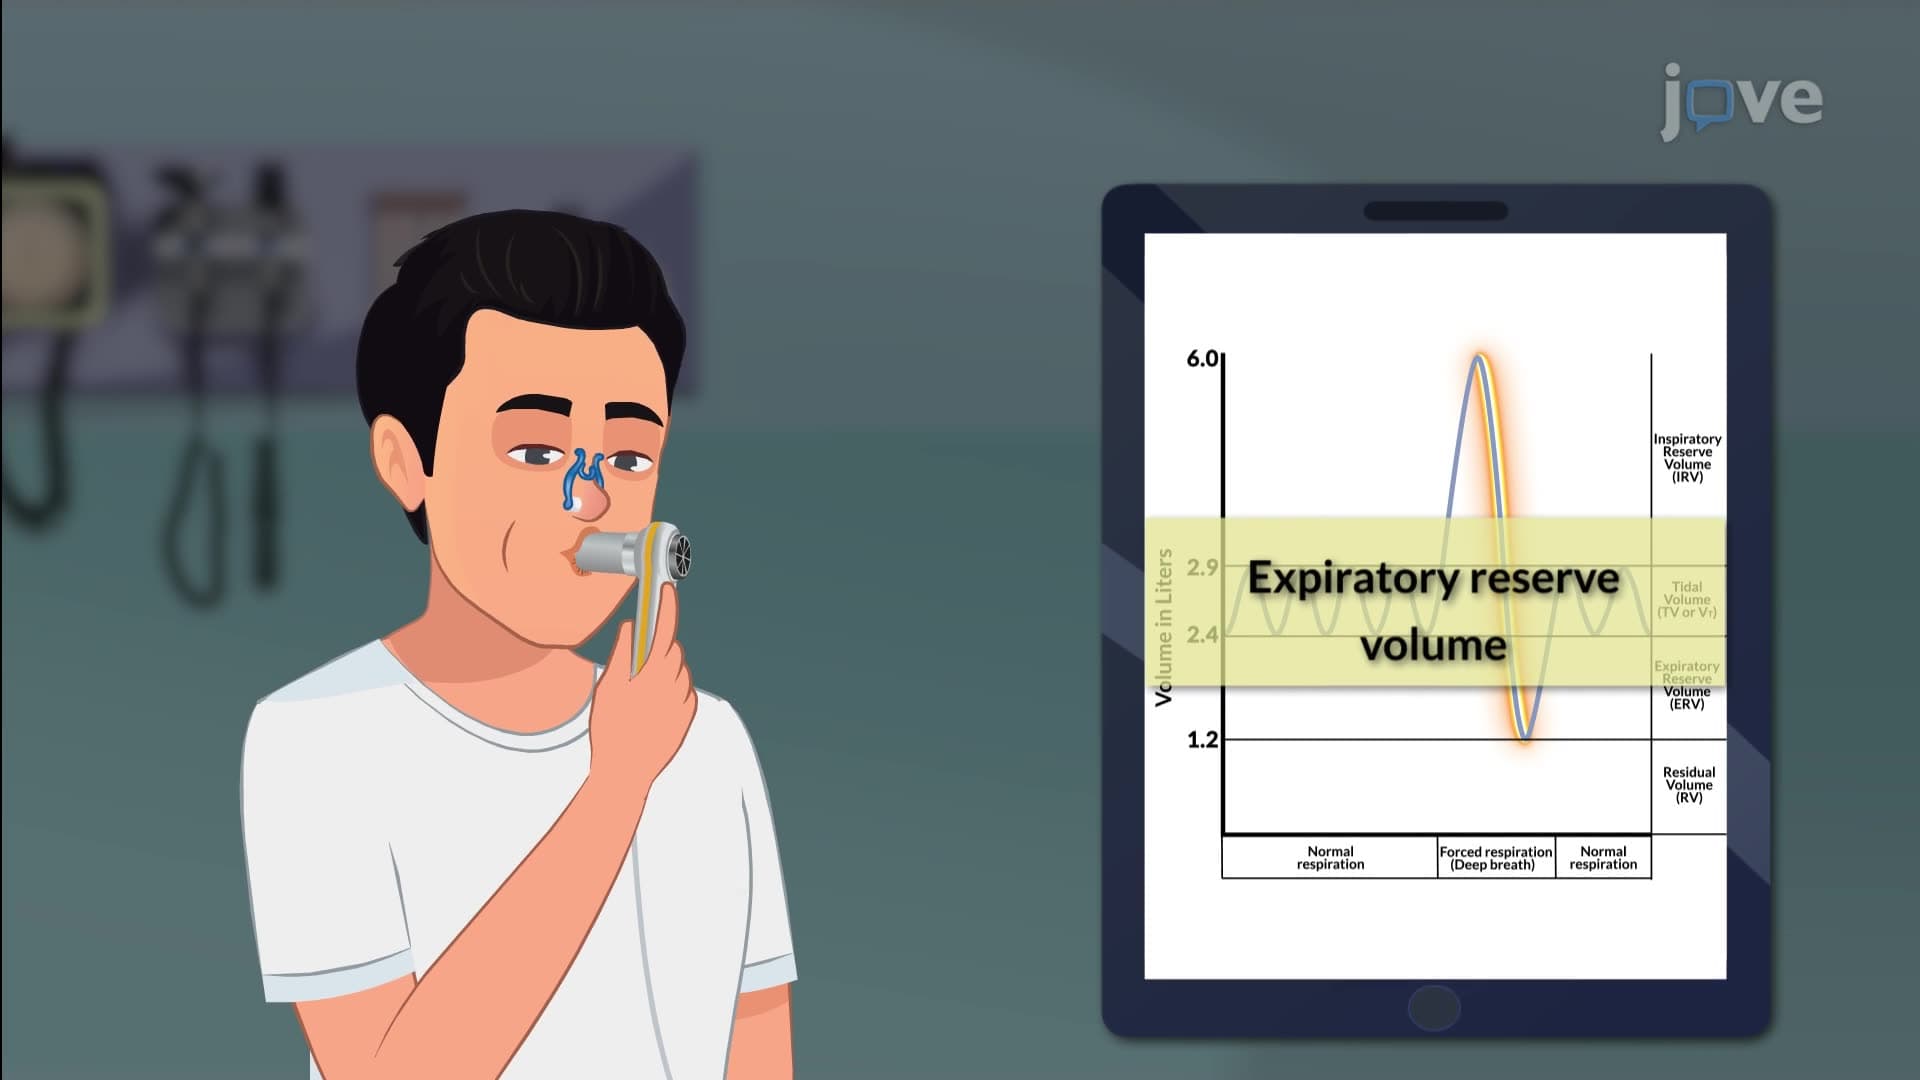
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:24
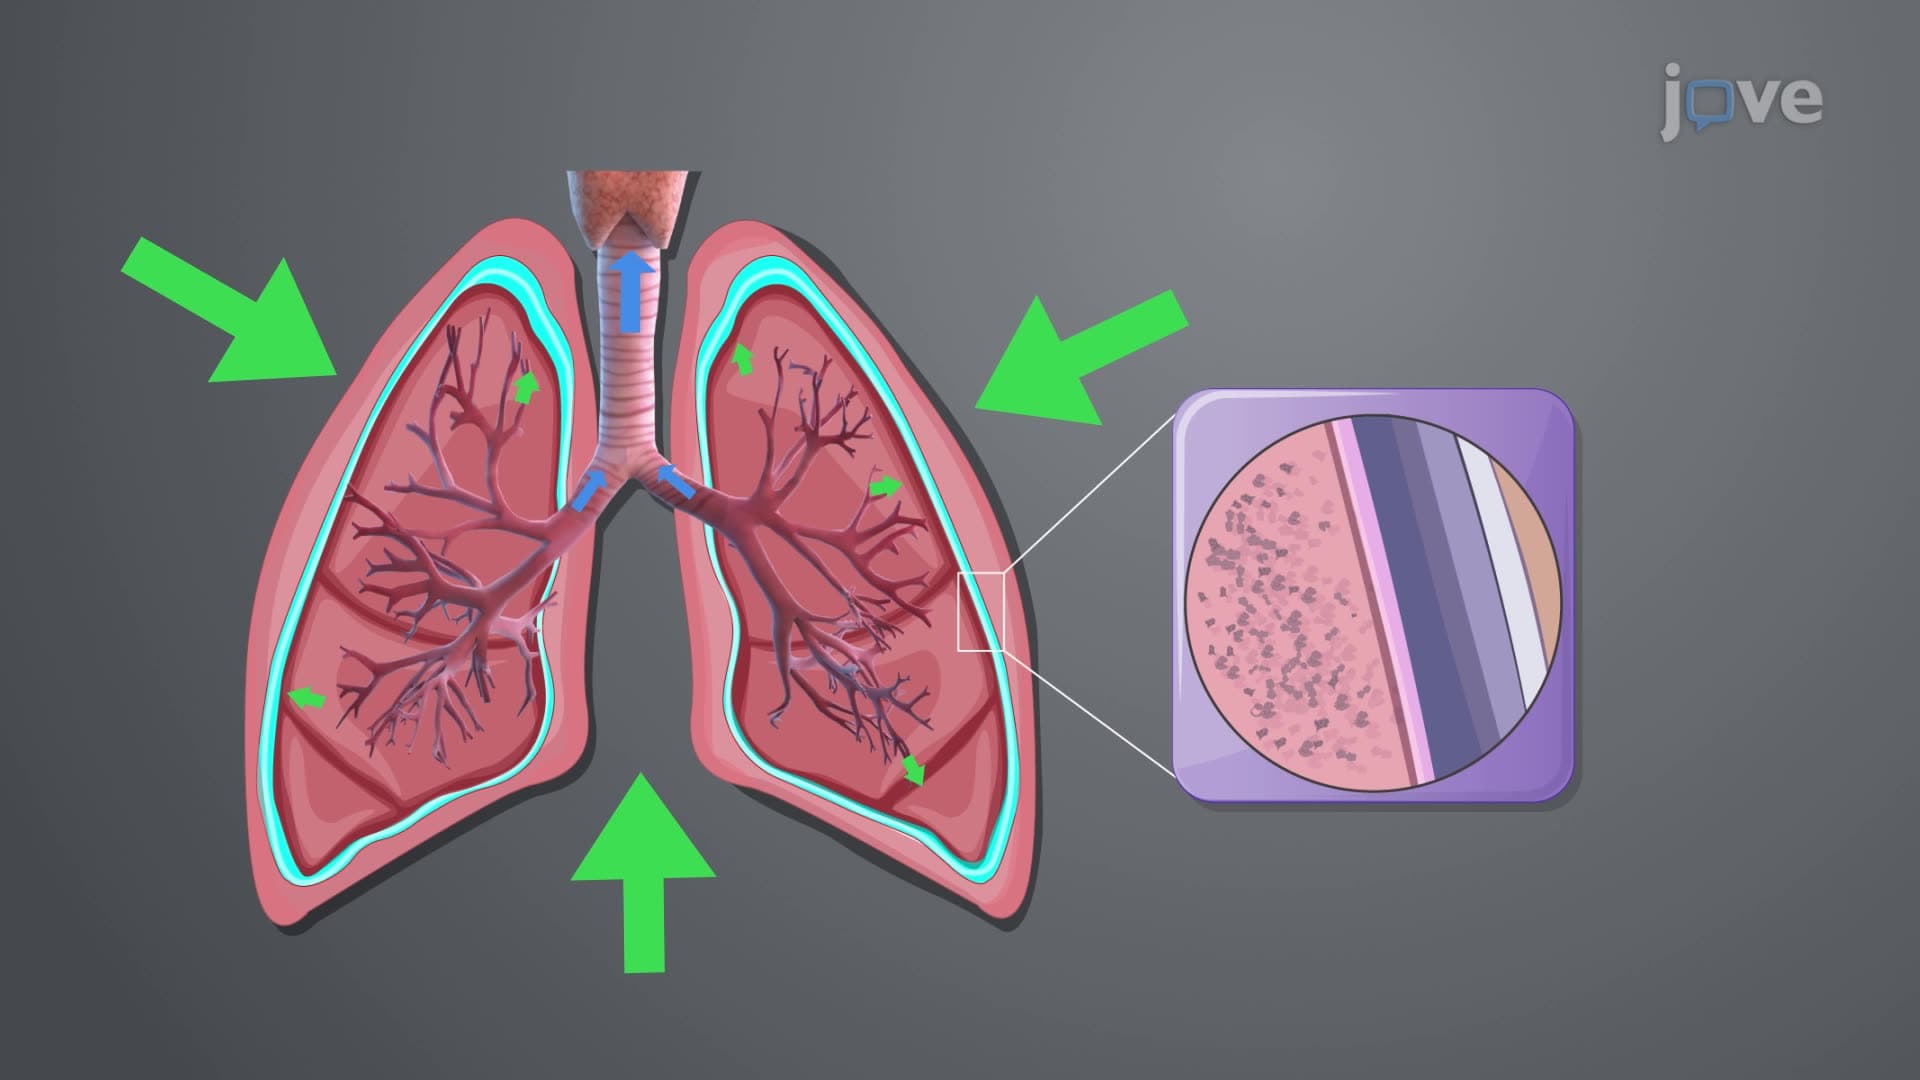
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...