Related Experiment Video
Updated: Mar 23, 2026


Rapid Screening of HIV Reverse Transcriptase and Integrase Inhibitors
Published on: April 9, 2014
[Tenofovir nephrotoxicity]
Corinne Isnard-Bagnis1, Blandine Aloy2, Gilbert Deray3
1Service d'urologie néphrologie transplantation, groupe hospitalier universitaire Pitié-Salpêtrière-Charles-Foix, 47-83, boulevard de l'Hôpital, 75651 Paris cedex 13, France; Université Pierre-et-Marie-Curie, 4, place Jussieu, 75005 Paris, France.

Abstract:
Tenofovir is currently the only commercially available nucleotidic reverse-transcriptase inhibitor of human immunodeficiency virus (HIV). It is overall very well tolerated and is prescribed to millions of patients-without any specific monitoring in developing countries. However a significant nephrotoxicity has been described. Acute nephrotoxicity is well characterized. Tenofovir is excreted in urine by proximal tubular epithelial cells. In case of cytoplasmic accumulation, tenofovir inhibits mitochondrial DNA polymerase γ, which causes a dysfunction of the respiratory chain, and in turn an alteration of the energy-deprived cells. Fanconi syndrome is the clinical expression of tenofovir acute toxicity, with sometimes an associated acute kidney failure. These abnormalities are usually reversible, at least partially, when tenofovir is discontinued. Tenofovir chronic toxicity has been debated but seems now well established by several cohort studies, even though it pathophysiology has yet to be understood. It manifests as an accelerated glomerular filtration rate decline in treated patients with no other renal abnormalities. The identification of this chronic toxicity was probably blurred by multiple cofactors, usually excluded from clinical trials. Simple measures such as dose adaptation to kidney function, identification of risk factors, and plasmatic tenofovir concentration monitoring can help decrease the risk of nephrotoxicity.
Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:15
Renal Drug Excretion: Overview
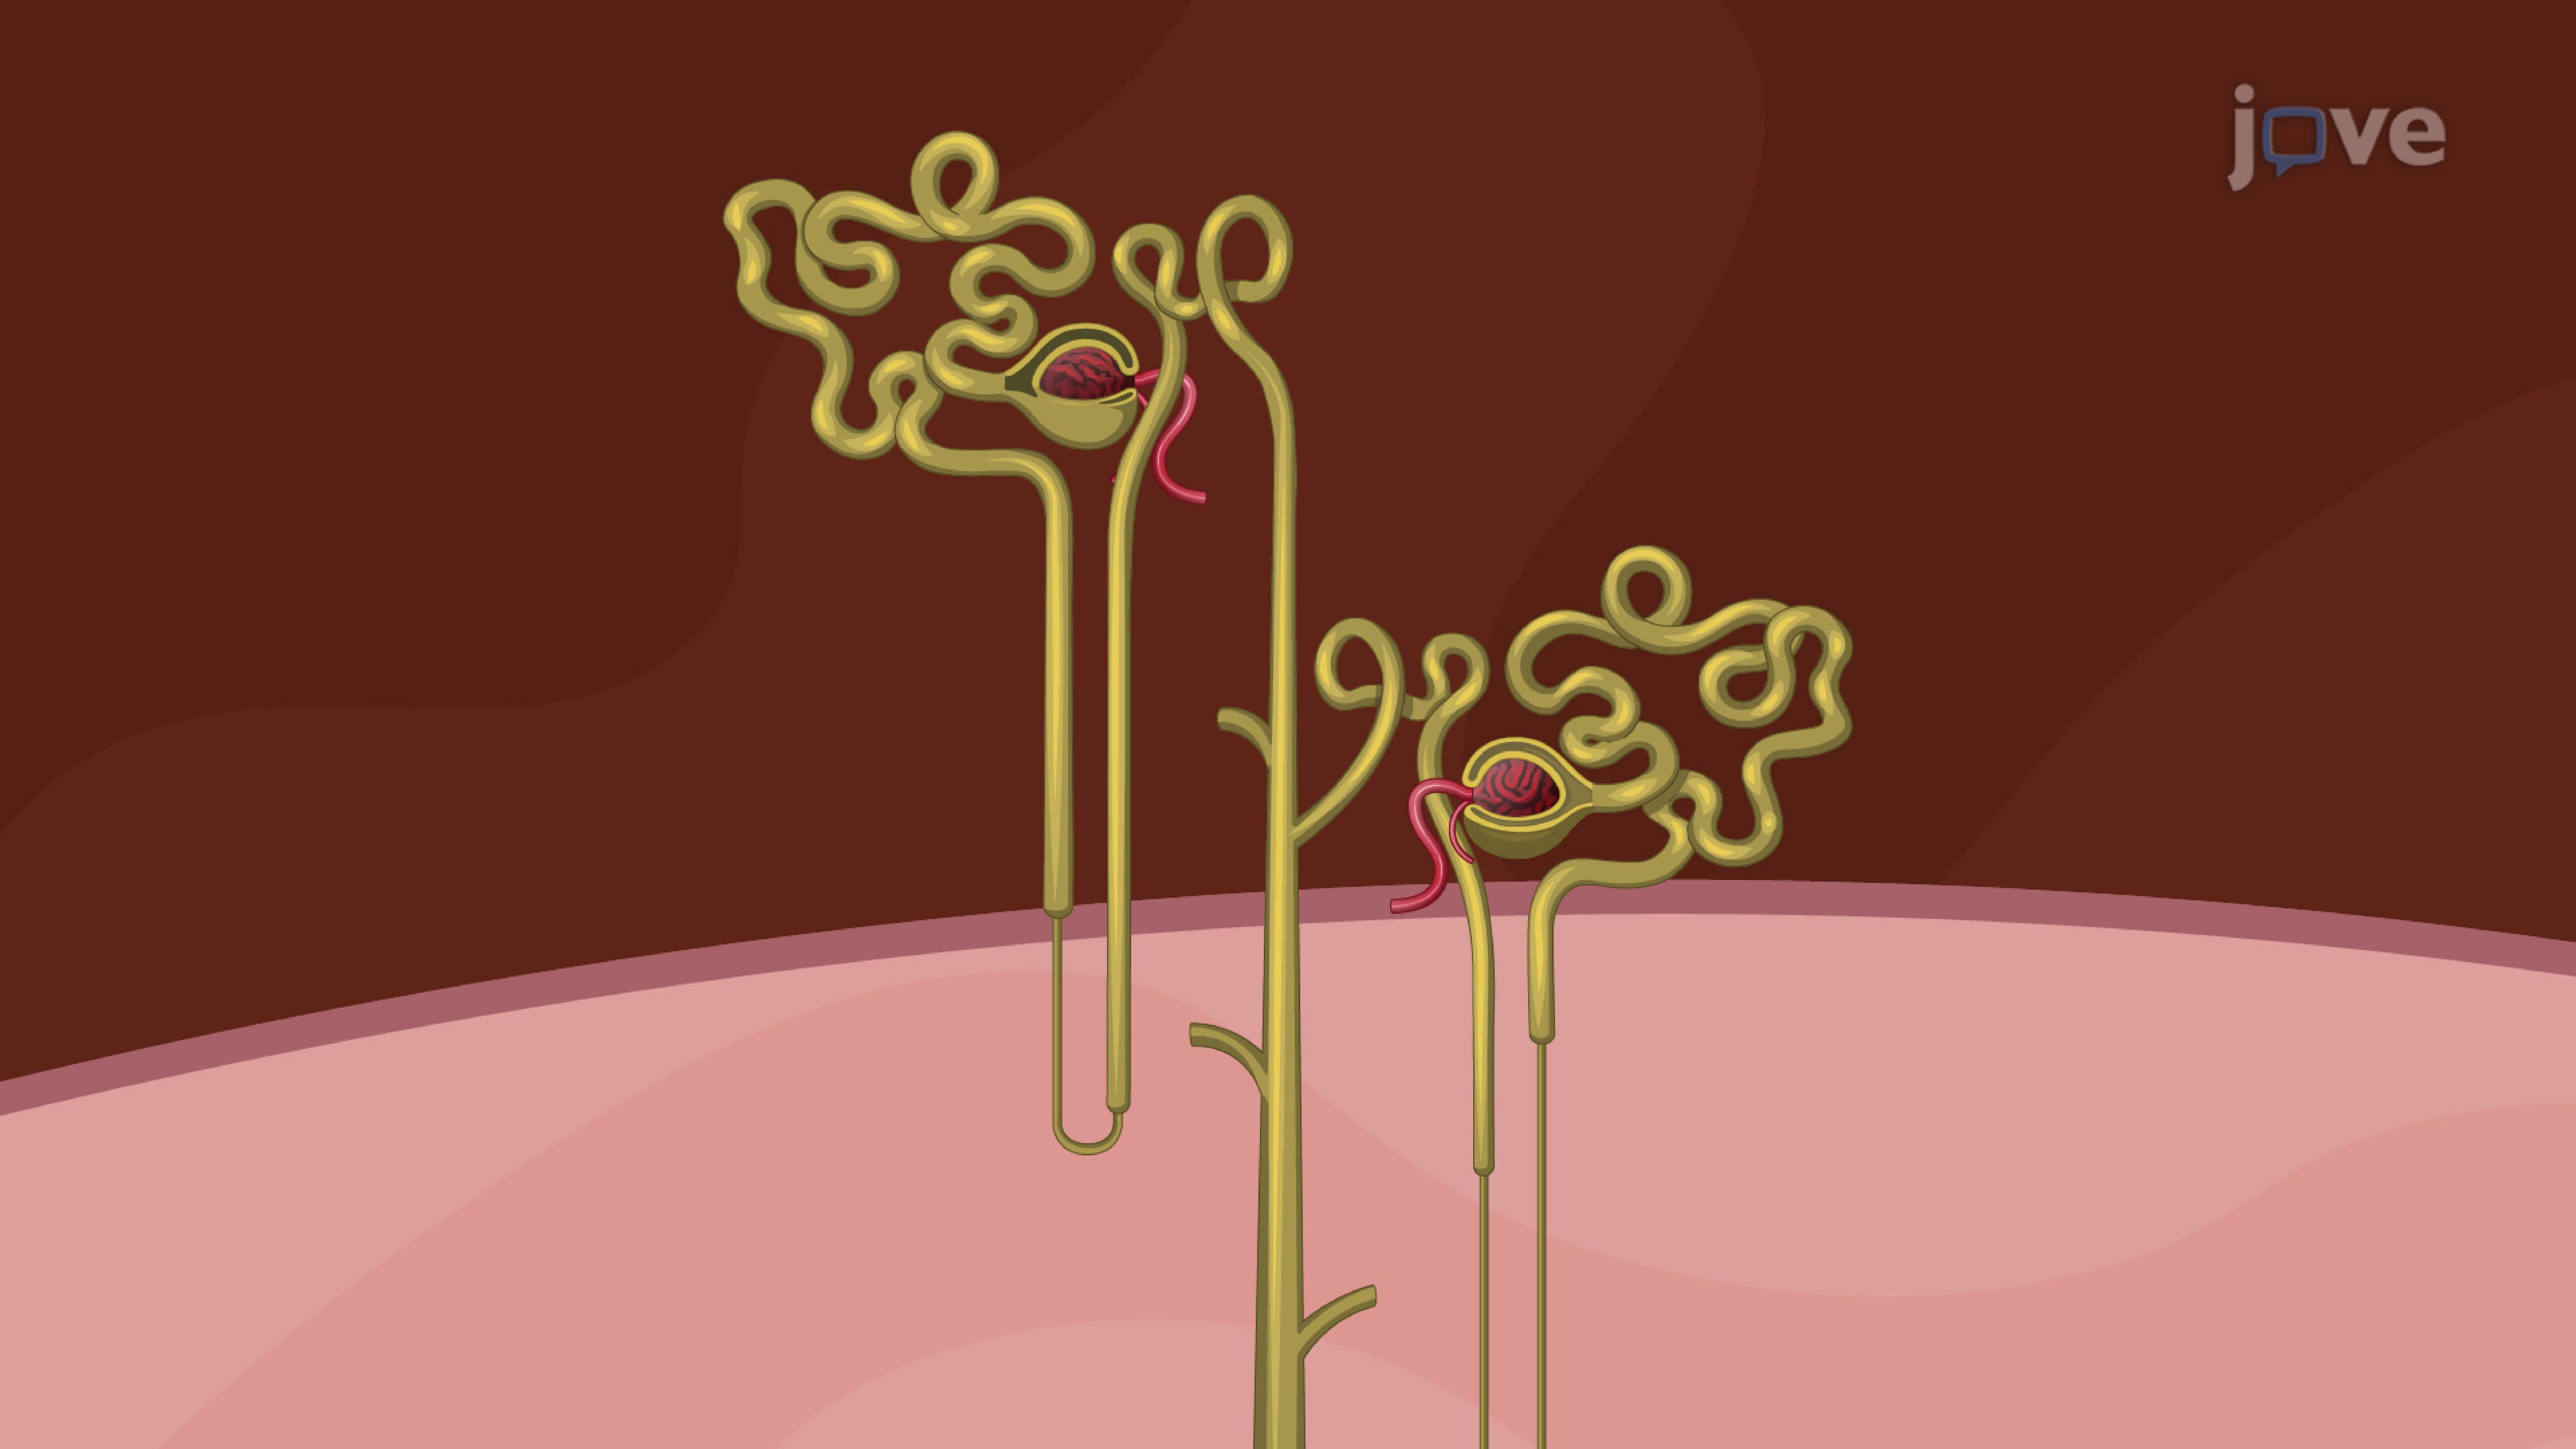
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...
 01:02
Renal Drug Excretion: Glomerular Filtration
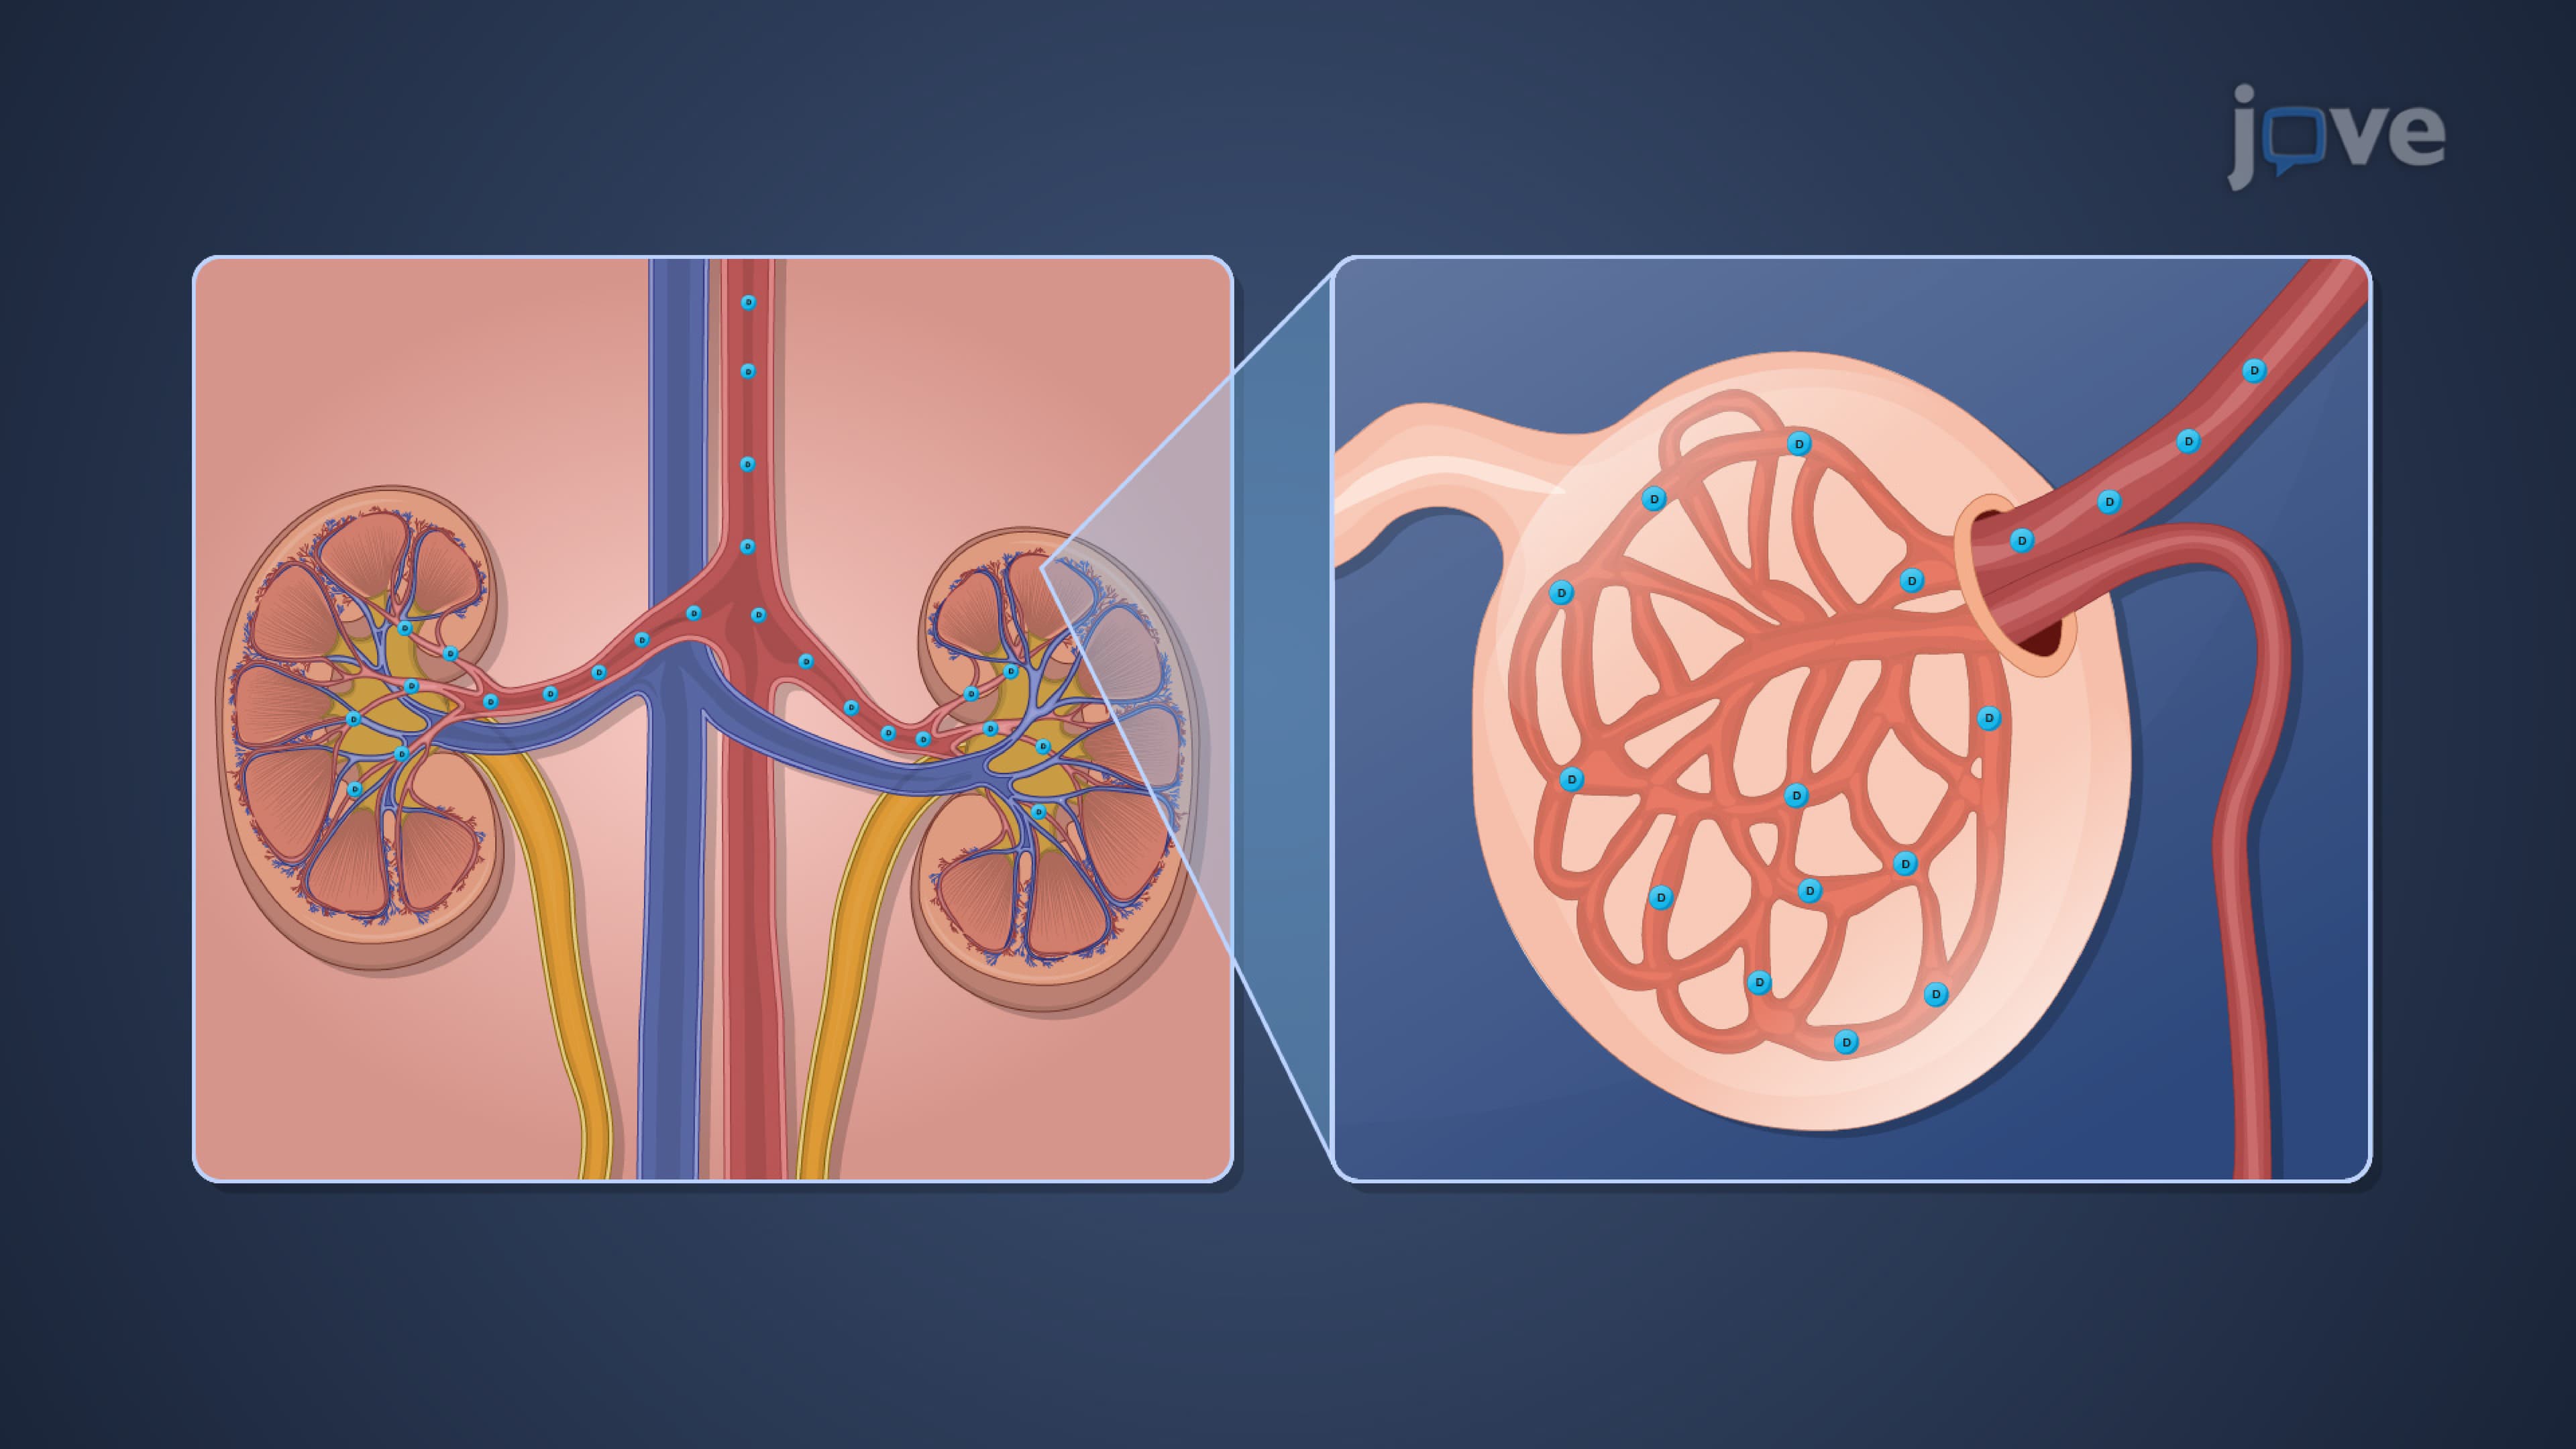
Drugs gain access to the kidney via the renal artery, which progressively branches off into afferent arterioles....
 01:28
Renal Drug Excretion: Tubular Secretion
 01:25
Renal Drug Excretion: Tubular Reabsorption
 01:26
Pharmacokinetics: Drug–Food and Drug–Viral Interactions