Related Experiment Video
Updated: Mar 23, 2026
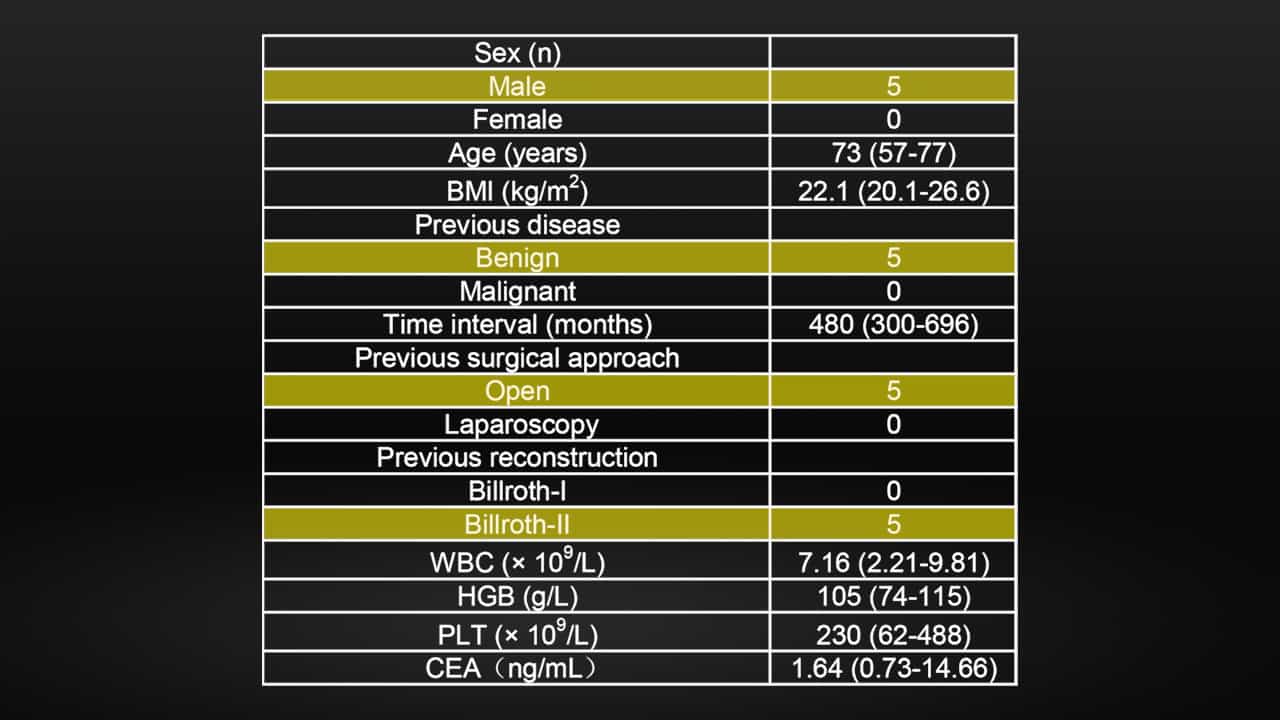
Laparoscopic Radical Gastrectomy for Remnant Gastric Cancer
Published on: October 31, 2025
Laparoscopic gastrectomy versus open gastrectomy for elderly patients with gastric cancer: a systematic review and
Jin-fa Wang1, Song-ze Zhang1, Neng-yun Zhang1
1Department of General Surgery, Yinzhou People's Hospital, Yinzhou Hospital Affiliated to Medical School of Ningbo University, 251 Baizhang Road, Ningbo, 315040, Zhejiang, People's Republic of China.

Background:
The objective of this study was to evaluate the feasibility, safety, and potential benefits of laparoscopic gastrectomy (LG) comparing with open gastrectomy (OG) in elderly population.
Methods:
Studies comparing LG with OG for elderly population with gastric cancer, published between January 1994 and July 2015, were identified in the PubMed, Embase, and ISI Web of Science databases. Operative outcomes (intraoperative blood loss, operative time, and the number of lymph nodes harvested) and postoperative outcomes (time to first ambulation, time to first flatus, time to first oral intake, postoperative hospital stay, postoperative morbidity) were included and analyzed. The Newcastle-Ottawa Scale was used to assess the quality of the pooled study. A funnel plot was used to evaluate the publication bias.
Results:
Seven studies totaling 845 patients were included in the meta-analysis. LG in comparison to OG showed less intraoperative blood loss (weighted mean difference (WMD) -127.47; 95% confidence interval (CI) -202.79 to -52.16; P < 0.01), earlier time to first ambulation (WMD -2.07; 95% CI -2.84 to -1.30; P < 0.01), first flatus (WMD -1.04; 95% CI -1.45 to -0.63; P < 0.01), and oral intake (WMD -0.94; 95% CI -1.11 to -0.77; P < 0.01), postoperative hospital stay (WMD -5.26; 95% CI -7.58 to -2.93; P < 0.01), lower overall postoperative complication rate (odd ratio (OR) 0.39; 95% CI 0.28 to 0.55; P < 0.01), less surgical complications (OR 0.47; 95% CI 0.32 to 0.69; P < 0.01), medical complication (OR 0.35; 95% CI 0.22 to 0.56; P < 0.01), incisional complication (OR 0.40; 95% CI 0.19 to 0.85; P = 0.02), and pulmonary infection (OR 0.49; 95% CI 0.26 to 0.93; P = 0.03). No significant differences were observed between LG and OG for the number of harvested lymph nodes. However, LG had longer operative times (WMD 15.73; 95% CI 6.23 to 25.23; P < 0.01).
Conclusions:
LG is a feasible and safe approach for elderly patients with gastric cancer. Compared with OG, LG has less blood loss, faster postoperative recovery, and reduced postoperative morbidity.
More Related Videos
 03:32
Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
 10:31
Intraoperative Gastroscopy for Tumor Localization in Laparoscopic Surgery for Gastric Adenocarcinoma
Published on: August 9, 2016
