Related Experiment Video
Updated: Mar 23, 2026


Introduction of Intracapsular Rotary-cut Procedures IRCP: A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
Canadian Contraception Consensus (Part 3 of 4): Chapter 7--Intrauterine Contraception
Amanda Black1, Edith Guilbert2, Dustin Costescu3
1Ottawa ON.

Objective:
To provide guidelines for health care providers on the use of contraceptive methods to prevent pregnancy and on the promotion of healthy sexuality.
Outcomes:
Overall efficacy of cited contraceptive methods, assessing reduction in pregnancy rate, safety, ease of use, and side effects; the effect of cited contraceptive methods on sexual health and general well-being; and the relative cost and availability of cited contraceptive methods in Canada.
Evidence:
Published literature was retrieved through searches of Medline and The Cochrane Database from January 1994 to January 2015 using appropriate controlled vocabulary (e.g., contraception, sexuality, sexual health) and key words (e.g., contraception, family planning, hormonal contraception, emergency contraception). Results were restricted to systematic reviews, randomized control trials/controlled clinical trials, and observational studies published in English from January 1994 to January 2015. Searches were updated on a regular basis in incorporated in the guideline to June 2015. Grey (unpublished) literature was identified through searching the websites of health technology assessment and health technology-related agencies, clinical practice guideline collections, clinical trial registries, and national and international medical specialty societies.
Values:
The quality of the evidence in this document was rated using the criteria described in the Report of the Canadian Task Force on Preventive Health Care (Table 1). CHAPTER 7: INTRAUTERINE CONTRACEPTION:
Summary Statements:
1. Intrauterine contraceptives are as effective as permanent contraception methods. (II-2) 2. The use of levonorgestrel-releasing intrauterine system (LNG-IUS) 52 mg by patients taking tamoxifen is not associated with recurrence of breast cancer. (I) 3. Intrauterine contraceptives have a number of noncontraceptive benefits. The levonorgestrel-releasing intrauterine system (LNG-IUS) 52 mg significantly decreases menstrual blood loss (I) and dysmenorrhea. (II-2) Both the copper intrauterine device and the LNG-IUS significantly decrease the risk of endometrial cancer. (II-2) 4. The risk of uterine perforation decreases with inserter experience but is higher in postpartum and breastfeeding women. (II-2) 5. The risk of pelvic inflammatory disease (PID) is increased slightly in the first month after intrauterine contraceptive (IUC) insertion, but the absolute risk is low. Exposure to sexually transmitted infections and not the IUC itself is responsible for PID occurring after the first month of use. (II-2) 6. Nulliparity is not associated with an increased risk of intrauterine contraceptive expulsion. (II-2) 7. Ectopic pregnancy with an intrauterine contraceptive (IUC) is rare, but when a pregnancy occurs with an IUC in situ, it is an ectopic pregnancy in 15% to 50% of the cases. (II-2) 8. In women who conceive with an intrauterine contraceptive (IUC) in place, early IUC removal improves outcomes but does not entirely eliminate risks. (II-2) 9. Intrauterine contraceptives do not increase the risk of infertility. (II-2) 10. Immediate insertion of an intrauterine contraceptive (10 minutes postplacental to 48 hours) postpartum or post-Caesarean section is associated with a higher continuation rate compared with insertion at 6 weeks postpartum. (I) 11. Immediate insertion of an intrauterine contraceptive (IUC; 10 minutes postplacental to 48 hours) postpartum or post-Caesarean section is associated with a higher risk of expulsion. (I) The benefit of inserting an IUC immediately postpartum or post-Caesarean section outweighs the disadvantages of increased risk of perforation and expulsion. (II-C) 12. Insertion of an intrauterine contraceptive in breastfeeding women is associated with a higher risk of uterine perforation in the first postpartum year. (II-2) 13. Immediate insertion of an intrauterine contraceptive (IUC) post-abortion significantly reduces the risk of repeat abortion (II-2) and increases IUC continuation rates at 6 months. (I) 14. Antibiotic prophylaxis for intrauterine contraceptive insertion does not significantly reduce postinsertion pelvic infection. (I) RECOMMENDATIONS: 1. Health care professionals should be careful not to restrict access to intrauterine contraceptives (IUC) owing to theoretical or unproven risks. (III-A) Health care professionals should offer IUCs as a first-line method of contraception to both nulliparous and multiparous women. (II-2A) 2. In women seeking intrauterine contraception (IUC) and presenting with heavy menstrual bleeding and/or dysmenorrhea, health care professionals should consider the use of the levonorgestrel intrauterine system 52 mg over other IUCs. (I-A) 3. Patients with breast cancer taking tamoxifen may consider a levonorgestrel-releasing intrauterine system 52 mg after consultation with their oncologist. (I-A) 4. Women requesting a levonorgestrel-releasing intrauterine system or a copper-intrauterine device should be counseled regarding changes in bleeding patterns, sexually transmitted infection risk, and duration of use. (III-A) 5. A health care professional should be reasonably certain that the woman is not pregnant prior to inserting an intrauterine contraceptive at any time during the menstrual cycle. (III-A) 6. Health care providers should consider inserting an intrauterine contraceptive immediately after an induced abortion rather than waiting for an interval insertion. (I-B) 7. In women who conceive with an intrauterine contraceptive (IUC) in place, the diagnosis of ectopic pregnancy should be excluded as arly as possible. (II-2A) Once an ectopic pregnancy has been excluded, the IUC should be removed without an invasive procedure. The IUC may be removed at the time of a surgical termination. (II-2B) 8. In the case of pelvic inflammatory disease, it is not necessary to remove the intrauterine contraceptive unless there is no clinical improvement after 48 to 72 hours of appropriate antibiotic treatment. (II-2B) 9. Routine antibiotic prophylaxis for intrauterine contraceptive (IUC) insertion is not indicated. (I-B) Health care providers should perform sexually transmitted infection (STI) testing in women at high risk of STI at the time of IUC insertion. If the test is positive for chlamydia and/or gonorrhea, the woman should be appropriately treated postinsertion and the IUC can remain in situ. (II-2B) 10. Unscheduled bleeding in intrauterine contraception users, when persistent or associated with pelvic pain, should be investigated to rule out infection, pregnancy, gynecological pathology, expulsion or malposition. (III-A)
More Related Videos
 03:30
Author Spotlight: Advancing Pelvic Prolapse Treatment with a Non-Mesh Approach using Laparoscopic Pectopexy
Published on: October 25, 2024
 05:21
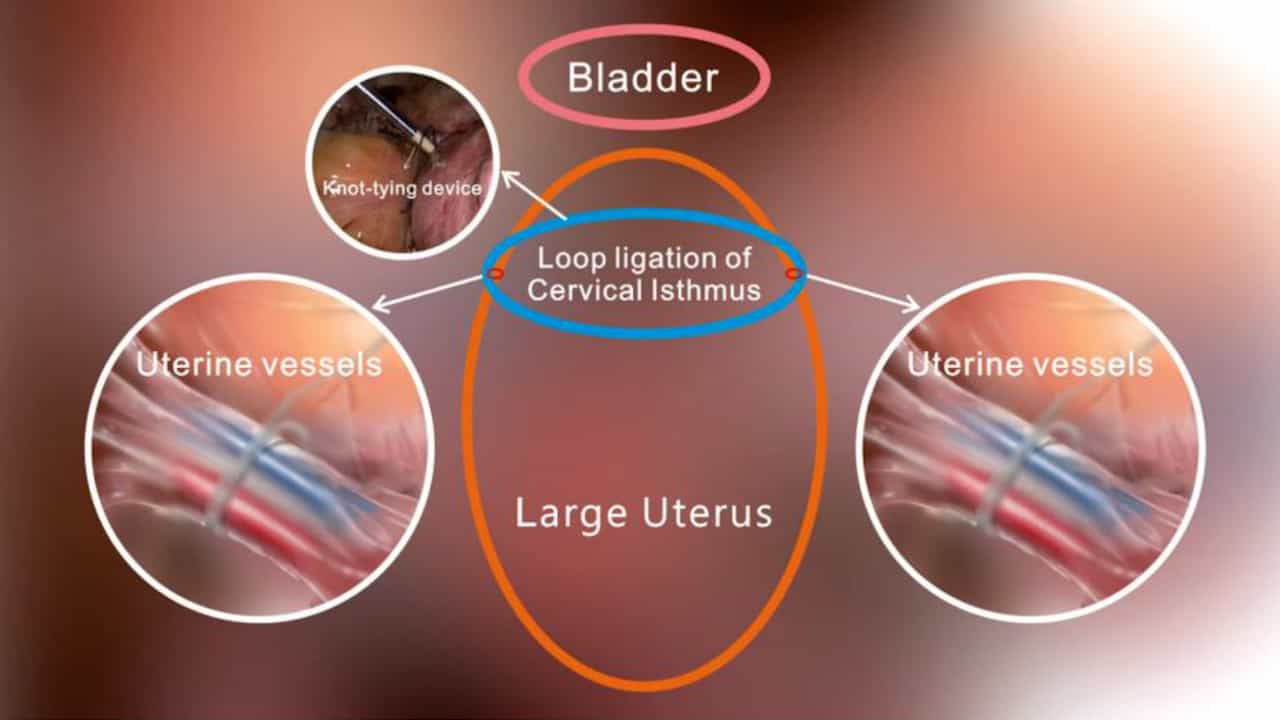
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Related Concept Videos
 01:21
Intrauterine Drug Delivery Systems
 01:22
Birth Control Methods
 01:24
In Vitro Fertilization
The IVF process begins with ovarian stimulation, during which reproductive endocrinologists prescribe hormonal medications to stimulate the ovaries to produce multiple eggs instead of the single...
 01:24
Gonadal and Placental Hormones
In males, testosterone is the primary gonadal androgen. It plays a central role in the maturation of male reproductive organs — the penis and testes. Additionally, testosterone is instrumental in the development of secondary sexual characteristics — a deep voice as well as facial and pubic hair...
 01:27
Ovarian Cycle
 01:28
Infertility in Females
Endometriosis, a condition characterized by abnormal growth of...