Related Experiment Video
Updated: Mar 23, 2026

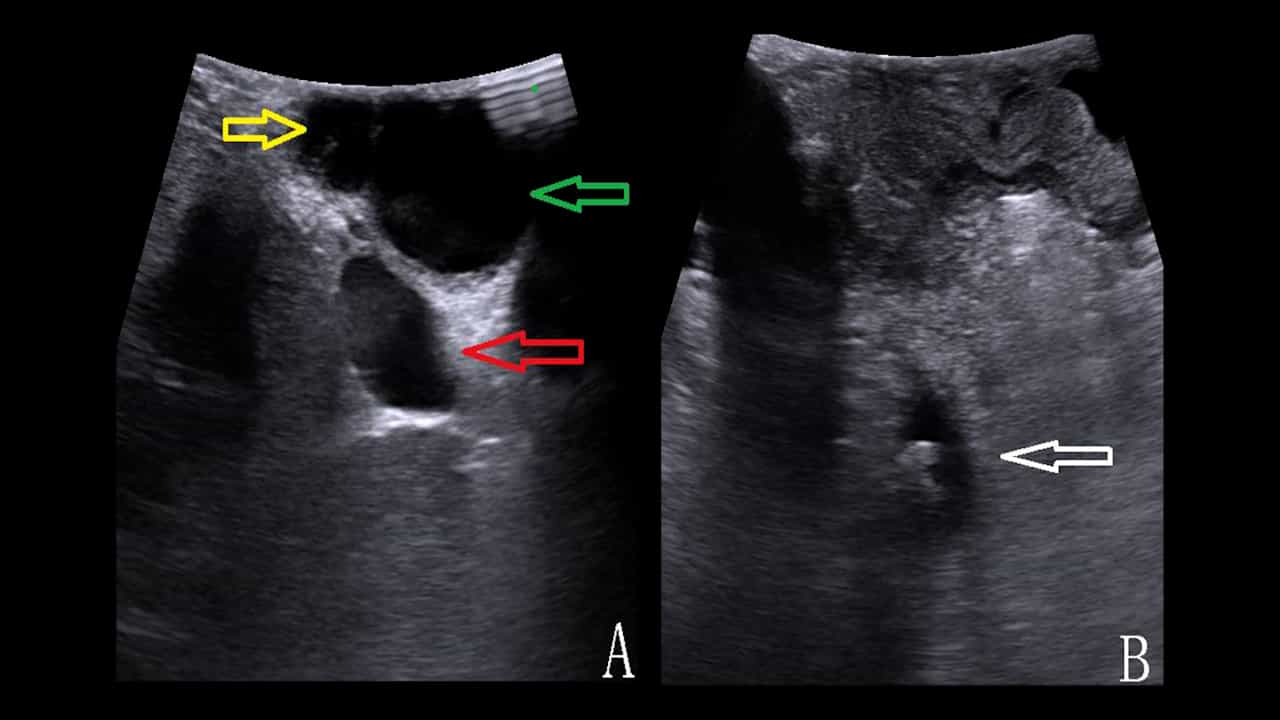
Laparoscopic Common Bile Duct Exploration in Patients with a Previous History of Biliary Tract Surgery
Published on: February 10, 2023
Pilot Randomized Controlled Trial of Laparoscopic Cholecystectomy vs Active Nonoperative Therapy for the Treatment
Bryan K Richmond1, Caresse Grodman2, Jerri Walker2
1Department of Surgery, West Virginia University/Charleston Division, Charleston, WV.

Background:
Despite widespread adoption by the surgical community, high-quality prospective data supporting the practice of laparoscopic cholecystectomy (LC) for the treatment of biliary dyskinesia (BD) are lacking.
Study Design:
Adult patients meeting criteria for diagnosis of BD (Rome III symptoms, normal ultrasound, gallbladder ejection fraction < 38%) were randomized to either LC or a trial of nonoperative (NO) therapy with a low-dose neuromodulator (amitriptyline 25 mg/day). Patients in the NO arm were allowed to cross over to the surgical arm and remain in the study for any reason. Besides collection of basic demographics and medical/surgical history, patients were administered a standardized quality of life (QOL) assessment (Short Form-8) and a symptom-specific questionnaire (Rome III criteria) at enrollment and monthly through the study to assess the effect of treatment on biliary symptoms and overall QOL.
Results:
Thirty patients were enrolled over 12 months (15 LC, 15 NO). In the LC group, 13 underwent LC, 1 refused surgery, 1 withdrew. In the NO group, 14 crossed over to the LC group (13 of whom had LC), yielding 26 patients who underwent LC. The SF-8 physical scores (PCS-8) were significantly improved at both the first and last follow-up visits (p < 0.0001, p = 0.0003, respectively). The SF-8 mental scores (MCS-8) were also significantly improved at both the first and last follow-up visits (p = 0.0187, p = 0.0017, respectively). With median follow-up of 12 months (range 3 to 14 months), all 26 reported relief of pain.
Conclusions:
This pilot study raises doubts regarding the feasibility of a randomized trial, presumably due to both clinician and patient bias toward LC and the lack of "gold-standard" nonoperative treatments. However, these prospective data indicate that, with careful patient selection (standardized symptom criteria/imaging methodology), LC results in pain relief and significant improvement in QOL in BD patients. Further prospective study of these findings is warranted.