Related Experiment Video
Updated: Mar 22, 2026
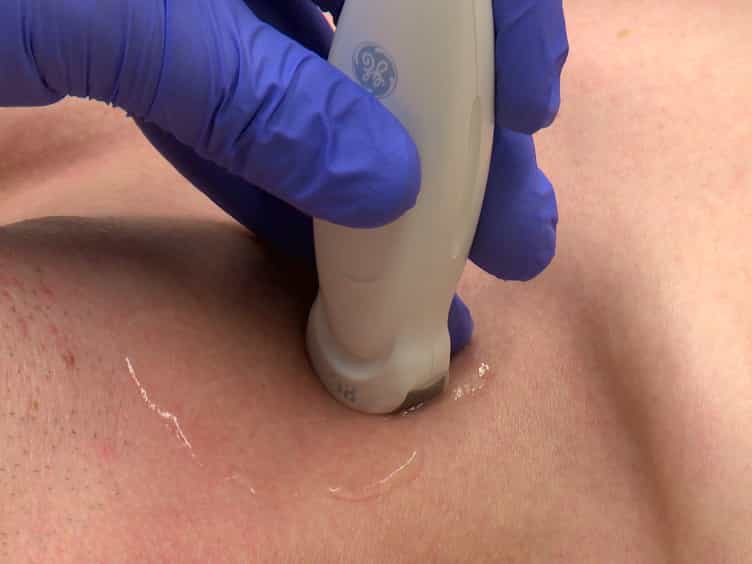

The Supraclavicular Fossa Ultrasound View for Central Venous Catheter Placement and Catheter Change Over Guidewire
Published on: December 23, 2014
Ultrasound-guided central venous catheter placement increases success rates in pediatric patients: a meta-analysis
Christine S M Lau1,2, Ronald S Chamberlain1,2,3
1Department of Surgery, Saint Barnabas Medical Center, Livingston, New Jersey.

Insights
Ultrasound-guided central venous catheter (CVC) insertion significantly improves success rates and reduces the number of attempts needed in pediatric patients. This method enhances patient safety and should be standard practice for children.
Area of Science:
- Pediatric critical care
- Medical technology
- Interventional procedures
Background:
- Real-time ultrasound (US) guidance for central venous catheter (CVC) insertion is established in adults for improving success and reducing complications.
- Limited and conflicting literature exists on US-guided CVC placement in pediatric patients.
Purpose of the Study:
- To examine the efficacy and safety of US-guided CVC placement in pediatric patients through a meta-analysis.
- To compare US-guided CVC insertion with traditional landmark (LM)-guided insertion in children.
Main Methods:
- A systematic literature search was conducted for randomized control trials (RCTs) comparing US-guided and LM-guided CVC insertion in patients under 18 years.
- Key outcomes analyzed included cannulation success rate, number of attempts, accidental arterial puncture, and time to cannulation.
Main Results:
- Analysis of eight RCTs with 760 patients revealed that US-guided CVC insertion significantly increased success rates by 31.8%.
- The mean number of attempts required was significantly decreased with US guidance.
- A trend towards reduced accidental arterial puncture was observed, with no significant difference in cannulation time.
Conclusions:
- US-guided CVC placement demonstrates significantly higher success rates and fewer attempts in pediatric patients.
- The findings support the utilization of US-guided CVC insertion to improve outcomes in pediatric care.
Background:
Real-time ultrasound (US) guidance for central venous catheter (CVC) insertion has been shown to increase cannulation success rates and reduce complications in adults. Literature regarding US-guided CVC placement in children remains limited and conflicting. This meta-analysis examines the efficacy and safety of US-guided CVC placement among pediatric patients.
Methods:
A comprehensive literature search of all published randomized control trials (RCTs) comparing the use of real-time US-guided CVC insertion with anatomic landmark (LM)-guided CVC insertion in pediatric patients <18 y of age was conducted. Outcomes analyzed were cannulation success rate, number of attempts required, incidence of accidental arterial puncture, and time to cannulation.
Results:
Eight RCTs involving 760 patients were analyzed. US-guided CVC insertion significantly increased success rates by 31.8% and decreased the mean number of attempts required. A trend toward a decrease in the risk of accidental arterial puncture with the use of US-guided CVC insertion was also observed. US-guided CVC insertion was not associated with a significant difference in time required for CVC placement.
Conclusion:
US-guided CVC placement is associated with significantly higher success rates and decreased mean number of attempts required for cannulation. US-guided CVC insertion improves success rates, and should be utilized in pediatric patients.
More Related Videos
Related Concept Videos
 01:27
Parentral Nutrition: Centeral and Peripheral Parental Nutrition
PN can be administered through two primary routes:
1. Central Parenteral Nutrition (CPN):
CPN involves delivering a high concentration of nutrients through a large vein. This is typically achieved using a Peripherally Inserted Central Catheter (PICC) or,...
 01:29
Venous Thrombosis III: Interprofessional Care