Related Experiment Video
Updated: Mar 22, 2026
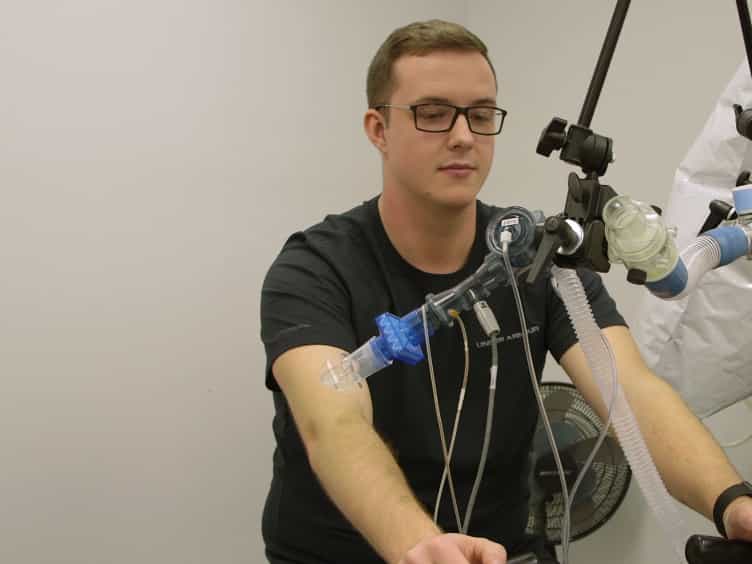

Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Decreased arterial PO2, not O2 content, increases blood flow through intrapulmonary arteriovenous anastomoses at rest
Joseph W Duke1, James T Davis2, Benjamin J Ryan3
1Ohio University, Division of Exercise Physiology, Athens, OH, USA.

Key Points:
The mechanism(s) that regulate hypoxia-induced blood flow through intrapulmonary arteriovenous anastomoses (QIPAVA ) are currently unknown. Our previous work has demonstrated that the mechanism of hypoxia-induced QIPAVA is not simply increased cardiac output, pulmonary artery systolic pressure or sympathetic nervous system activity and, instead, it may be a result of hypoxaemia directly. To determine whether it is reduced arterial PO2 (PaO2) or O2 content (CaO2) that causes hypoxia-induced QIPAVA , individuals were instructed to breathe room air and three levels of hypoxic gas at rest before (control) and after CaO2 was reduced by 10% by lowering the haemoglobin concentration (isovolaemic haemodilution; Low [Hb]). QIPAVA , assessed by transthoracic saline contrast echocardiography, significantly increased as PaO2 decreased and, despite reduced CaO2 (via isovolaemic haemodilution), was similar at iso-PaO2. These data suggest that, with alveolar hypoxia, low PaO2 causes the hypoxia-induced increase in QIPAVA , although where and how this is detected remains unknown.
Abstract:
Alveolar hypoxia causes increased blood flow through intrapulmonary arteriovenous anastomoses (QIPAVA ) in healthy humans at rest. However, it is unknown whether the stimulus regulating hypoxia-induced QIPAVA is decreased arterial PO2 (PaO2) or O2 content (CaO2). CaO2 is known to regulate blood flow in the systemic circulation and it is suggested that IPAVA may be regulated similar to the systemic vasculature. Thus, we hypothesized that reduced CaO2 would be the stimulus for hypoxia-induced QIPAVA . Blood volume (BV) was measured using the optimized carbon monoxide rebreathing method in 10 individuals. Less than 5 days later, subjects breathed room air, as well as 18%, 14% and 12.5% O2 , for 30 min each, in a randomized order, before (CON) and after isovolaemic haemodilution (10% of BV withdrawn and replaced with an equal volume of 5% human serum albumin-saline mixture) to reduce [Hb] (Low [Hb]). PaO2 was measured at the end of each condition and QIPAVA was assessed using transthoracic saline contrast echocardiography. [Hb] was reduced from 14.2 ± 0.8 to 12.8 ± 0.7 g dl(-1) (10 ± 2% reduction) from CON to Low [Hb] conditions. PaO2 was no different between CON and Low [Hb], although CaO2 was 10.4%, 9.2% and 9.8% lower at 18%, 14% and 12.5% O2 , respectively. QIPAVA significantly increased as PaO2 decreased and, despite reduced CaO2, was similar at iso-PaO2. These data suggest that, with alveolar hypoxia, low PaO2 causes the hypoxia-induced increase in QIPAVA . Whether the low PO2 is detected at the carotid body, airway and/or the vasculature remains unknown.
Related Concept Videos
 01:27
Oxygen Transport in the Blood
 01:19
Overview of Pulmonary Circulation
The process begins with the right ventricle of the heart pumping deoxygenated blood into the pulmonary trunk. This large vessel extends about 5 centimeters before splitting into the left and right pulmonary arteries. These arteries...
 01:24
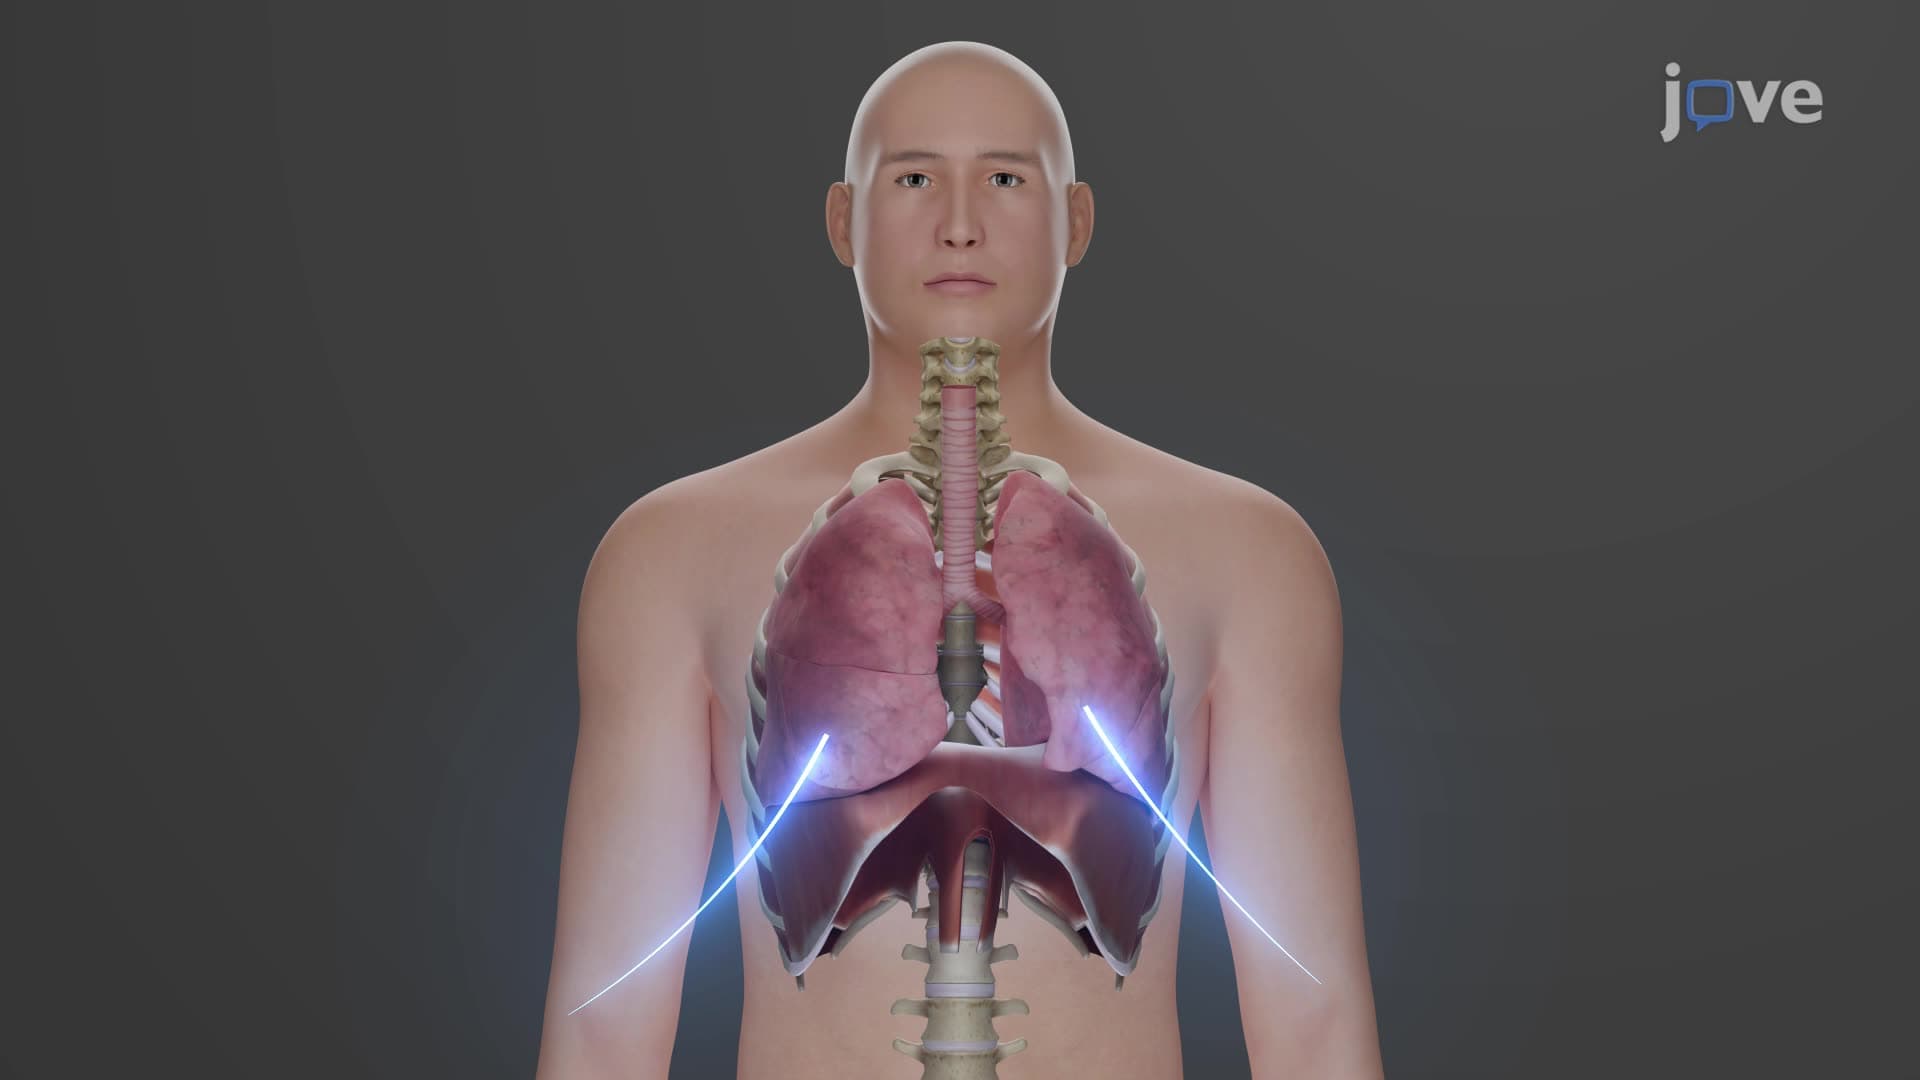
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:31
Chemical Factors Affecting Respiration Centers
CO2 has a potent influence on respiration and is strictly regulated....
 01:20
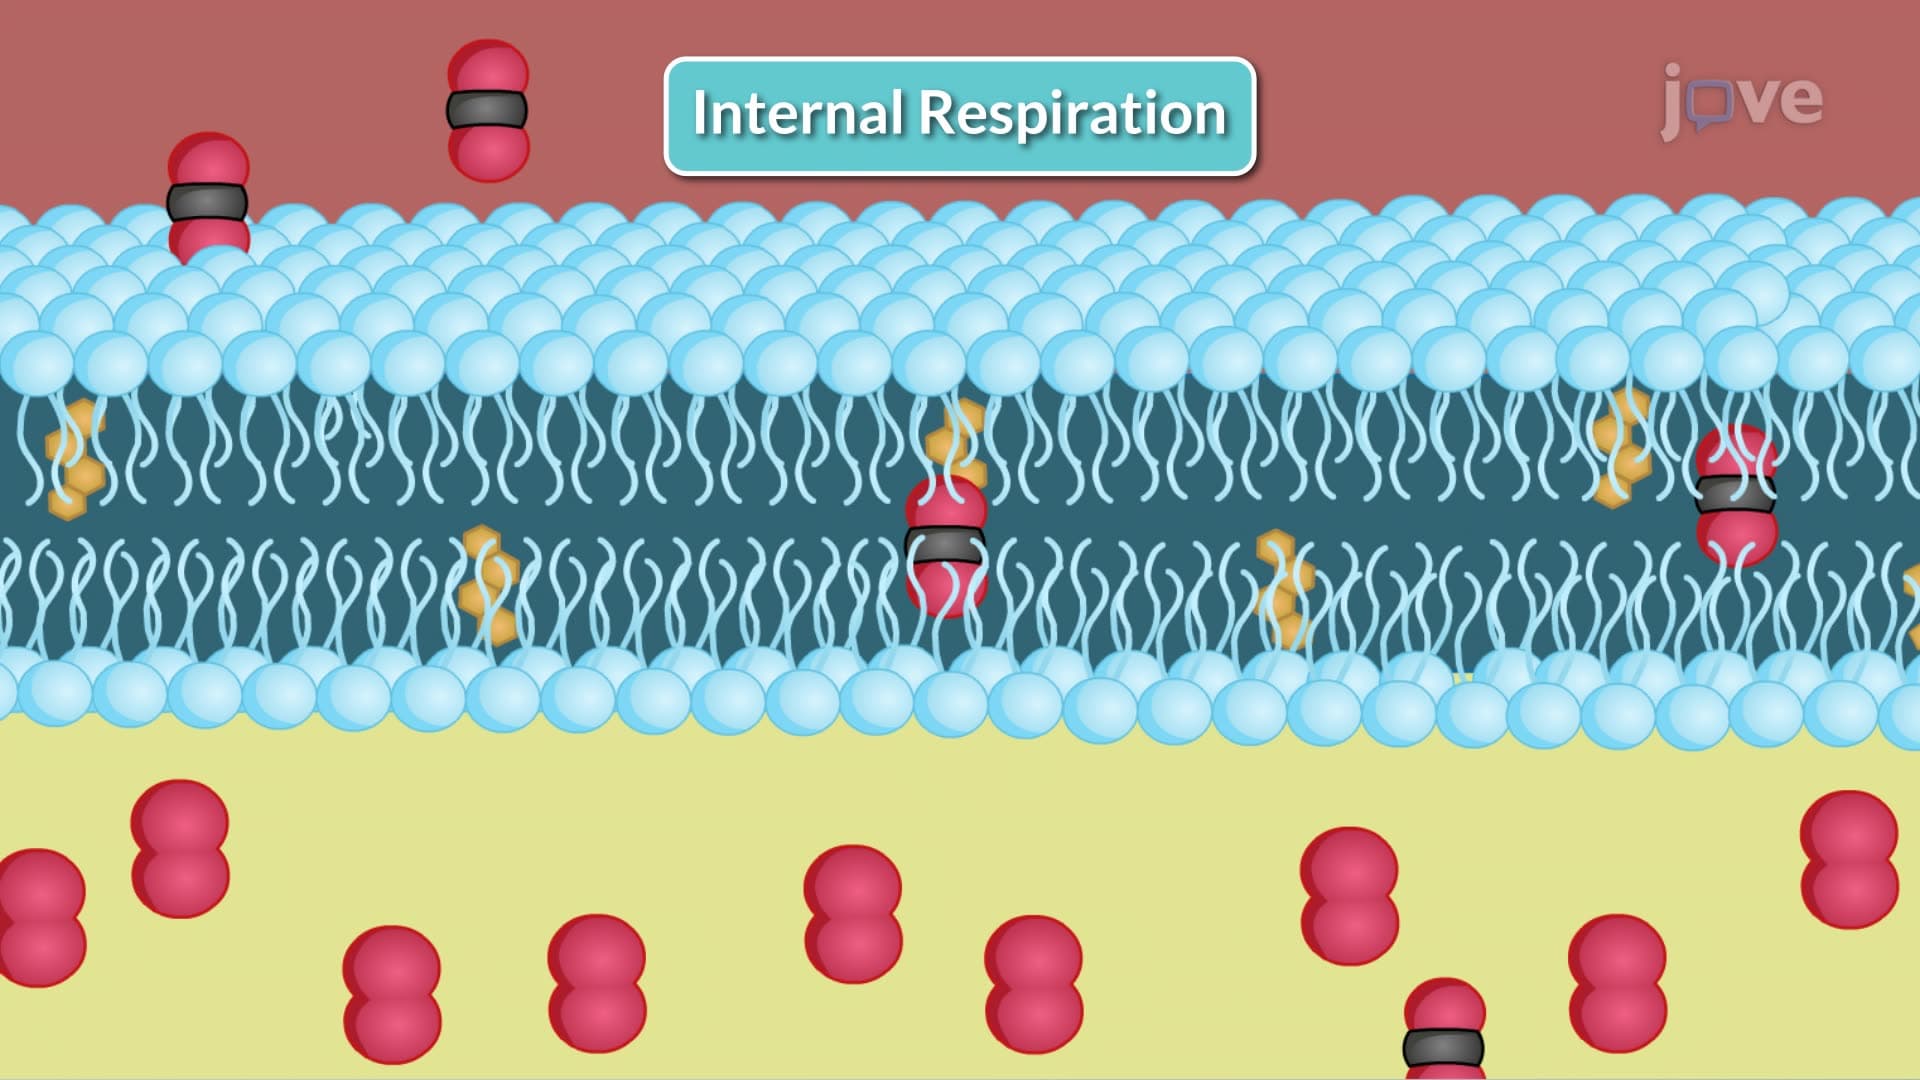
Respiration and Gaseous Exchange
Respiration involves the exchange of gases, especially oxygen (O2) and carbon dioxide (CO2), between the alveoli and body cells, a process facilitated by blood circulation. As a result, the cardiovascular system, which involves...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include: