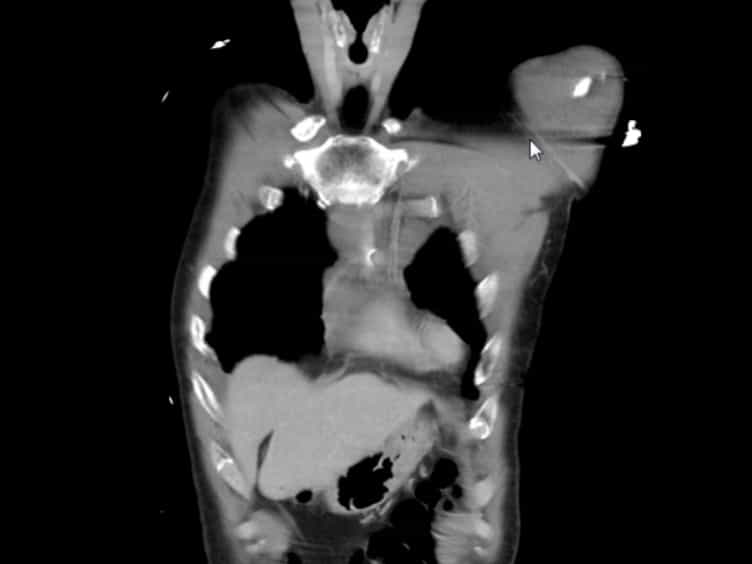
In patients with acute flail chest does surgical rib fixation improve outcomes in terms of morbidity and mortality?
Katharina Schulte1, Donald Whitaker2, Rizwan Attia3
1Department of Cardiothoracic Surgery, King's College Hospital, London, UK Department of General, Visceral and Vascular Surgery, Minimally Invasive Surgery, St. Hedwig Hospital, Berlin, Germany.

Abstract:
A best evidence topic in cardiothoracic surgery was written according to a structured protocol. The question addressed was: In patients with acute flail chest does surgical rib fixation improve outcomes in terms of morbidity and mortality? Using the reported search criteria, 137 papers were found. Of these, 11 papers (N = 1712) represent the best evidence to answer the clinical question, and include one meta-analysis, two randomized, controlled trials (RCTs), five retrospective cohort studies and two case-control series. In-hospital mortality was lower for the surgical group in the meta-analysis [n = 582, odds ratio (OR) 0.31 (0.20-0.48), risk difference (RD) 0.19 (0.13-0.26), number needed to treat (NNT) 5] as well as significant decreases in ventilator days [mean 8 days, 95% confidence interval (CI) 5-10 days] and intensive care unit stay (mean 5 days, 95% CI 2-8 days). A reduction was found for septicaemia [n = 345, OR 0.36 (0.19-0.71), RD 0.14 (0.56-0.23), NNT 7], pneumonia [n = 616, OR 0.18 (0.11-0.32), RD 0.31 (0.21-0.41), NNT 3, P = 0.001], tracheostomy (OR 0.06, 95% CI 0.02-0.20) and chest wall deformity [n = 228, OR 0.11 (0.02-0.60), RD 0.30 (0.00-0.60), NNT 3]. Eight studies (n = 1015) had a shorter duration of mechanical ventilation following surgery. A reduction in intensive care unit stay was demonstrated in four papers (n = 389, 3.1-9.0 days), whereas a further three papers described a reduction in the duration of hospitalization (n = 489, 4-10.6 days). Three studies (n = 166) showed a lower risk for tracheostomy. One retrospective cohort study estimated lower total treatment costs in surgically treated patients ($32 300 vs $37 100) although not statistically significant. One retrospective case-control study described a lower risk for reintubation (n = 50, P = 0.034) and home oxygen requirements (n = 50, P = 0.034). One cohort study showed a better APACHE II score 14 days after trauma in the surgical group (P = 0.02). Surgical stabilization of flail chest in thoracic trauma patients has beneficial effects with respect to reduced ventilatory support, shorter intensive care and hospital stay, reduced incidence of pneumonia and septicaemia, decreased risk of chest deformity and an overall reduced mortality when compared with patients who received non-operative management.
More Related Videos

Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:20
The Thoracic Cage: Ribs
Parts of a Typical Rib
A typical rib has a head, neck, and body. The posterior end of the rib is called the head, followed by a narrow neck. The head articulates primarily with the costal...
 01:27
Pneumothorax-II
Clinical Manifestations: