

Anatomic Variability of the Upper Mediastinal Lymph Node Level VII
Dana M Hartl1, Ingrid Breuskin2, Haïtham Mirghani2
1Department of Head and Neck Oncology, Thyroid Surgery Unit, Institut de Cancérologie Gustave Roussy and Paris-Sud University, 114, Rue Edouard Vaillant, 94805, Villejuif Cedex, France. dana.hartl@gustaveroussy.fr.

Objective:
Lymph node level VII, between the sternal notch and the innominate artery, is a frequent site of lymph node metastases in thyroid cancer. The objective of this study was to determine the cranial-caudal dimensions of level VII in patients undergoing central neck dissection for thyroid cancer and its accessibility through a neck incision only.
Patients And Methods:
Consecutive patients undergoing central neck dissection for thyroid cancer, with no previous neck dissection, mediastinal or thoracic surgery. The innominate artery was identified and the distance between the sternal notch and the upper border of the artery was measured to the nearest .5 mm. The sizes of level VII were compared with respect to age, sex, height, body mass index, type of neck dissection (therapeutic or prophylactic), and the incidence of previous thyroidectomy.
Results:
One-hundred-one consecutive patients (65 women, 36 men, mean age 44 years (range 15-87) underwent prophylactic (n = 55) or therapeutic (n = 46) bilateral central compartment neck dissection. Level VII was accessible via the horizontal neck incision in all cases. Sizes of level VII ranged from 6 cm above the sternal notch to 35 mm below the sternal notch, with a mean distance of 3.5 mm below the sternal notch. The innominate artery was at the level of the sternal notch in 29 patients, and cranial to the sternal notch in 20 cases. No statistical relationship with age, sex, therapeutic/prophylactic neck dissection, previous surgery, body mass index or height was found.
Conclusions:
The maximal distance below the sternal notch was 35 mm. Level VII did not exist in 49 % of patients, and was less than 25 mm caudal to the sternal notch in 95 % of cases. Distinguishing level VII from level VI in thyroid cancer surgery may not be pertinent, due to the ease of access via a classic horizontal neck incision and the small sizes of level VII in the majority of patients.


Related Concept Videos
 01:23
Detailed Structure and Function of Lymph Nodes
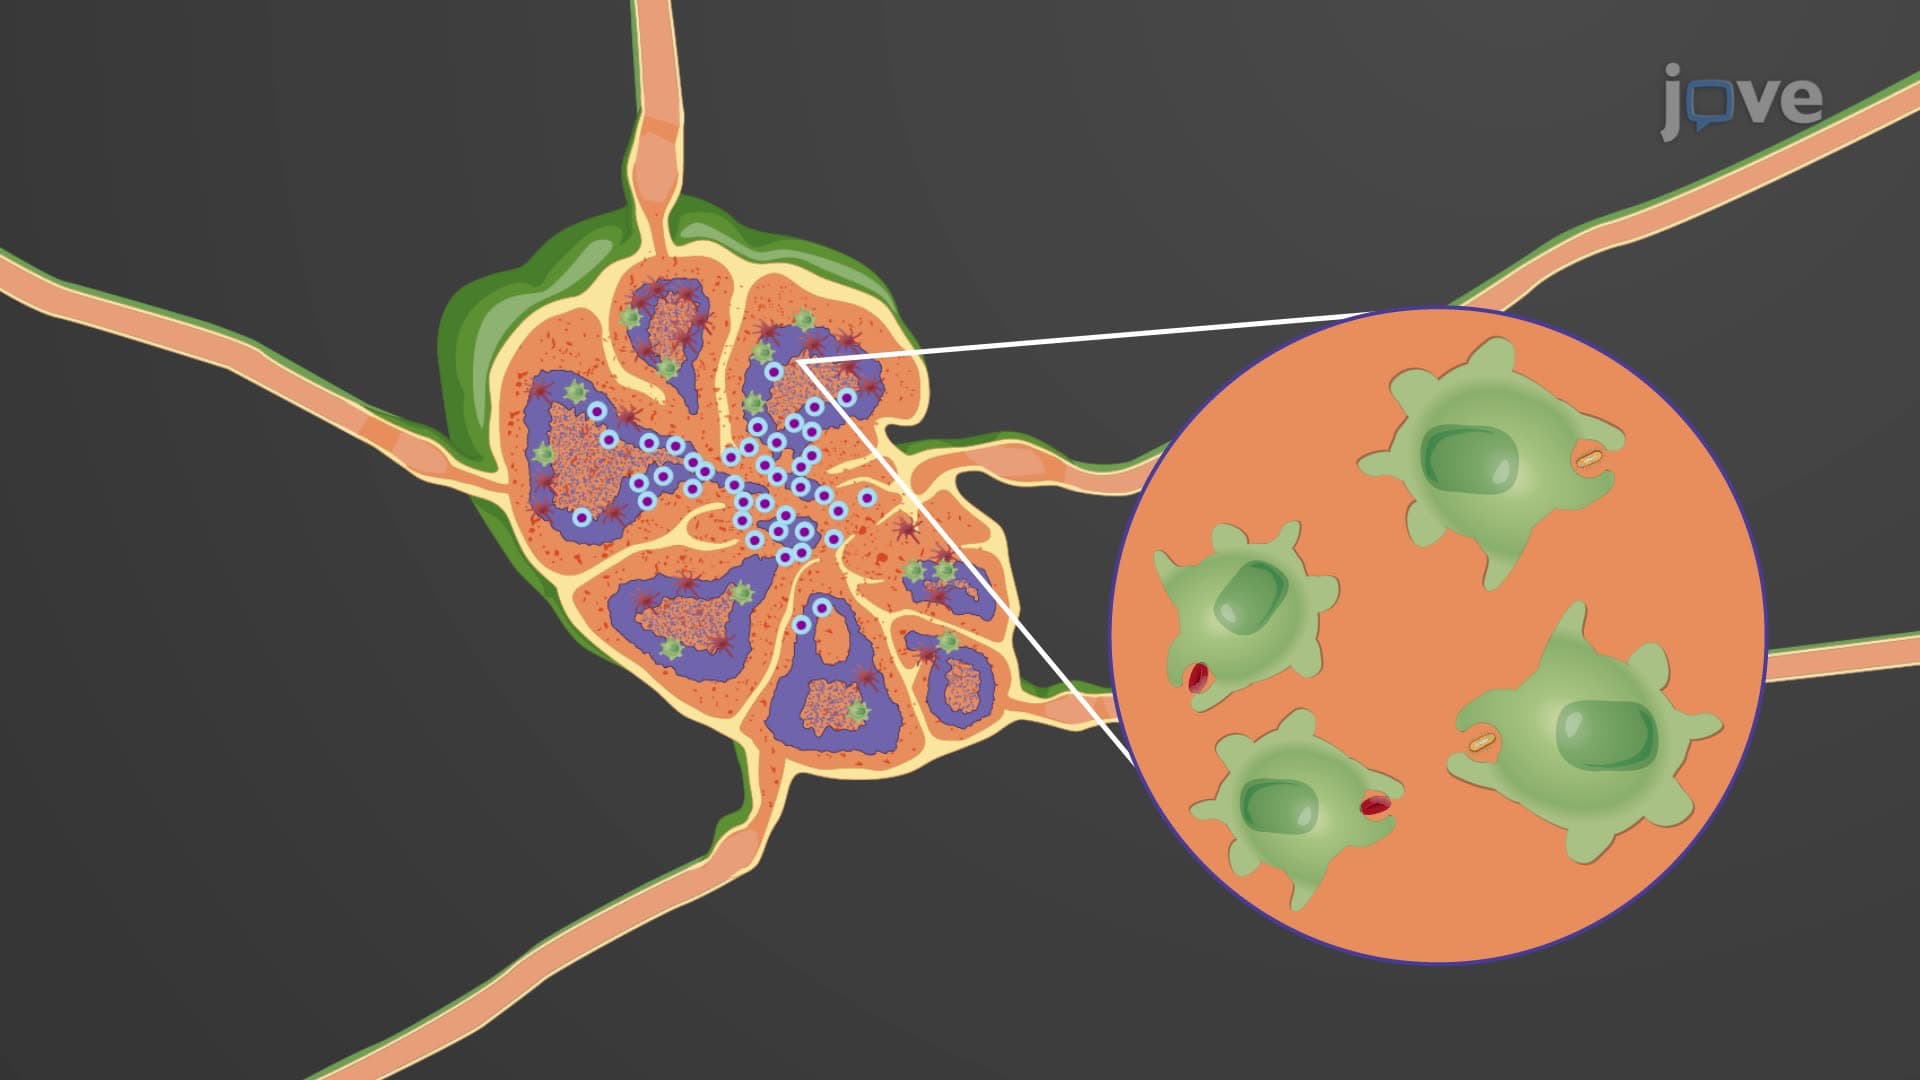
From a histological perspective, lymph nodes can be split into two main areas: the superficial cortex and the deep medulla. The outer cortex is populated by dendritic cells, macrophages, and B lymphocytes, which are densely packed into follicles. When these B-lymphocytes are presented...
 01:15
Development of the Lymphatic System
The first lymph sacs to form are the paired jugular lymph sacs located at the junction of the internal jugular and subclavian veins. From these sacs, lymphatic capillary plexuses extend to the thorax, upper limbs, neck, and head, eventually forming lymphatic vessels. Each jugular lymph sac maintains a...
 01:15
Secondary Lymphoid Organs
The spleen is a vital organ in the lymphatic system, nestled in the upper left side of the abdomen. It is composed of two primary regions: the red pulp and the white pulp, each having distinct functions. The red pulp performs a significant role in blood filtration. It efficiently purges the blood of old or damaged red blood cells and...
 01:16
Lymphatic Vessels and Lymph Transport
This one-way system allows fluids, solutes, and even pathogens to enter but prevents their return to the intercellular...
 01:16
Primary Lymphoid Organs
The red bone marrow is a soft, spongy tissue nestled in the interior of long bones such as the humerus and femur. It is the site...
 01:18
Lymphoid Cells and Tissues
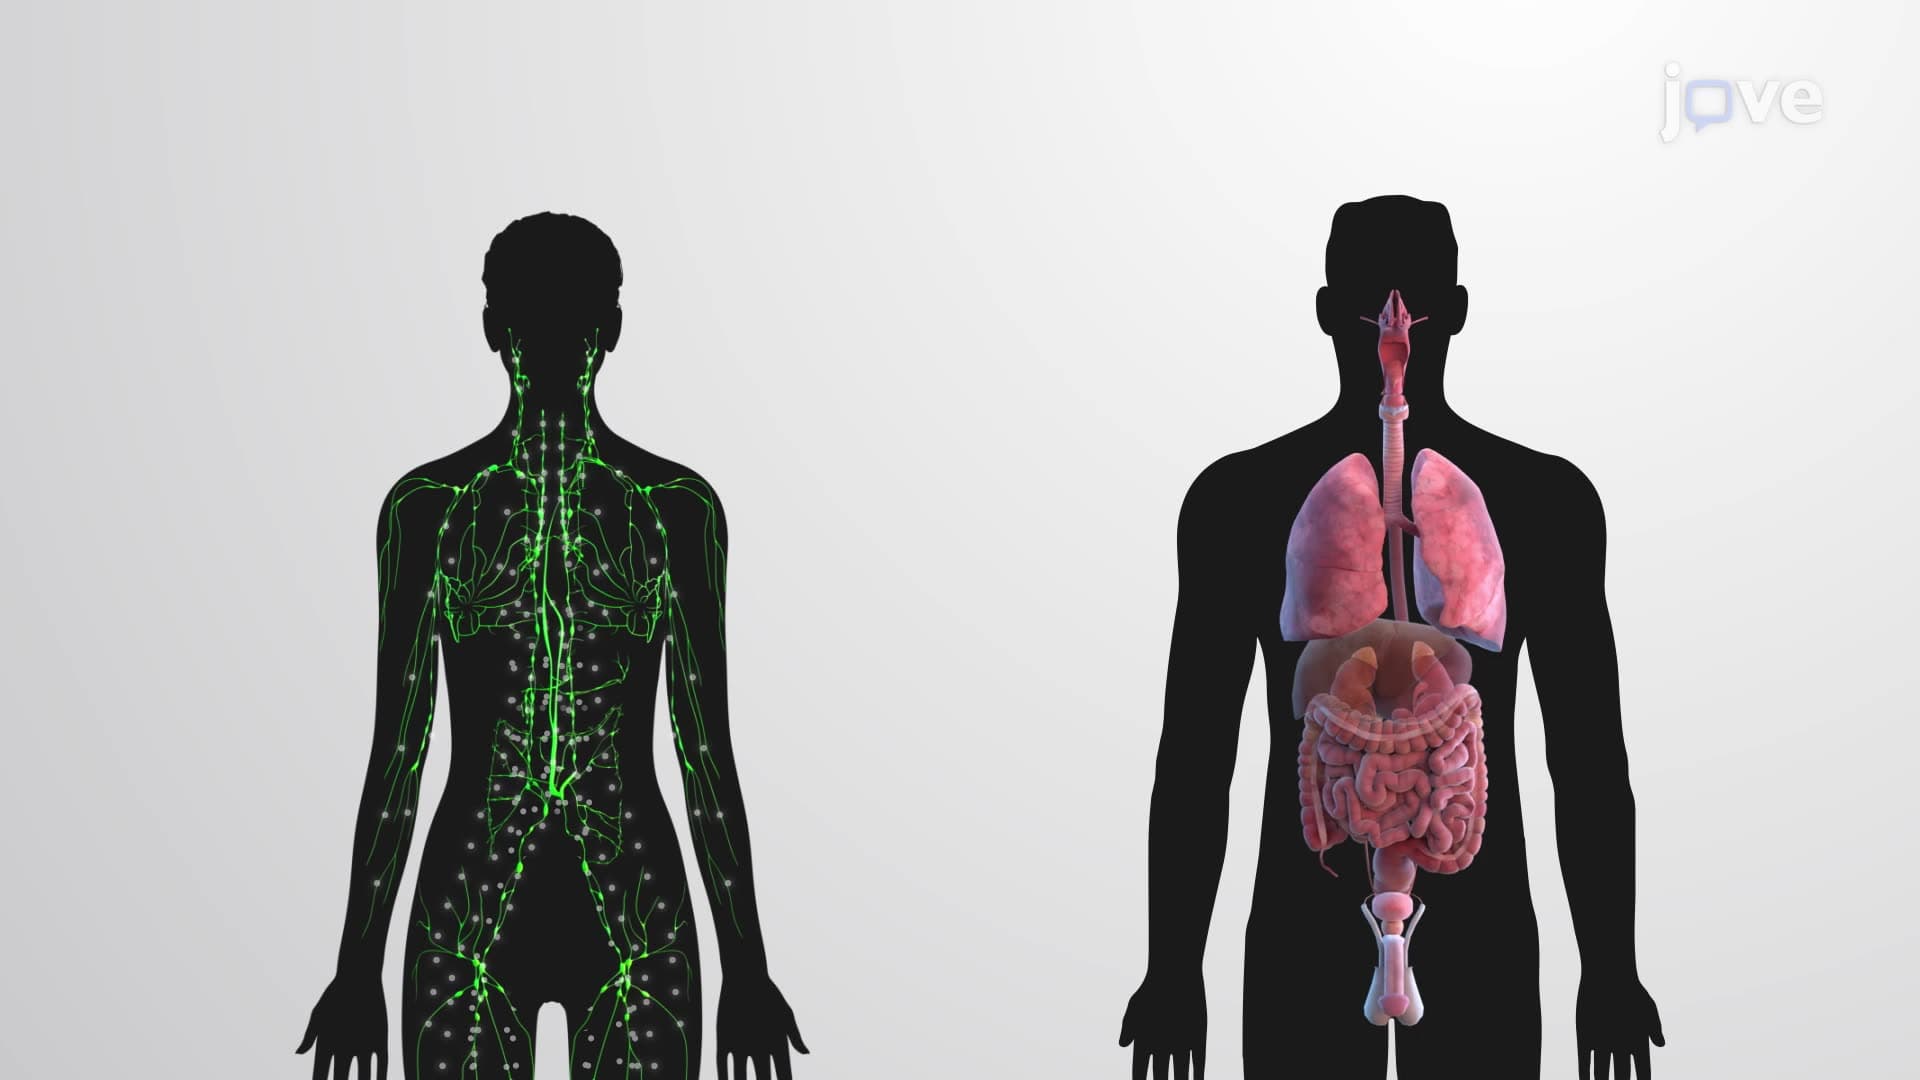
Lymphoid cells consist of various types of immune system cells. These include B and T lymphocytes, which are responsible for producing antibodies and killing infected cells, respectively. Dendritic cells act as messengers between the innate and adaptive...