Related Experiment Video
Updated: Mar 22, 2026
Repeated Measurement of Respiratory Muscle Activity and Ventilation in Mouse Models of Neuromuscular Disease
Published on: April 17, 2017
Cortical drive to breathe in amyotrophic lateral sclerosis: a dyspnoea-worsening defence?
Marjolaine Georges1, Elise Morawiec2, Mathieu Raux3
1UMRS1158 Neurophysiologie Respiratoire Expérimentale et Clinique, Sorbonne Universités, UPMC Université Paris 06, INSERM, Paris, France Service de Pneumologie et Réanimation Médicale (Département R3S), AP-HP, Groupe Hospitalier Pitié-Salpêtrière Charles Foix, Paris, France Service de Pneumologie et Réanimation Respiratoire, Centre Hospitalier Universitaire de Dijon, Dijon, France.

Abstract:
Amyotrophic lateral sclerosis (ALS) is a neurodegenerative disease causing diaphragm weakness that can be partially compensated by inspiratory neck muscle recruitment. This disappears during sleep, which is compatible with a cortical contribution to the drive to breathe. We hypothesised that ALS patients with respiratory failure exhibit respiratory-related cortical activity, relieved by noninvasive ventilation (NIV) and related to dyspnoea.We studied 14 ALS patients with respiratory failure. Electroencephalographic recordings (EEGs) and electromyographic recordings of inspiratory neck muscles were performed during spontaneous breathing and NIV. Dyspnoea was evaluated using the Multidimensional Dyspnea Profile.Eight patients exhibited slow EEG negativities preceding inspiration (pre-inspiratory potentials) during spontaneous breathing. Pre-inspiratory potentials were attenuated during NIV (p=0.04). Patients without pre-inspiratory potentials presented more advanced forms of ALS and more severe respiratory impairment, but less severe dyspnoea. Patients with pre-inspiratory potentials had stronger inspiratory neck muscle activation and more severe dyspnoea during spontaneous breathing.ALS-related diaphragm weakness can engage cortical resources to augment the neural drive to breathe. This might reflect a compensatory mechanism, with the intensity of dyspnoea a negative consequence. Disease progression and the corresponding neural loss could abolish this phenomenon. A putative cognitive cost should be investigated.
More Related Videos
Related Concept Videos
 01:22
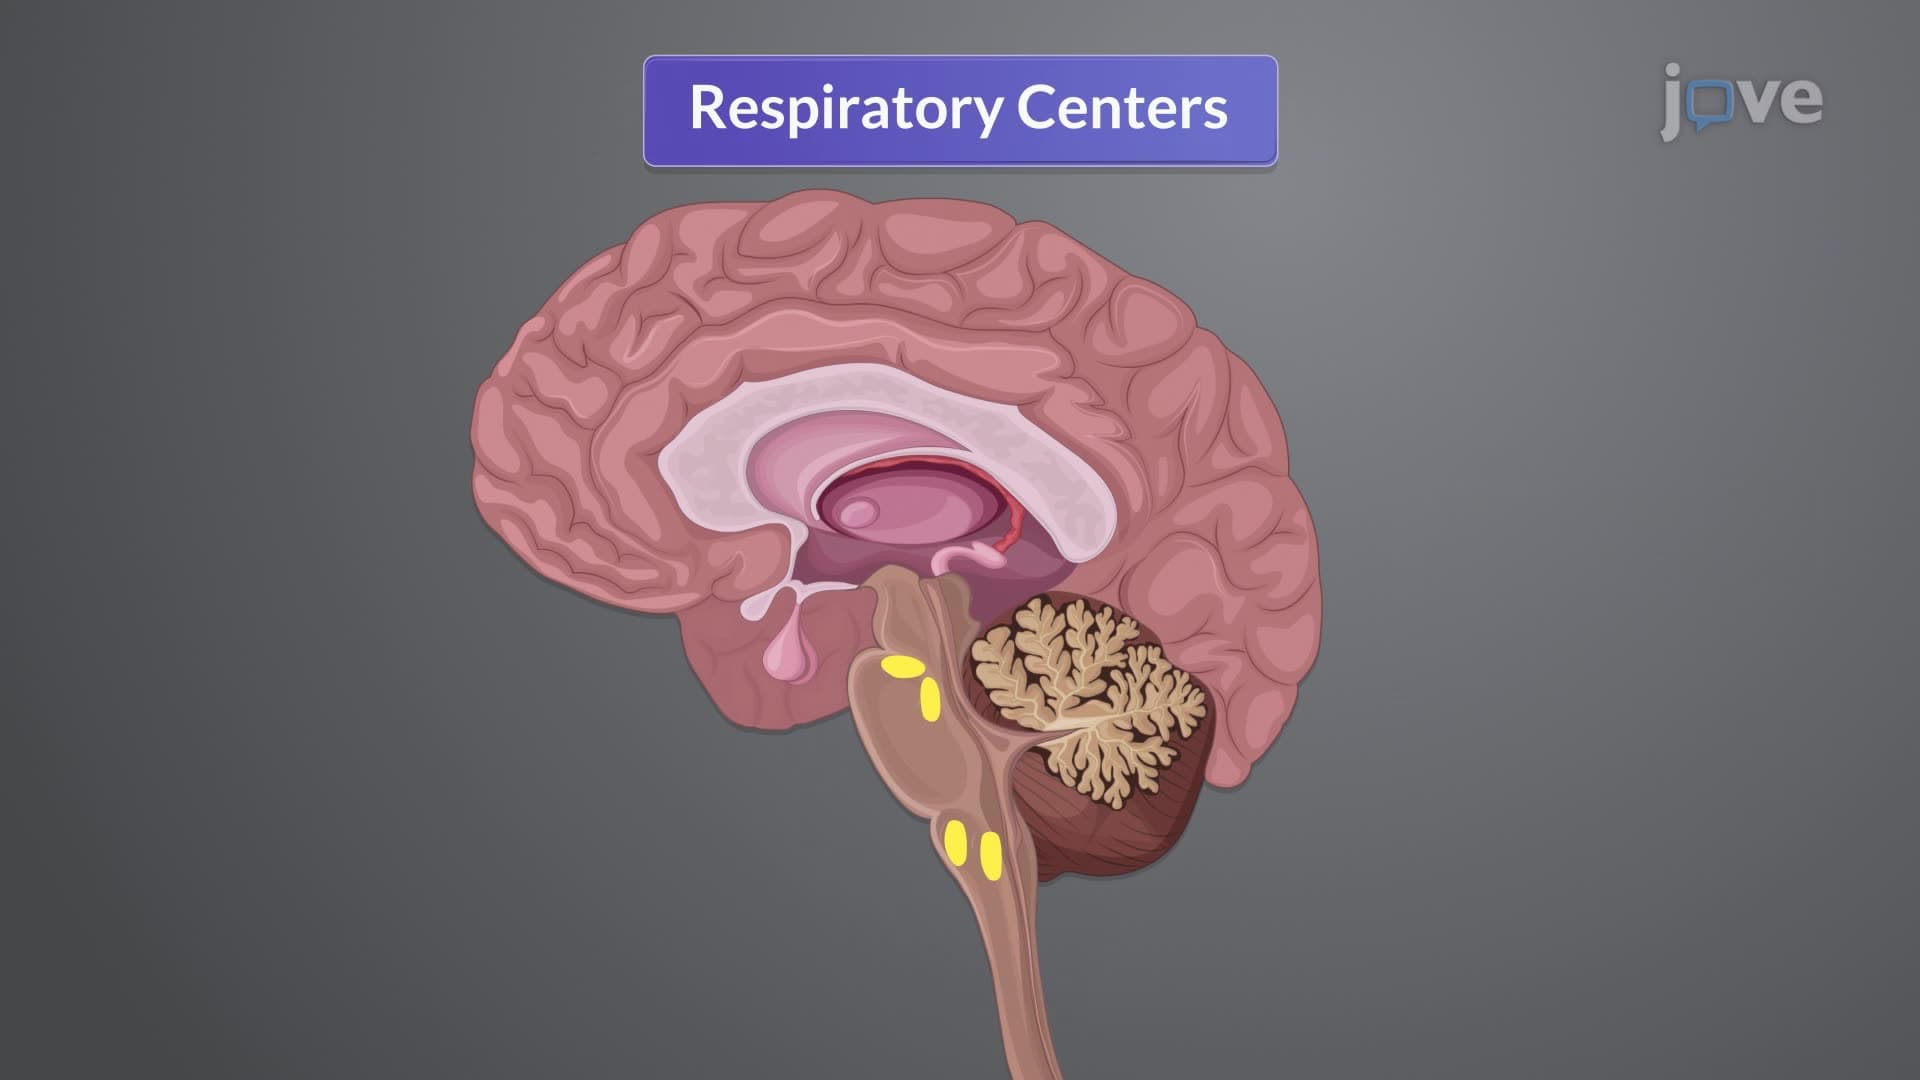
Physiology of Respiration II: Neurogenic Control of Respiration
Central Control
The brainstem is the primary site of central control, hosting respiratory centers:
 01:26
Cross-bridge Cycle
 01:18
Neural Control of Respiration
Respiratory Centers in the Brainstem
Two primary areas comprise the respiratory center: the medullary respiratory center in the medulla oblongata and the pontine respiratory group in the pons. The...
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:21
Mechanism of Breathing III: The Accessory Muscles
The respiratory system is a complex network that relies on primary respiratory muscles like the diaphragm, but also involves accessory muscles to enhance lung expansion and airflow during both inhalation and exhalation.
Enhancing Inhalation with Accessory Muscles:
Accessory muscles such as the sternocleidomastoid, scalene, intercostal, and abdominal muscles are crucial when additional respiratory effort is required, such as during deep...