Related Experiment Video
Updated: Mar 22, 2026

Author Spotlight: Effect of Left Atrial Ligation on Avian Embryonic Hearts and HLHS Implications
Published on: June 16, 2023
Persistent Left Superior Vena Cava Connected to the Coronary Sinus in the Fetus: Effects on Cardiac Structure and
Xiaowei Liu1, Yihua He2, Zhiyun Tian3
1Fetal Heart Disease Maternal Fetal Medicine Research Laboratories, Department of Ultrasound, Beijing Anzhen Hospital, Capital Medical University, No. 2 Anzhen Road, Chaoyang District, 100029, Beijing, China.

Insights
Persistent left superior vena cava (PLSVC) in fetuses is linked to altered cardiac dimensions, particularly in the second trimester. These cardiac differences associated with PLSVC tend to decrease as the pregnancy progresses.
Area of Science:
- Fetal cardiology
- Congenital heart anomalies
- Prenatal imaging
Background:
- Persistent left superior vena cava (PLSVC) is a common fetal anomaly.
- Ventricular size discrepancies can be associated with PLSVC, impacting cardiac development.
- Understanding these impacts is crucial for prenatal diagnosis and management.
Purpose of the Study:
- To investigate differences in fetal cardiac structure and hemodynamics between fetuses with isolated PLSVC connected to the coronary sinus (CS) and normal controls.
- To assess how these differences change with gestational age.
Main Methods:
- Retrospective analysis of fetal echocardiograms in the second and third trimesters.
- Comparison of cardiac structure parameters (e.g., RV/LV, PA/AO ratios, vessel diameters) and hemodynamics between isolated PLSVC and control groups.
- Gestational age-matched cohort design.
Main Results:
- In the second trimester, fetuses with isolated PLSVC showed significantly larger RV/LV and PA/AO ratios and smaller AO and aortic isthmus diameters compared to controls.
- In the third trimester, only the PA/AO ratio remained significantly larger, and aortic isthmus diameter smaller in the PLSVC group.
- Cardiac structural differences associated with isolated PLSVC diminished with advancing gestational age.
Conclusions:
- Isolated PLSVC connected to the CS is associated with measurable differences in fetal cardiac structure.
- These observed differences tend to decrease with increasing gestational age.
- A dilated CS may influence the development of fetal left heart structures.
Abstract:
Ventricular size discrepancy may be due to a persistent left superior vena cava (PLSVC) in utero. We sought to investigate for differences in cardiac structure measures and hemodynamics between fetuses with isolated PLSVC connected to the coronary sinus (CS) and normal. Fetuses diagnosed with isolated PLSVC in the second and third trimester were enrolled. We defined two groups: group 1, twenty-five fetuses in the second trimester (22-27 W + 6d); group 2, twenty-two fetuses in the third trimester (28-39 W + 6d). Fifty-three fetuses without intra-cardiac or extra-cardiac anomalies and gestation age-matched were divided into normal control groups: group 3, 28 fetuses in the second trimester; group 4, 25 fetuses in the third trimester. Parameters of cardiac structure and hemodynamics were measured, including: left- and right-side heart size, the diameter of foramen ovale, aorta (AO), aortic isthmus and pulmonary artery (PA), and ratios of cardiac structure RV/LV, RA/LA and PA/AO were calculated. Hemodynamic parameters measured included: flow velocity across mitral valve, tricuspid valve and foramen ovale. In the second trimester, the ratio of RV/LV and PA/AO of the PLSVC fetuses was significantly larger than normal, while the AO diameter, aortic isthmus diameter were smaller than normal (P < 0.05). However, in the third trimester, only the ratio of PA/AO of the PLSVC fetuses was significantly larger, and the aortic isthmus diameter was still smaller than normal (P < 0.05). Isolated PLSVC connecting to the CS is associated with differences in cardiac structure size from normal. These differences appear to diminish with gestational age. A dilated CS may have an influence on development of fetal left heart structures.

Related Concept Videos
 01:11
Overview of Systemic Veins
The coronary sinus, the heart's principal vein, resides in the coronary sulcus on the heart's posterior aspect. This broad venous channel receives nearly all venous blood from the myocardium, the heart muscle. It is fed by three primary veins: the great cardiac vein, the...
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...
 01:21
Coronary Circulation
Coronary circulation begins at the base of the aorta, where two main arteries arise—the left and right coronary arteries. These arteries encircle the heart in the coronary sulcus and supply the...
 01:27
Development of the Heart
As the embryo undergoes lateral folding, these paired tubes approach each other, merging into a single primitive heart...
 01:16
Chambers of the Heart
Deoxygenated blood from the body is received in the right...
 01:07
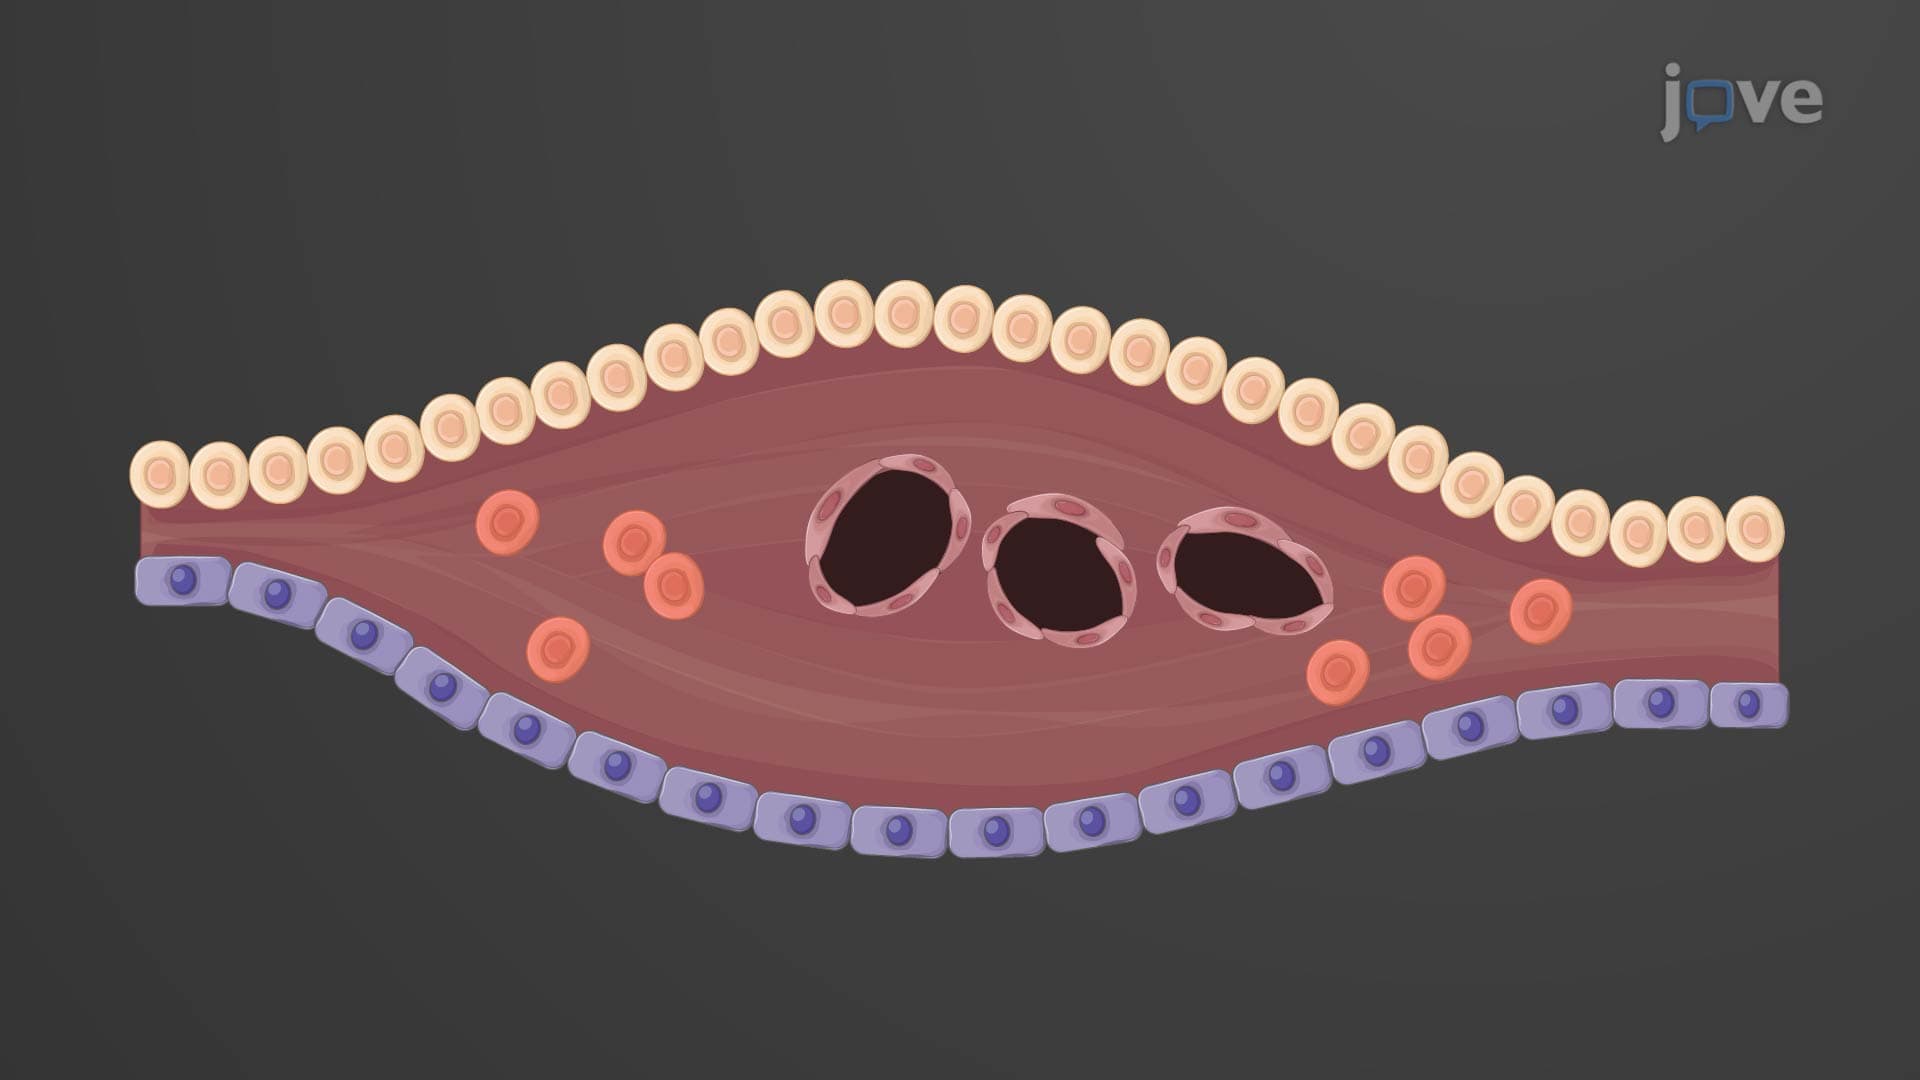
Development of Blood Vessels
The initial formation of this system is facilitated by the small amount of yolk present in the ovum and yolk sac. Blood vessels originate from...