Related Experiment Video
Updated: Mar 22, 2026


Sarcomere Shortening of Pluripotent Stem Cell-Derived Cardiomyocytes using Fluorescent-Tagged Sarcomere Proteins.
Published on: March 3, 2021
Contractile Dysfunction in Sarcomeric Hypertrophic Cardiomyopathy
David H MacIver1, Andrew L Clark2
1Department of Cardiology, Taunton & Somerset Hospital, Musgrove Park, Taunton, UK; Biological Physics Group, School of Physics & Astronomy, University of Manchester, Manchester, UK; Medical Education, University of Bristol, Senate House, Tyndall Avenue, Bristol BS8 1TH, UK.

Insights
Reduced contractile stress, not just hypertrophy, drives hypertrophic cardiomyopathy. Hemodynamic load influences the specific disease pattern, impacting cardiac function and phenotype.
Area of Science:
- Cardiology
- Pathophysiology
- Biomedical Engineering
Background:
- The mechanisms behind hypertrophic cardiomyopathy (HCM) phenotypes remain debated.
- Cardiac hypertrophy in conditions like hypertension is typically a compensatory response to normalize wall stress.
Purpose of the Study:
- To propose that reduced myocardial contractile stress, rather than solely hypertrophy, is a key abnormality in HCM.
- To investigate how hemodynamic load influences the diverse clinical phenotypes observed in HCM.
Main Methods:
- The study proposes a theoretical framework based on existing pathophysiological understanding.
- Analysis of the relationship between contractile stress, cardiomyocyte disarray, and cardiac remodeling.
- Examination of how different hemodynamic loads might lead to specific HCM patterns.
Main Results:
- Reduced contractile stress, caused by factors like cardiomyocyte disarray, is suggested as a primary driver of HCM progression.
- This reduced stress leads to worsening hypertrophy and disarray, despite preserved or enhanced ejection fraction.
- Hemodynamic load is proposed to dictate the specific phenotype: concentric hypertrophy in hypertension, asymmetric in athletes, and apical in inactive individuals.
Conclusions:
- HCM pathophysiology may involve a primary deficit in myocardial contractile stress.
- The interplay between contractile stress, cardiac remodeling, and hemodynamic load determines HCM phenotype.
- Left ventricular outflow tract obstruction and mitral regurgitation could arise from regional strain disparities and mitral annular rotation.
Abstract:
The pathophysiological mechanisms underlying the clinical phenotype of sarcomeric hypertrophic cardiomyopathy are controversial. The development of cardiac hypertrophy in hypertension and aortic stenosis is usually described as a compensatory mechanism that normalizes wall stress. We suggest that an important abnormality in hypertrophic cardiomyopathy is reduced contractile stress (the force per unit area) generated by myocardial tissue secondary to abnormalities such as cardiomyocyte disarray. In turn, a progressive deterioration in contractile stress provokes worsening hypertrophy and disarray. A maintained or even exaggerated ejection fraction is explained by the increased end-diastolic wall thickness producing augmented thickening. We propose that the nature of the hemodynamic load in an individual with hypertrophic cardiomyopathy could determine its phenotype. Hypertensive patients with hypertrophic cardiomyopathy are more likely to develop exaggerated concentric hypertrophy; athletic individuals an asymmetric pattern; and inactive individuals a more apical hypertrophy. The development of a left ventricular outflow tract gradient and mitral regurgitation may be explained by differential regional strain resulting in mitral annular rotation.
More Related Videos


Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:25
Cardiomyopathy I: Introduction and Classification
 01:08
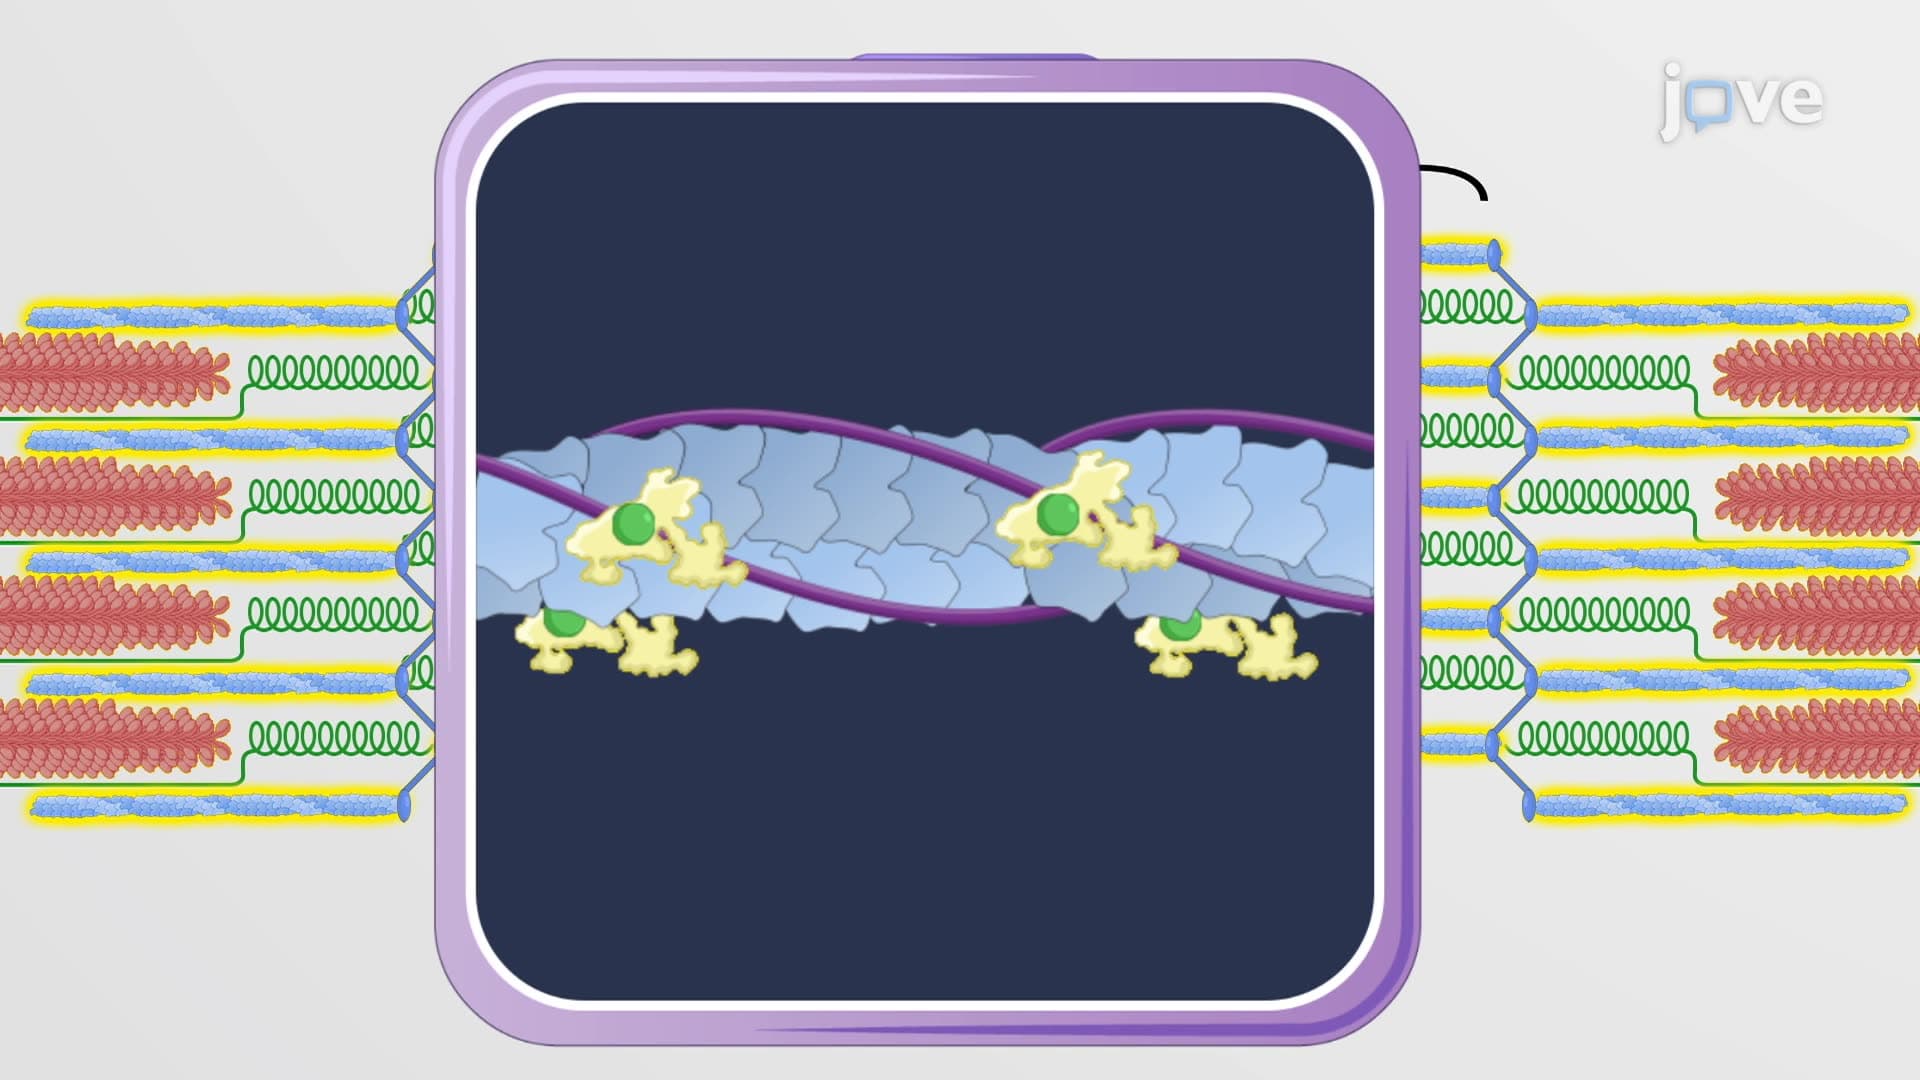
The Sarcomere
Each...
 01:13
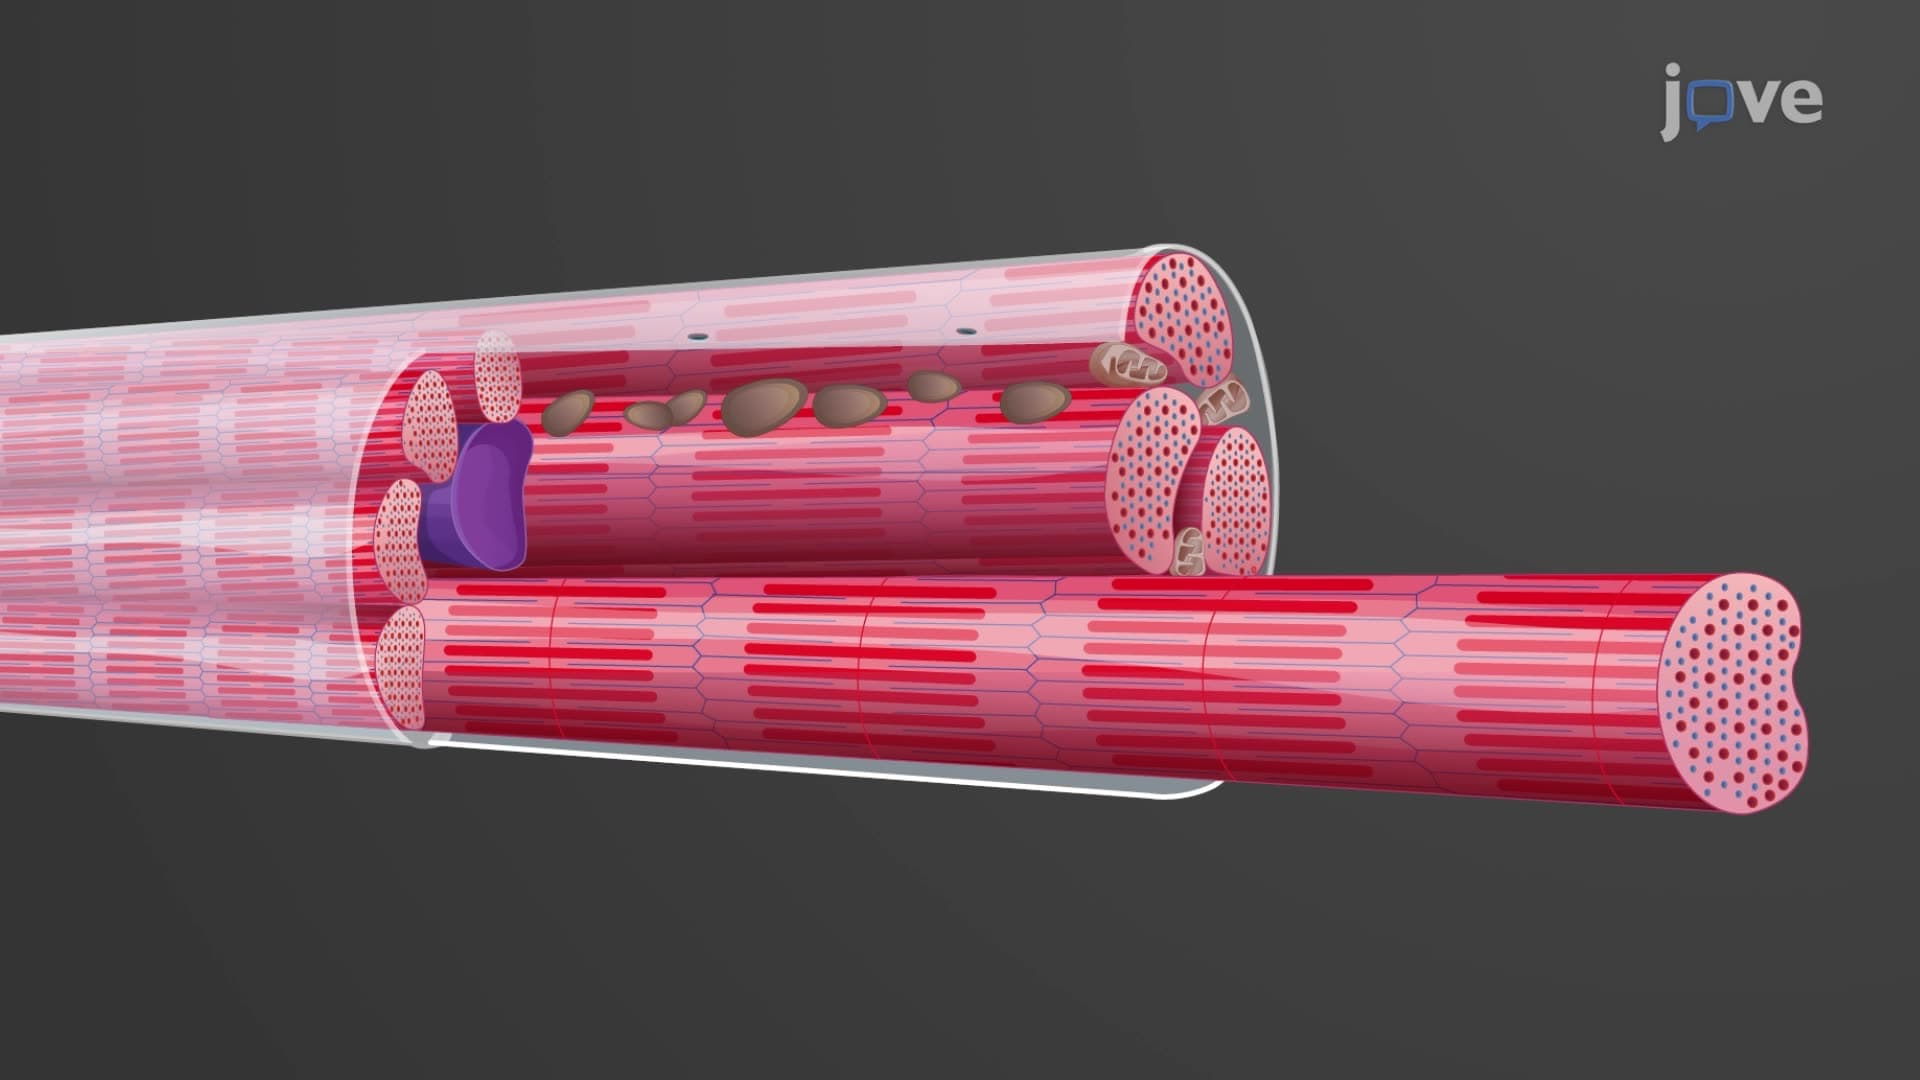
Structure of Cardiac Muscles
Compared to skeletal muscles, cardiac muscle cells are small and mostly have a single nucleus. Additionally, they are usually...