Related Experiment Video
Updated: Mar 22, 2026
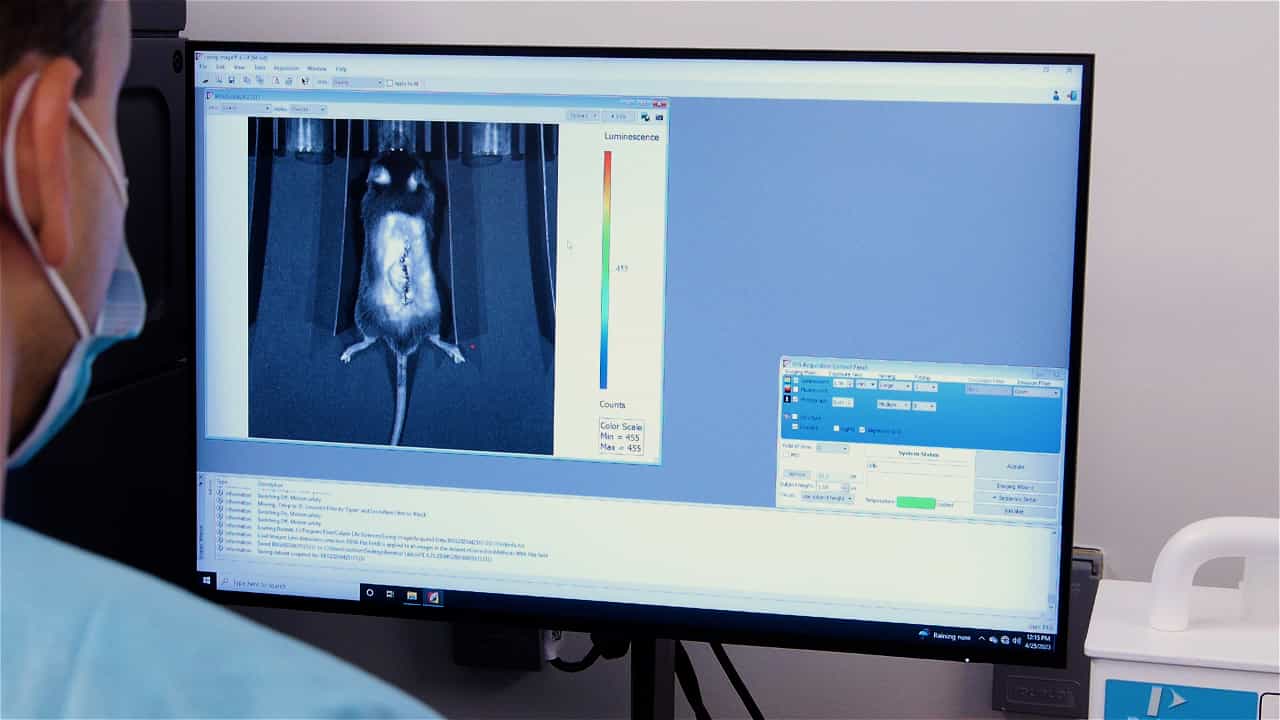

In Vivo Mouse Model of Spinal Implant Infection
Published on: June 23, 2020
A comparison of different antibiotic regimens for the treatment of infective endocarditis
Arturo J Martí-Carvajal1, Mark Dayer, Lucieni O Conterno
1Iberoamerican Cochrane Network, Valencia, Venezuela.

Background:
Infective endocarditis is a microbial infection of the endocardial surface of the heart. Antibiotics are the cornerstone of treatment, but their use is not standardised, due to the differences in presentation, populations affected and the wide variety of micro-organisms that can be responsible.
Objectives:
To assess the existing evidence about the clinical benefits and harms of different antibiotics regimens used to treat people with infective endocarditis.
Search Methods:
We searched the Cochrane Central Register of Controlled Trials (CENTRAL), MEDLINE, EMBASE Classic and EMBASE, LILACS, CINAHL and the Conference Proceedings Citation Index on 30 April 2015. We also searched three trials registers and handsearched the reference lists of included papers. We applied no language restrictions.
Selection Criteria:
We included randomised controlled trials assessing the effects of antibiotic regimens for treating possible infective endocarditis diagnosed according to modified Duke's criteria. We considered all-cause mortality, cure rates and adverse events as the primary outcomes. We excluded people with possible infective endocarditis and pregnant women.
Data Collection And Analysis:
Three review authors independently performed study selection, 'Risk of bias' assessment and data extraction in duplicate. We constructed 'Summary of findings' tables and used GRADE methodology to assess the quality of studies. We described the included studies narratively.
Main Results:
Four small randomised controlled trials involving 728 allocated/224 analysed participants met our inclusion criteria. These trials had a high risk of bias. Drug companies sponsored two of the trials. We were unable to pool the data due to the heterogeneity in outcome definitions and the different antibiotics used.The included trials compared the following antibiotic schedules. The first trial compared quinolone (levofloxacin) plus standard treatment (anti-staphylococcal penicillin (cloxacillin or dicloxacillin), aminoglycoside (tobramycin or netilmicin) and rifampicin) versus standard treatment alone reporting uncertain effects on all-cause mortality (8/31 (26%) with levofloxacin plus standard treatment versus 9/39 (23%) with standard treatment alone; RR 1.12, 95% CI 0.49 to 2.56, very low quality evidence). The second trial compared daptomycin versus low-dose gentamicin plus an anti-staphylococcal penicillin (nafcillin, oxacillin or flucloxacillin) or vancomycin. This showed uncertain effects in terms of cure rates (9/28 (32.1%) with daptomycin versus 9/25 (36%) with low-dose gentamicin plus anti-staphylococcal penicillin or vancomycin, RR 0.89 95% CI 0.42 to 1.89; very low quality evidence). The third trial compared cloxacillin plus gentamicin with a glycopeptide (vancomycin or teicoplanin) plus gentamicin. In participants receiving gentamycin plus glycopeptide only 13/23 (56%) were cured versus 11/11 (100%) receiving cloxacillin plus gentamicin (RR 0.59, 95% CI 0.40 to 0.85; very low quality evidence). The fourth trial compared ceftriaxone plus gentamicin versus ceftriaxone alone and found no conclusive differences in terms of cure (15/34 (44%) with ceftriaxone plus gentamicin versus 21/33 (64%) with ceftriaxone alone, RR 0.69, 95% CI 0.44 to 1.10; very low quality evidence).The trials reported adverse events, need for cardiac surgical interventions, uncontrolled infection and relapse of endocarditis and found no conclusive differences between comparison groups (very low quality evidence). No trials assessed septic emboli or quality of life.
Authors' Conclusions:
Limited and very low quality evidence suggested that there were no conclusive differences between antibiotic regimens in terms of cure rates or other relevant clinical outcomes. However, because of the very low quality evidence, this needs confirmation. The conclusion of this Cochrane review was based on randomised controlled trials with high risk of bias. Accordingly, current evidence does not support or reject any regimen of antibiotic therapy for treatment of infective endocarditis.
Insights
Current evidence on antibiotic regimens for infective endocarditis is limited and of very low quality. No definitive conclusions can be drawn regarding the superiority of any specific antibiotic treatment for this heart infection.
Area of Science:
- Cardiology
- Infectious Diseases
- Pharmacology
Background:
- Infective endocarditis is a serious microbial infection of the heart's endocardial surface.
- Antibiotic therapy is the primary treatment, but standardized regimens are lacking due to diverse presentations and causative organisms.
Purpose of the Study:
- To evaluate the clinical benefits and harms of various antibiotic regimens for treating infective endocarditis.
Main Methods:
- A systematic review of randomized controlled trials (RCTs) was conducted, searching multiple databases up to April 2015.
- Four small RCTs with a high risk of bias were included, comparing different antibiotic schedules for infective endocarditis.
- Data were analyzed narratively due to heterogeneity; primary outcomes included mortality, cure rates, and adverse events.
Main Results:
- Limited evidence from four small, high-risk-of-bias RCTs showed no conclusive differences between compared antibiotic regimens regarding cure rates or mortality.
- Specific comparisons included quinolones, daptomycin, cloxacillin, and ceftriaxone against various standard treatments, all yielding very low-quality evidence.
- No significant differences were found in adverse events, need for surgery, or infection relapse across treatment groups.
Conclusions:
- The current evidence base for antibiotic treatment of infective endocarditis is very limited and of low quality.
- Existing data do not support or reject any specific antibiotic regimen for treating infective endocarditis.
- Further high-quality research is needed to confirm findings and guide treatment decisions.
Related Concept Videos
 01:18
Endocarditis III: Medical Management
 01:25
Endocarditis I: Introduction
 01:29
Endocarditis IV: Nursing Management
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:22
Pharmaceutical Alternatives: Stability-Related Therapeutic Nonequivalence
 01:14
Myocarditis III: Medical Management