Related Experiment Video
Updated: Mar 22, 2026
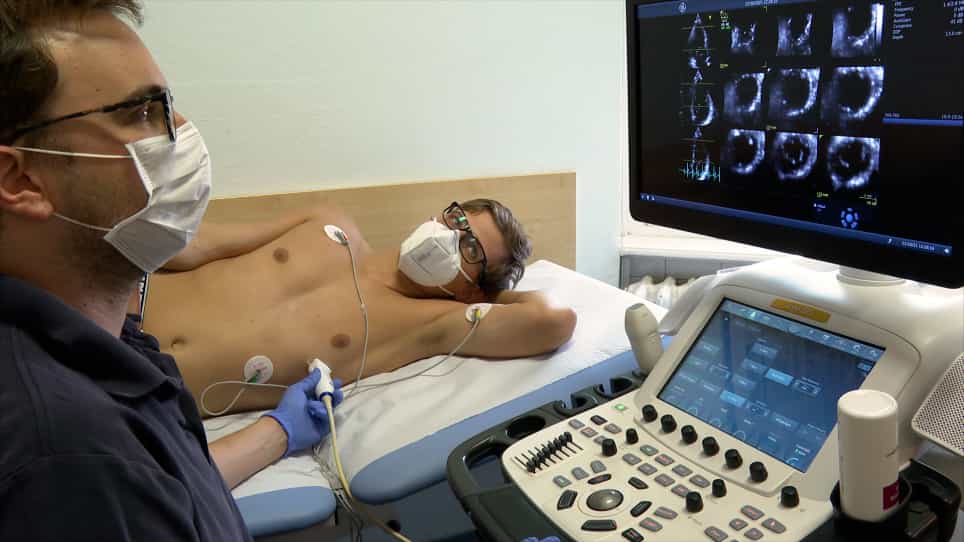
Evaluation of Left Ventricular Structure and Function using 3D Echocardiography
Published on: October 28, 2020
Prognostic value of diastolic wall strain in patients with chronic heart failure with reduced ejection fraction
Yuko Soyama1, Toshiaki Mano2, Akiko Goda1
1Cardiovascular Division, Department of Internal Medicine, Hyogo College of Medicine, 1-1, Mukogawa-cho, Nishinomiya, Hyogo, 663-8501, Japan.

Insights
Diastolic wall strain (DWS), a marker of left ventricular stiffness, predicts outcomes in heart failure with reduced ejection fraction (HFrEF) patients on beta blockers. Lower DWS indicates a worse prognosis, independent of other factors.
Area of Science:
- Cardiology
- Cardiovascular Physiology
Background:
- Left ventricular (LV) diastolic dysfunction is key in heart failure with reduced ejection fraction (HFrEF).
- The prognostic value of LV stiffness, a component of diastolic function, in HFrEF patients receiving adequate beta-blocker therapy is not fully understood.
Purpose of the Study:
- To assess if diastolic wall strain (DWS), a noninvasive marker of LV stiffness, can predict prognosis in HFrEF patients under chronic beta-blockade.
- To determine if DWS is an independent prognostic factor in this patient population.
Main Methods:
- Seventy-five HFrEF patients receiving chronic beta-blocker therapy were enrolled.
- Echocardiographic parameters, plasma brain natriuretic peptide (BNP), and pulmonary artery wedge pressure (PAWP) were measured.
- DWS was calculated using M-mode echocardiography: DWS = [(LV posterior wall thickness at end-systole - LVPWT at end-diastole)/LVPWT] at end-systole.
Main Results:
- DWS did not correlate with other echocardiographic parameters or PAWP.
- Patients with low DWS had a significantly higher incidence of the primary outcome (HF hospitalization or cardiovascular death) over 7 years (p=0.04).
- Under sufficient beta-blocker therapy, DWS emerged as an independent predictor of event-free time in multivariate analysis, unlike other echocardiographic parameters.
Conclusions:
- Impaired LV stiffness, assessed by DWS, is linked to worse outcomes in HFrEF patients on chronic beta-blockade.
- DWS may serve as an independent prognostic factor in this specific patient group.
Abstract:
Left ventricular (LV) diastolic dysfunction plays a crucial role in heart failure with reduced ejection fraction (HFrEF). LV stiffness is a main component of diastolic function, but its role and prognostic value in HFrEF patients remains unclear. This study aimed to determine whether diastolic wall strain (DWS) as a noninvasive and simple marker of LV stiffness can predict the prognosis of HFrEF patients who were administrated chronic beta blockade enough. We enrolled 75 HFrEF patients who were administrated chronic beta blockade. We evaluated the echocardiographic parameters and plasma brain natriuretic peptide (BNP) before the induction of beta blockade and also obtained pulmonary artery wedge pressure (PAWP) from the right heart catheterization. DWS was obtained from standard M-mode echocardiography as follows: DWS = [(LV posterior wall thickness (LVPWT) at end-systole - LVPWT at end-diastole)/LVPWT] at end-systole. DWS did not correlate with other echocardiographic parameters and PAWP. We defined primary outcome as HF hospitalization or cardiovascular death and followed for 7 years. The incidence rate was higher in low DWS than high DWS patients (p = 0.04). Other echocardiographic parameters could not be significant predictors of HFrEF outcome under the condition of enough beta blocker therapy. In multivariate analysis, DWS was the independent contributor to the event-free time. Impaired LV stiffness evaluated with DWS was associated with worse outcome and DWS might be an independent prognostic factor in HFrEF patients with chronic beta blockade.
More Related Videos
 12:12
Echocardiographic Approaches and Protocols for Comprehensive Phenotypic Characterization of Valvular Heart Disease in Mice
Published on: February 14, 2017
 11:50
High-frequency High-resolution Echocardiography: First Evidence on Non-invasive Repeated Measure of Myocardial Strain, Contractility, and Mitral Regurgitation in the Ischemia-reperfused Murine Heart
Published on: July 9, 2010
Related Concept Videos
 01:29
Heart Failure II: Pathophysiology
 01:30
Heart Failure IV: Classification and Diagnostic Evaluation