Related Experiment Video
Updated: Mar 22, 2026


Intravascular Delivery of Biologics to the Rat Kidney
Published on: September 1, 2016
Infusion Rate Dependent Pharmacokinetics of Bendamustine with Altered Formation of γ-hydroxybendamustine (M3)
N R Srinivas1, W Richter2, V C Devaraj3
1Suramus Bio, Drug Development, I Phase, J.P. Nagar, Bangalore, India.

Abstract:
Bendamustine is an alkylating agent administered as 1 h intravenous infusion in the clinic for the treatment of malignant haematological cancers. The aim of the study was to evaluate the pharmacokinetics of bendamustine and its key cytochrome P 450 (CYP) 1A2 mediated γ-hydroxybendamustine (M3) metabolite after 30- and 60-min intravenous infusion of bendamustine in rats. 2 groups were assigned to receive bendamustine either as 30- or 60-min infusion and doses were normalized to 15 mg/kg for the sake of statistical evaluation. Serial pharmacokinetic samples were collected and were analysed for the circulatory levels of bendamustine and its M3 metabolite. Standard pharmacokinetic parameters were generated for bendamustine and its M3 metabolite. Regardless of the intravenous regimens, Cmax coincided with end of infusion for both bendamustine and its M3 metabolite. Immediately after stoppage of infusion, a rapid decline in the plasma levels occurred for both bendamustine and M3 metabolite. The Cmax and AUC0-∞ parameters for bendamustine after 60-min infusion were 1.90 and 1.34-fold higher; while CL was lower by 1.32-fold as compared to the 30-min infusion. In contrast, the Cmax and AUC0-∞ after 30-min infusion for the M3 metabolite was 2.15- and 2.78-fold greater; while CL was 2.32-fold lower when compared to the 60-min infusion. However, T1/2 and Vz values were similar between the 2 intravenous treatments for bendamustine or the M3 metabolite. The data unequivocally confirmed the existence of differential pharmacokinetics of bendamustine and its M3 metabolite as the function of the duration of intravenous infusion.


Related Concept Videos
 01:15
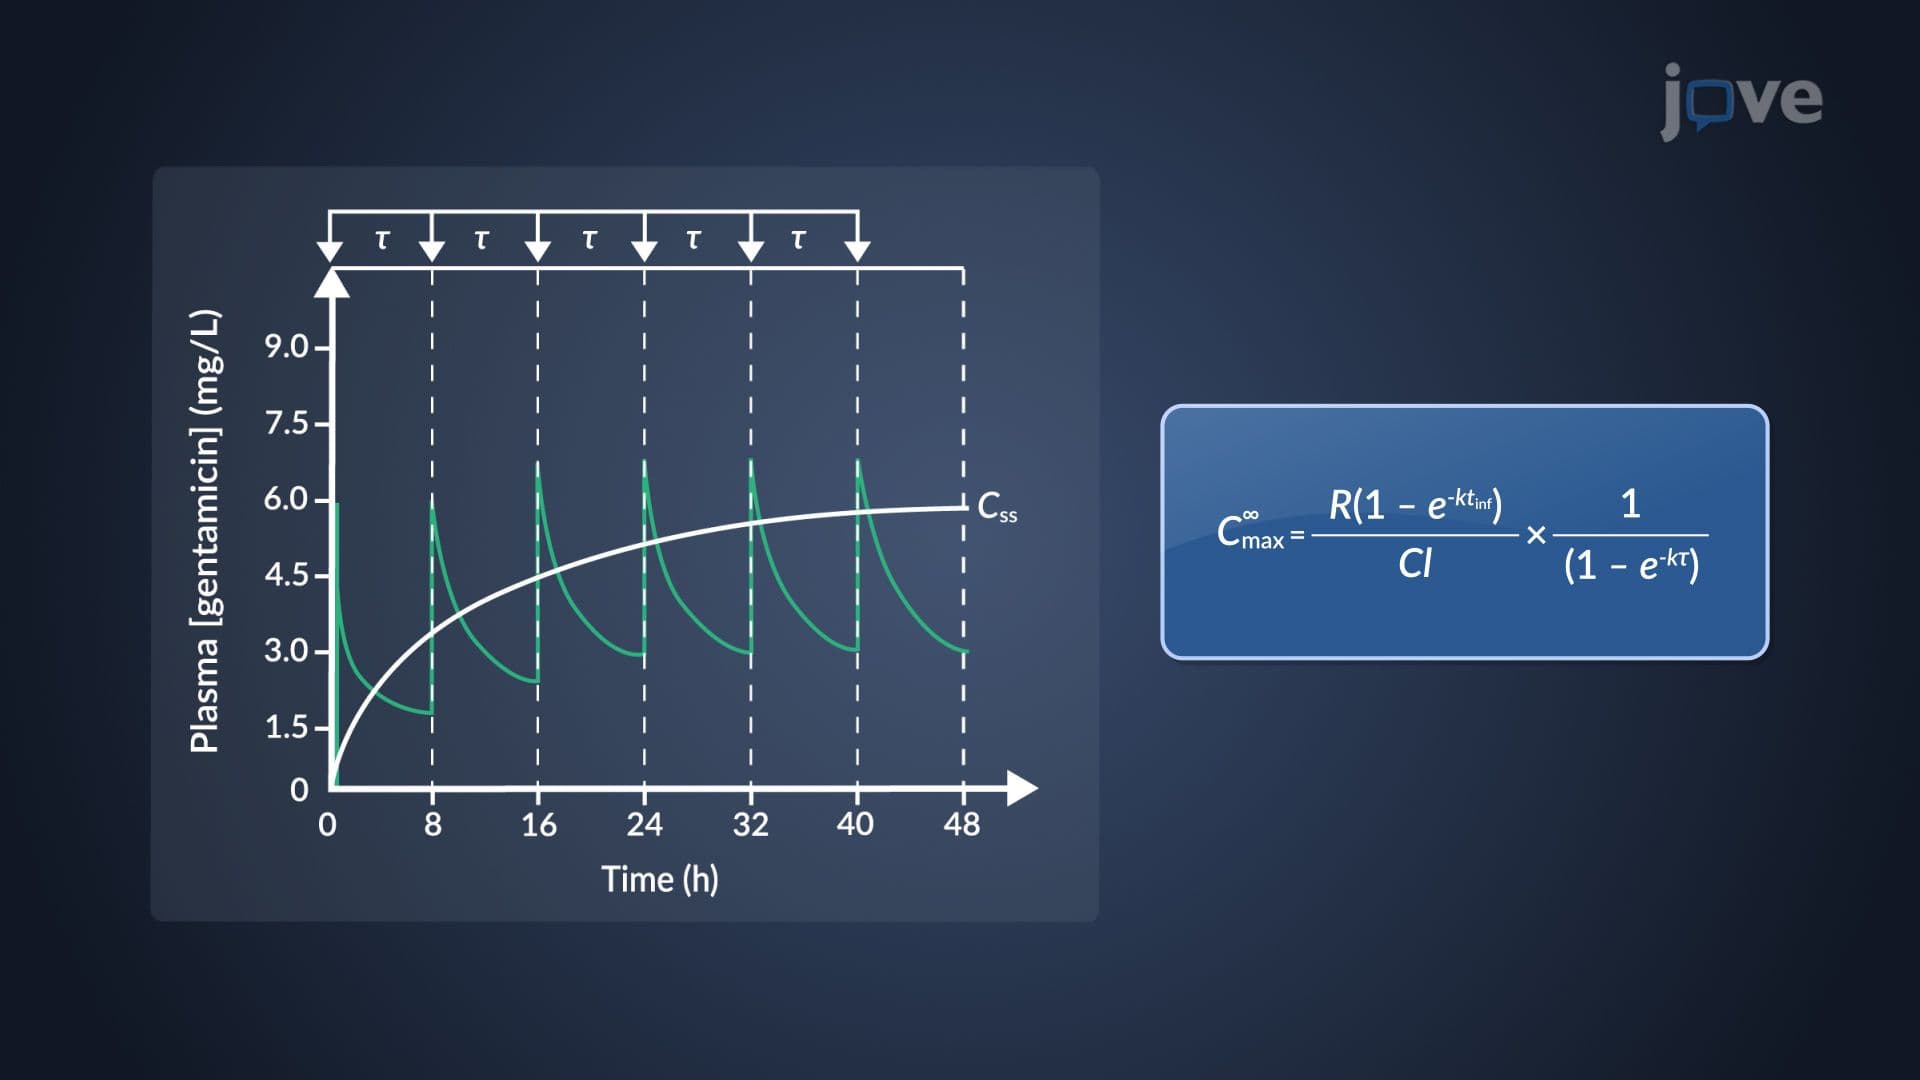
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:25
Determination of Multiple Dosing Parameters: Loading and Maintenance Doses
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:18
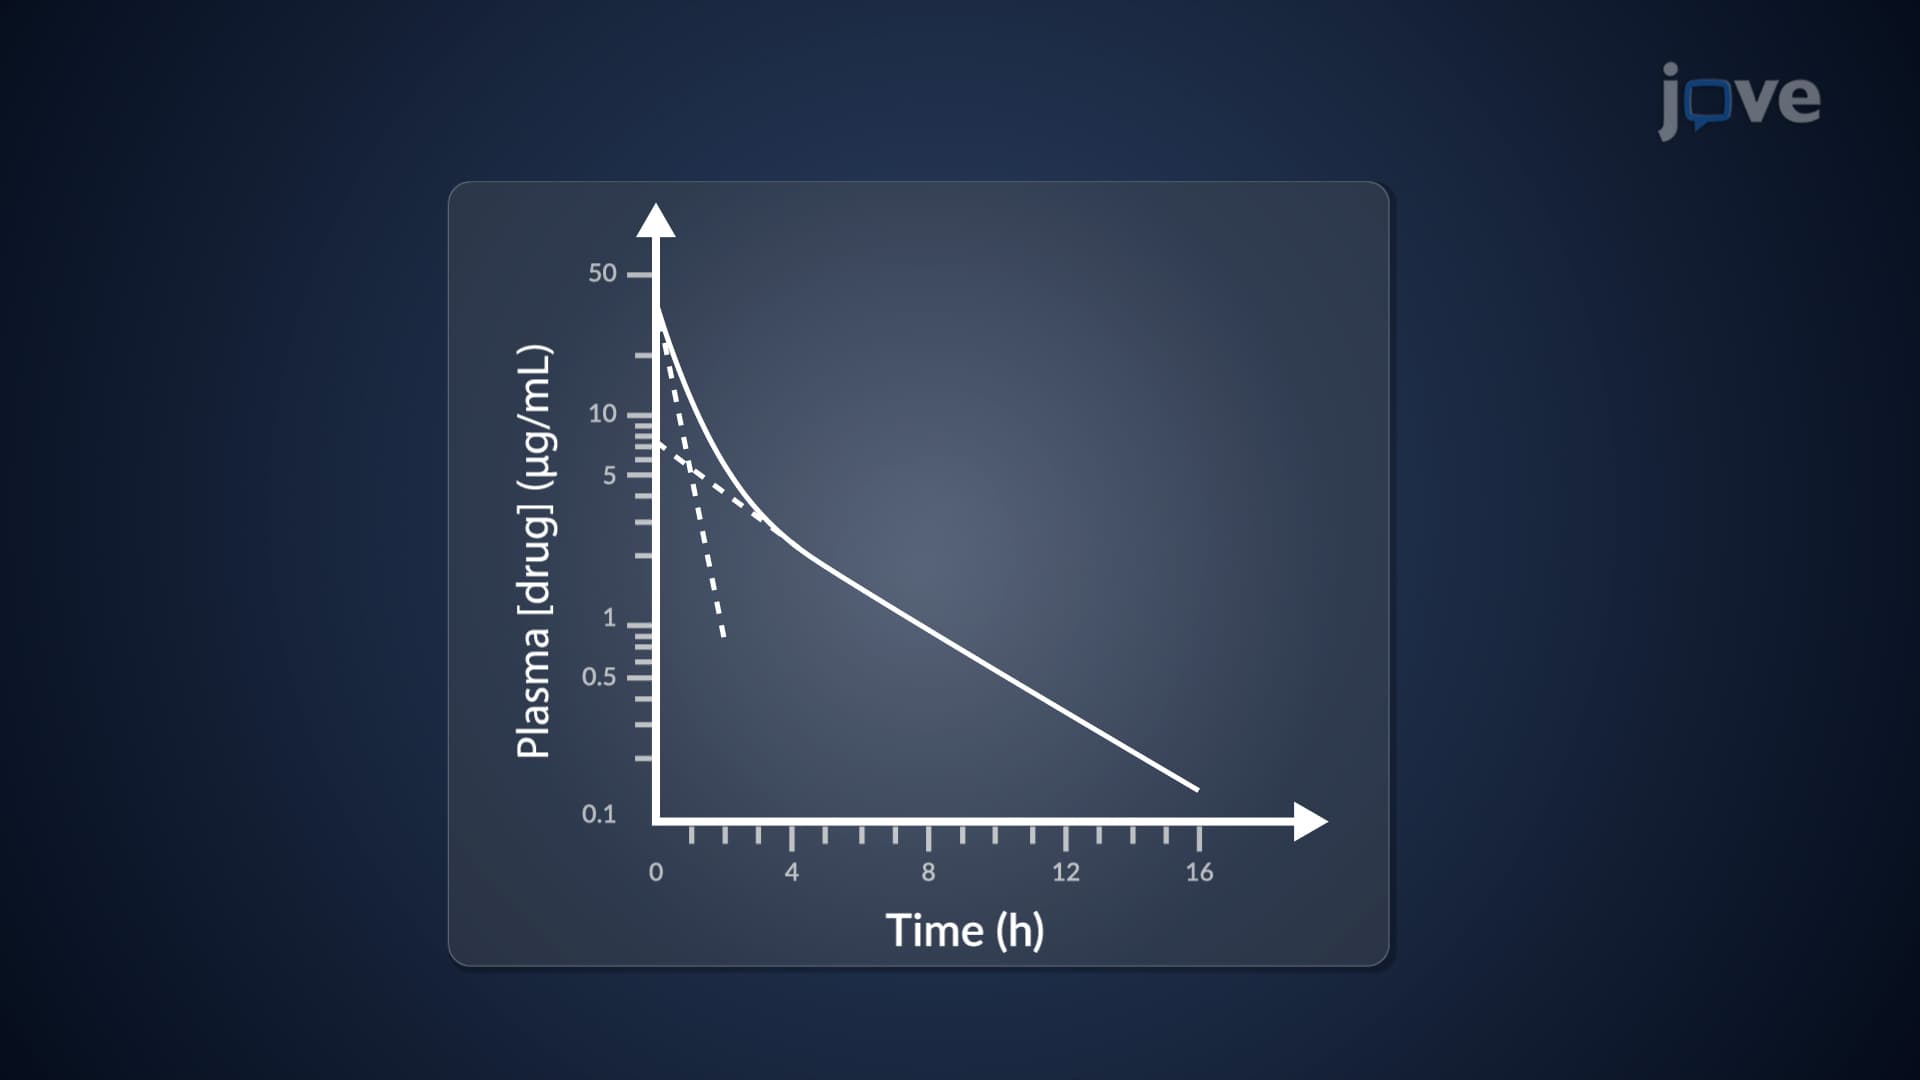
Two-Compartment Open Model: IV Bolus Administration
The disparity between drug input and the sum of drug transfer rates between...