Related Experiment Videos
Function and Ventilation of Large and Small Airways in Children and Adolescents with Inflammatory Bowel Disease
Sophie Yammine1, Sylvia Nyilas, Carmen Casaulta
1*Division of Pediatric Pulmonology, University Children's Hospital, Inselspital, University of Bern, Bern, Switzerland;†Division of Pediatric Pulmonology, University Children's Hospital, UKBB, University of Basel, Basel, Switzerland; and‡Division of Pediatric Gastroenterology, Hepatology and Nutrition, University Children's Hospital, Inselspital, University of Bern, Bern, Switzerland.

Background:
Extraintestinal manifestations are common among patients with inflammatory bowel disease (IBD), whereas pulmonary involvement is considered rare. However, chronic lung diseases begin with subclinical changes of the small airways and often originate in childhood. Pulmonary involvement, particularly of the small airways, can be assessed using novel inert gas washout tests.
Methods:
In this prospective, single-center study, 30 children and adolescents (mean age, 14 years; SD, ±2.6; 13 boys) with IBD (mean disease duration, 3.2 years; SD, ±2.8), and 32 healthy age-matched controls, performed nitrogen multiple-breath washout, double-tracer gas single-breath washout, and diffusion capacity for carbon monoxide. Patients with IBD additionally performed spirometry, plethysmography, and measurement of exhaled nitric oxide.
Results:
Patients with IBD demonstrated no abnormalities in classical lung function tests. There was no difference between active disease and remission. The lung clearance index, a very sensitive indicator for small airway function, did not differ between patients with IBD and healthy controls (mean difference [95% confidence interval] -0.01 [-0.28 to 0.25]). Specific markers for peripheral lung ventilation (Sacin and Scond) were also within the normal range (0.002 [-0.003 to 0.008] and -0.002 [-0.020 to 0.015], respectively). No association was found between measures of lung function and IBD subtype, clinical disease activity scores, laboratory values, treatment modalities, or disease duration.
Conclusions:
In our cohort of pediatric and adolescent patients with IBD without respiratory symptoms, there was no evidence of significant lung disease on extensive screening testing. General screening of asymptomatic patients therefore appears unnecessary and is not recommended in this population.
Related Concept Videos
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:23
The Bronchial Tree
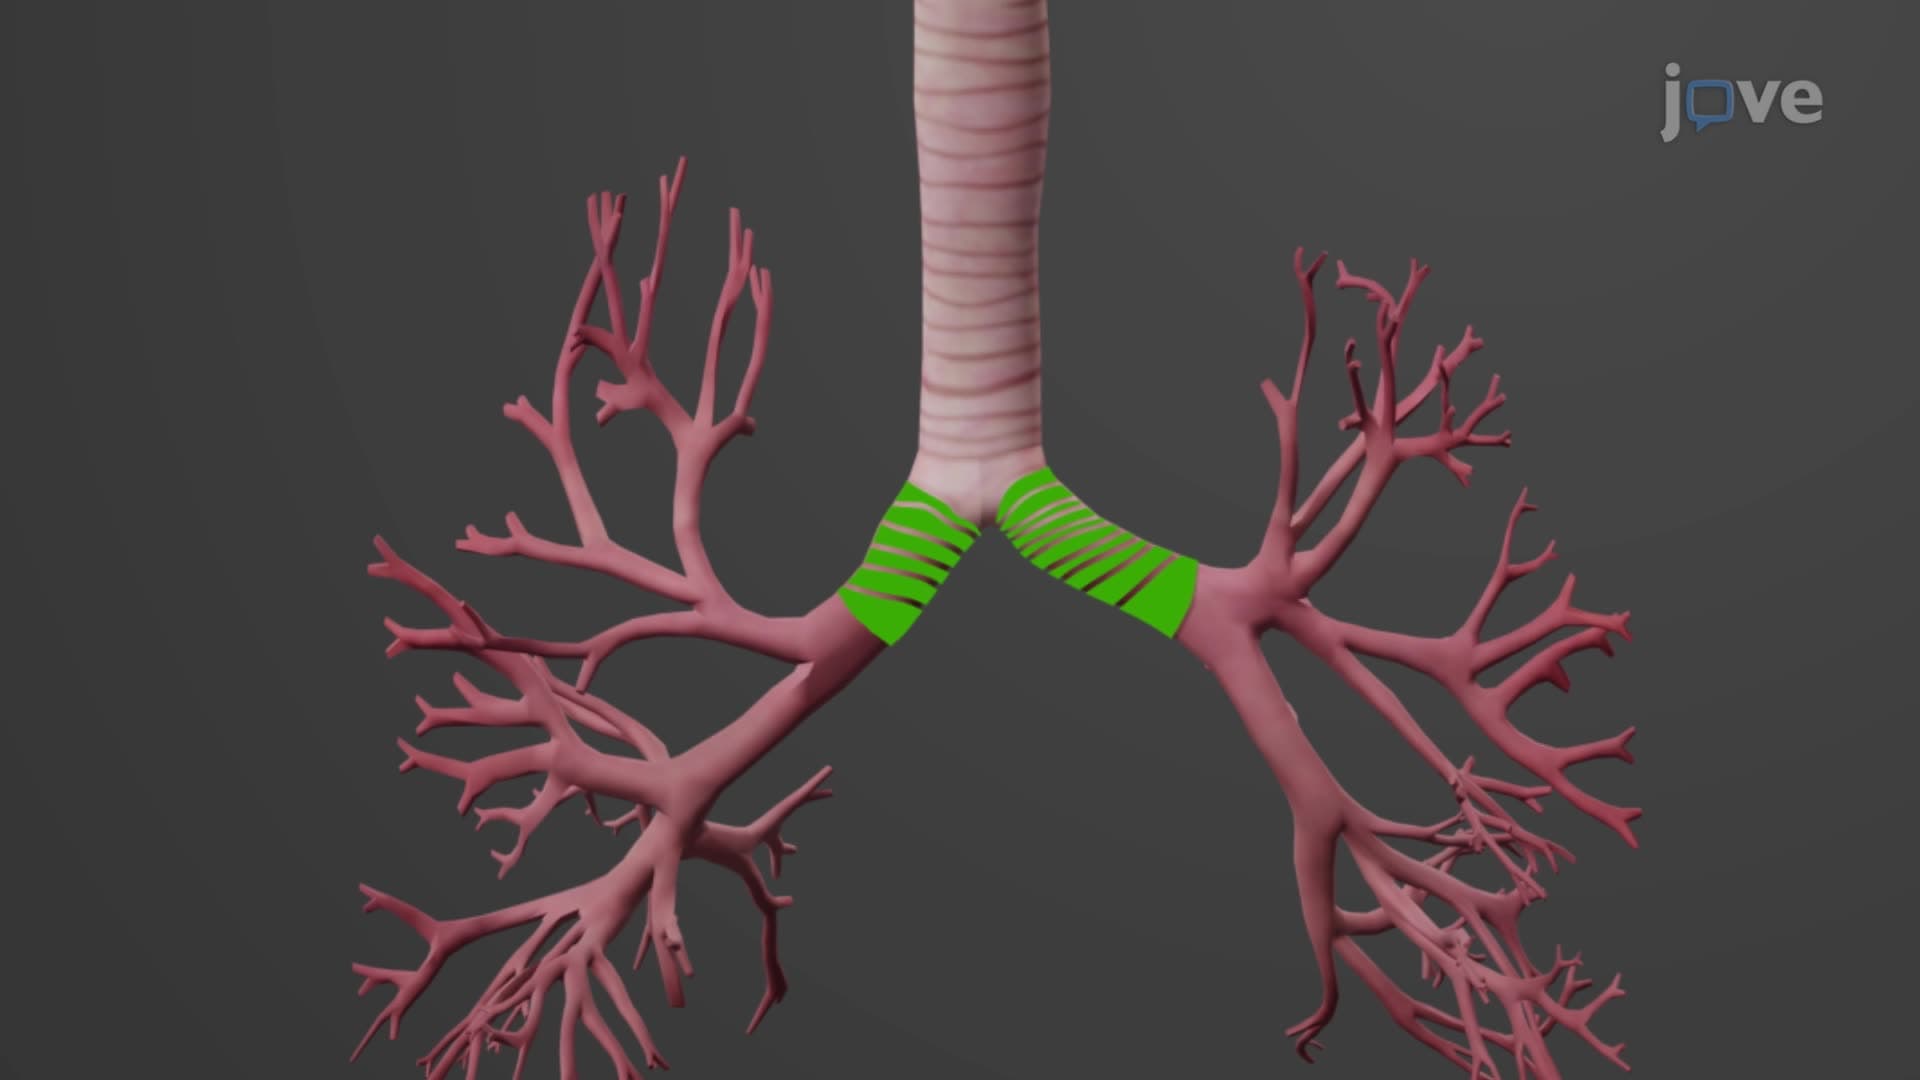
The trachea, commonly known as the windpipe, is a tube that connects the larynx (voice box) to the bronchi. At a point called the carina, it bifurcates into two primary bronchi. The right primary bronchus is wider, shorter, and more vertical than the left primary...
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:26
COPD: Management Using Bronchodilators and Corticosteroids