Related Experiment Video
Updated: Mar 22, 2026

Improving IV Insulin Administration in a Community Hospital
Published on: June 11, 2012
Personalized intensification of insulin therapy in type 2 diabetes - does a basal-bolus regimen suit all patients?
D Giugliano1, J Sieradzki2, A Stefanski3
1a Department of Medical, Surgical, Neurological, Metabolic Sciences and Aging , Second University of Naples , Naples , Italy ;

Many patients with type 2 diabetes mellitus (T2DM) require insulin therapy. If basal insulin fails to achieve glycemic control, insulin intensification is one possible treatment intensification strategy. We summarized clinical data from randomized clinical trials designed to compare the efficacy and safety of basal-bolus and premixed insulin intensification regimens. We defined a between-group difference of ≥0.3% in end-of-study glycated hemoglobin (HbA1c) as clinically meaningful. A PubMed database search supplemented by author-identified papers yielded 15 trials which met selection criteria: randomized design, patients with T2DM receiving basal-bolus (bolus injection ≤3 times/day) vs. premixed (≤3 injections/day) insulin regimens, primary/major endpoint(s) HbA1c- and/or hypoglycemia-related, and trial duration ≥12 weeks. Glycemic control improved with both basal-bolus and premixed insulin regimens with - in most cases - acceptable levels of weight gain and hypoglycemia. A clinically meaningful difference between regimens in glycemic control was recorded in only four comparisons, all of which favored basal-bolus therapy. The incidence of hypoglycemia was significantly different between regimens in only three comparisons, one of which favored premixed insulin and two basal-bolus therapy. Of the four trials that reported a significant difference between regimens in bodyweight change, two favored basal-bolus therapy and two favored premixed insulin. Thus, on a population level, neither basal-bolus therapy nor premixed insulin showed a consistent advantage in terms of glycemic control, hypoglycemic risk, or bodyweight gain. It is therefore recommended that clinicians should adopt an individualized approach to insulin intensification - taking into account the benefits and risks of each treatment approach and the attitude and preferences of each patient - in the knowledge that both basal-bolus and premixed regimens may be successful.
Many patients with type 2 diabetes mellitus (T2DM) require insulin therapy. If basal insulin fails to achieve glycemic control, insulin intensification is one possible treatment intensification strategy. We summarized clinical data from randomized clinical trials designed to compare the efficacy and safety of basal-bolus and premixed insulin intensification regimens. We defined a between-group difference of ≥0.3% in end-of-study glycated hemoglobin (HbA1c) as clinically meaningful. A PubMed database search supplemented by author-identified papers yielded 15 trials which met selection criteria: randomized design, patients with T2DM receiving basal-bolus (bolus injection ≤3 times/day) vs. premixed (≤3 injections/day) insulin regimens, primary/major endpoint(s) HbA1c- and/or hypoglycemia-related, and trial duration ≥12 weeks. Glycemic control improved with both basal-bolus and premixed insulin regimens with - in most cases - acceptable levels of weight gain and hypoglycemia. A clinically meaningful difference between regimens in glycemic control was recorded in only four comparisons, all of which favored basal-bolus therapy. The incidence of hypoglycemia was significantly different between regimens in only three comparisons, one of which favored premixed insulin and two basal-bolus therapy. Of the four trials that reported a significant difference between regimens in bodyweight change, two favored basal-bolus therapy and two favored premixed insulin. Thus, on a population level, neither basal-bolus therapy nor premixed insulin showed a consistent advantage in terms of glycemic control, hypoglycemic risk, or bodyweight gain. It is therefore recommended that clinicians should adopt an individualized approach to insulin intensification - taking into account the benefits and risks of each treatment approach and the attitude and preferences of each patient - in the knowledge that both basal-bolus and premixed regimens may be successful.
More Related Videos
 09:31
Sustained Administration of β-cell Mitogens to Intact Mouse Islets Ex Vivo Using Biodegradable Poly(lactic-co-glycolic acid) Microspheres
Published on: November 5, 2016
 06:13
Author Spotlight: Exploring the Impact of Reduced Resistance Exercise Volume on Metabolic Health
Published on: December 1, 2023
Related Concept Videos
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:27
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into...
 01:25
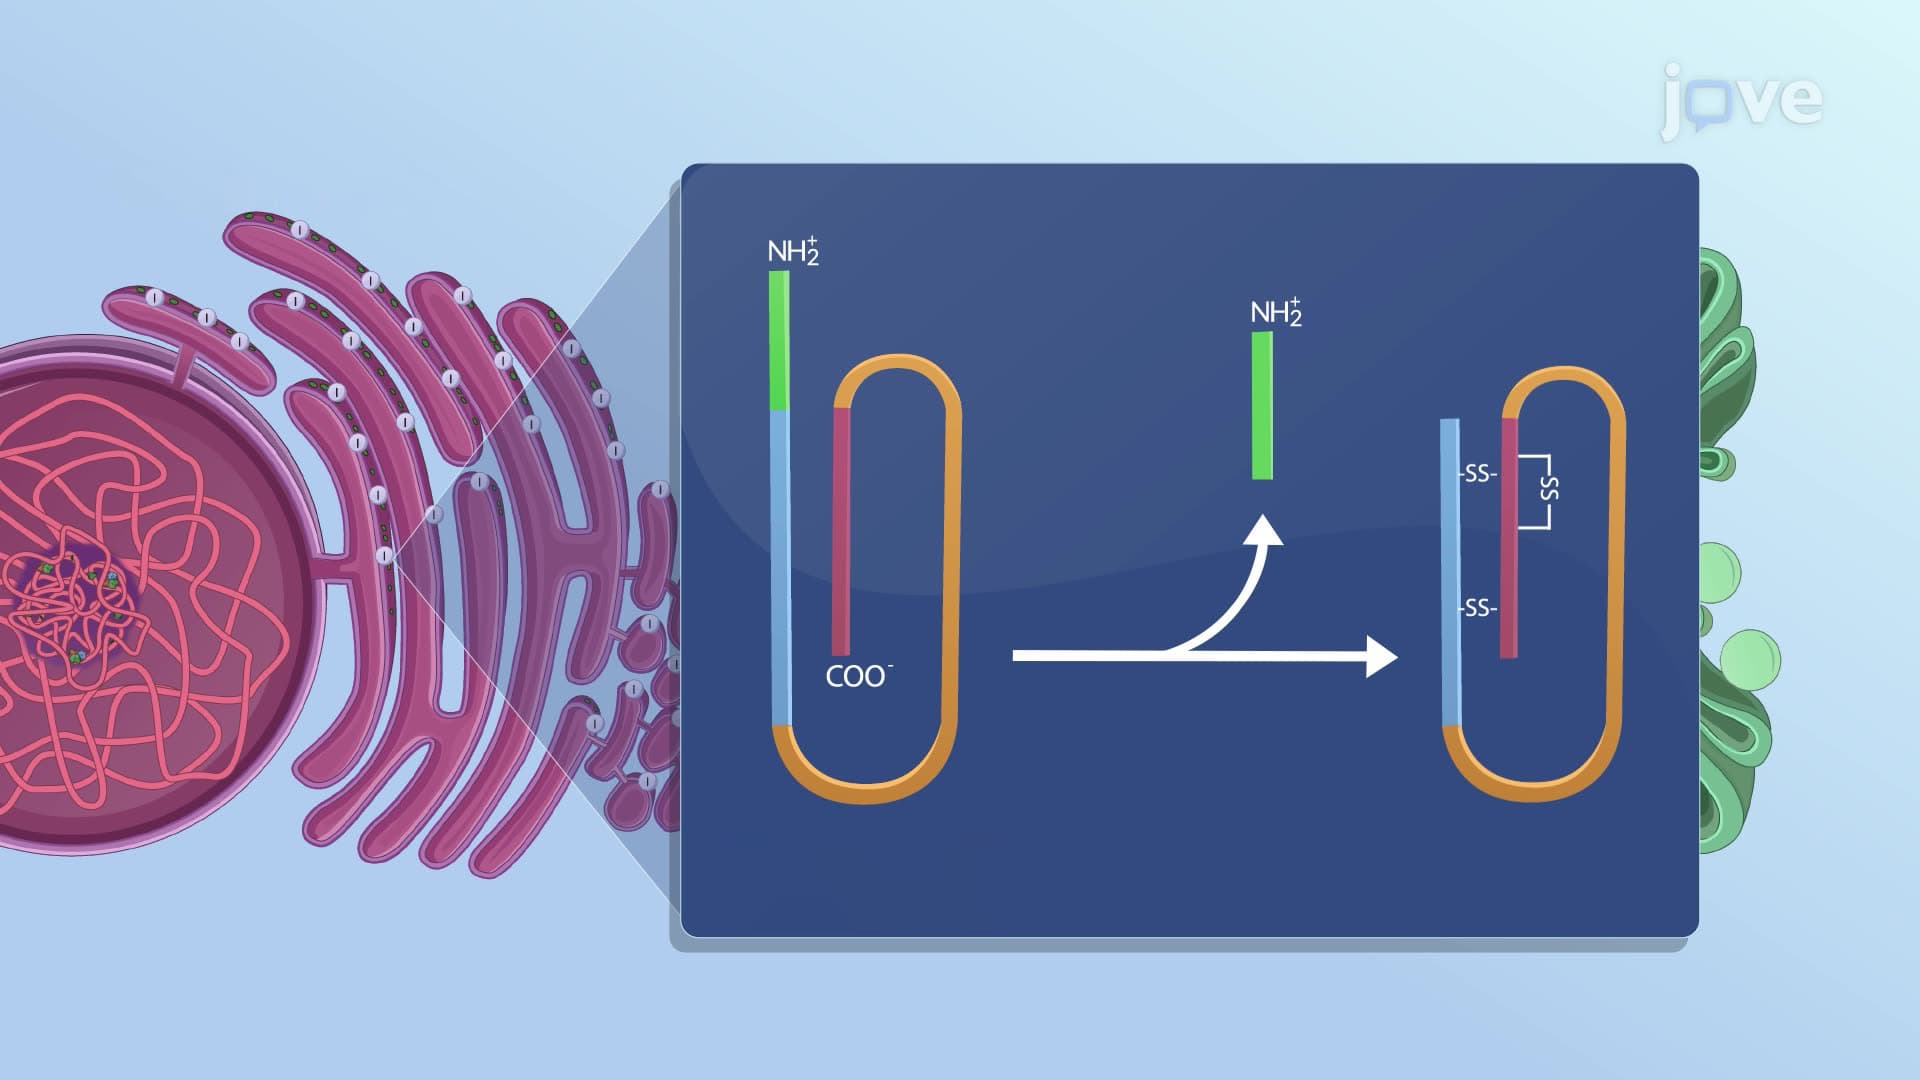
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment...
 01:24
Dosage Regimen: Individualization
 01:15
Diabetes: Management and Pharmacotherapy
Insulin remains the cornerstone of treatment for most patients with type 1 and many...
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...