Related Experiment Video
Updated: Mar 22, 2026


Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
How well do patients and providers agree on the severity of dyspnea?
Mihaela S Stefan1,2,3,4, Aruna Priya5, Benjamin Martin6
1Center for Quality of Care Research, Baystate Medical Center, Springfield, Massachusetts. mihaela.stefan@baystatehealth.org.

Background:
Understanding the severity of patients' dyspnea is critical to avoid under- or overtreatment of patients with acute cardiopulmonary conditions.
Objective:
To evaluate the agreement between dyspnea assessment by patients and healthcare providers and to explore which factors contribute to discordance in assessment.
Design, Settings And Participants:
Prospective study of patients hospitalized for acute cardiopulmonary diseases at an urban teaching hospital.
Intervention And Measurements:
A numerical rating scale (0-10) was used to assess dyspnea severity as perceived by patients and assessed by providers. Agreement was defined as a score within ±1 between patient and healthcare provider; differences of ≥2 points were considered over- or underestimations. The relationship between patient self-perceived dyspnea severity and provider rating was assessed using a weighted kappa coefficient.
Results:
Of the 138 patients enrolled, 33% had a diagnosis of heart failure, 30% chronic obstructive pulmonary disease, and 13% pneumonia; median age was 72 years, and 57% were women. In all, 96 patient-physician and 138 patient-nurses pairs were included in the study. The kappa coefficient for agreement was 0.11 (95% confidence interval [CI]: 0.01 to 0.21) between patients and physicians and 0.18 (95% CI: 0.12 to 0.24) between patients and nurses. Physicians underestimated patients' dyspnea 37.9% of the time and overestimated it 25.8% of the time, whereas nurses underestimated it 43.5% of the time and overestimated it 12.4% of the time. Admitting diagnosis was the only patient factor associated with discordance.
Conclusions:
Agreement between patient perception of dyspnea and healthcare providers' assessment is low. Future studies should prospectively test whether routine assessment of dyspnea results in better patient outcomes. Journal of Hospital Medicine 2016;11:701-707. © 2016 Society of Hospital Medicine.
More Related Videos
 03:25
Author Spotlight: Exploring Non-Pharmacological Therapies for Chronic Respiratory Diseases — Linking Intestinal Microbiome Insights to COPD Treatment
Published on: December 27, 2024
 02:34
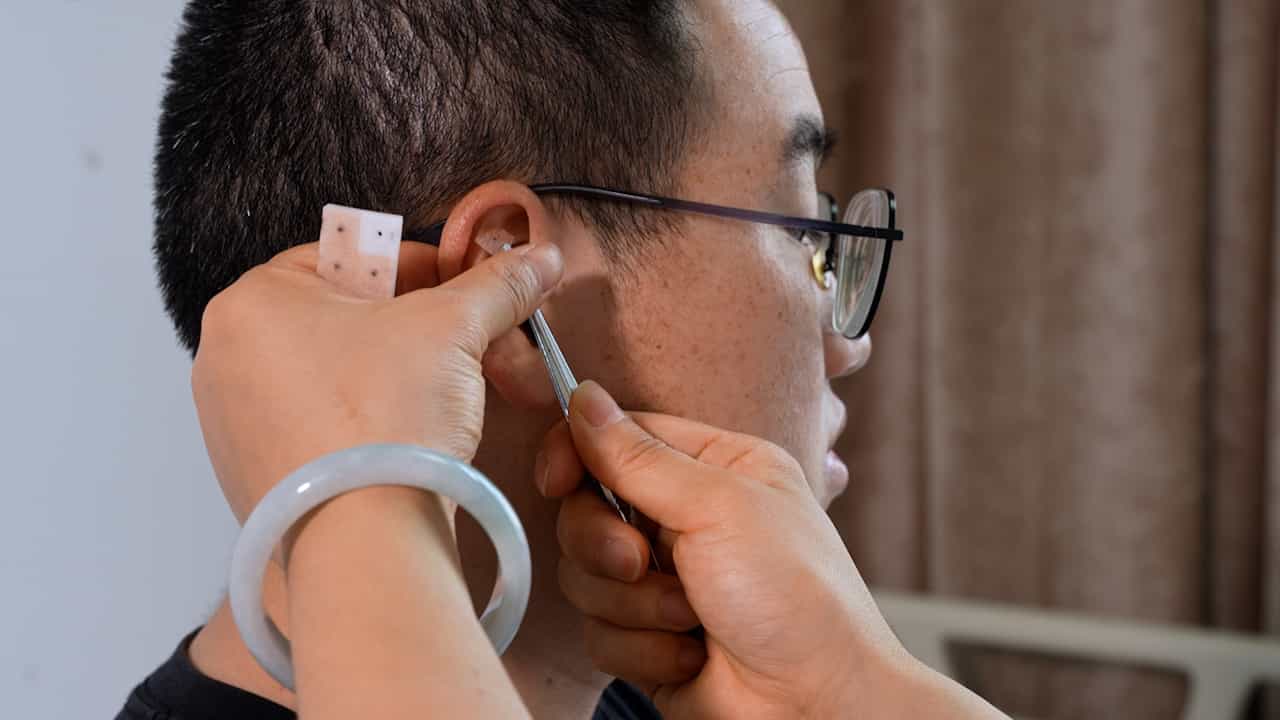
Author Spotlight: Efficacy of Auricular Pressure Bean Therapy in Reducing Wheezing Symptoms
Published on: May 10, 2024
Related Concept Videos
 01:30
Chronic Obstructive Pulmonary Disease-V: Nursing Management
Assessment
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
Smoking Cessation
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...
 01:26
Respiratory Volumes and Capacities I
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: