Related Experiment Video
Updated: Mar 21, 2026
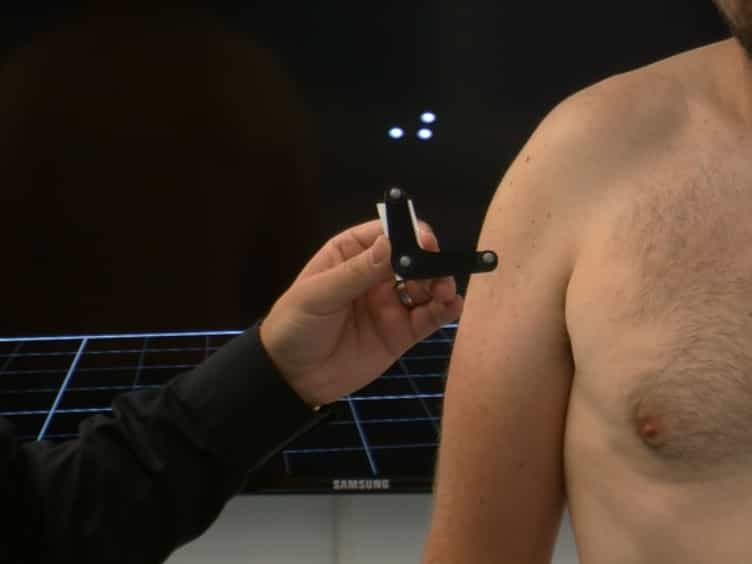
Measurement of Dynamic Scapular Kinematics Using an Acromion Marker Cluster to Minimize Skin Movement Artifact
Published on: February 10, 2015
Reliability of levator scapulae index in subjects with and without scapular downward rotation syndrome
Ji-Hyun Lee1, Heon-Seock Cynn1, Woo-Jeong Choi1
1Applied Kinesiology and Ergonomic Technology Laboratory, Department of Physical Therapy, The Graduate School, Yonsei University, Baekwoon-kwan, 1 Yonseidae-gil, Wonju, Kangwon-do, South Korea.

Objectives:
The objective of this study was to introduce levator scapulae (LS) measurement using a caliper and the levator scapulae index (LSI) and to investigate intra- and interrater reliability of the LSI in subjects with and without scapular downward rotation syndrome (SDRS).
Design:
Two raters measured LS length twice in 38 subjects (19 with SDRS and 19 without SDRS).
Main Outcome Measures:
For reliability testing, intraclass correlation coefficients (ICCs), standard error of measurement (SEM), and minimal detectable change (MDC) were calculated.
Results:
Intrarater reliability analysis resulted with ICCs ranging from 0.94 to 0.98 in subjects with SDRS and 0.96 to 0.98 in subjects without SDRS. These results represented that intrarater reliability in both groups were excellent for measuring LS length with the LSI. Interrater reliability was good (ICC: 0.82) in subjects with SDRS; however, interrater reliability was moderate (ICC: 0.75) in subjects without SDRS. Additionally, SEM and MDC were 0.13% and 0.36% in subjects with SDRS and 0.35% and 0.97% in subjects without SDRS. In subjects with SDRS, low dispersion of the measurement errors and MDC were shown.
Conclusions:
This study suggested that the LSI is a reliable method to measure LS length and is more reliable for subjects with SDRS.
Related Concept Videos
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...