Related Experiment Video
Updated: Mar 21, 2026
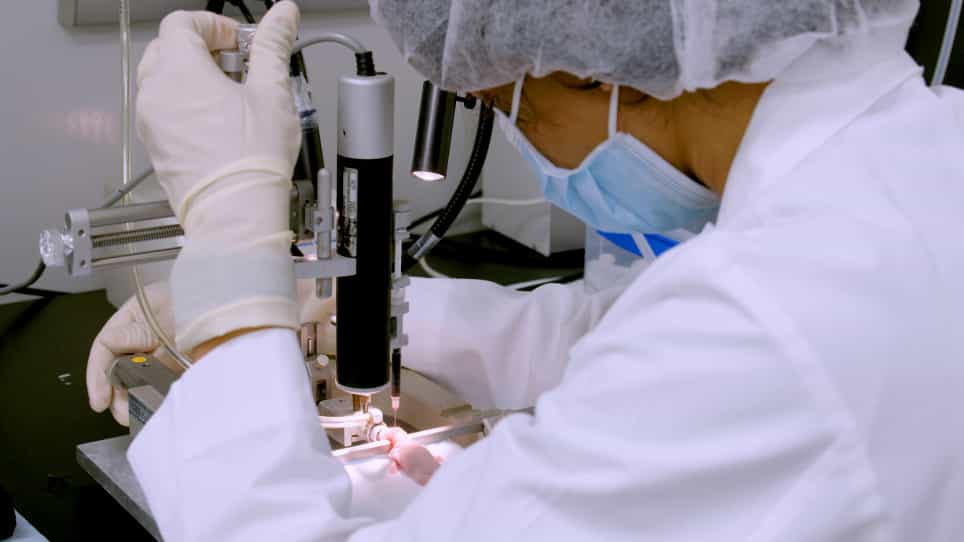
Modeling Neonatal Intraventricular Hemorrhage Through Intraventricular Injection of Hemoglobin
Published on: August 25, 2022
Heparin for the prevention of intraventricular haemorrhage in preterm infants
Matteo Bruschettini1, Olga Romantsik, Simona Zappettini
1Department of Paediatrics, Lund University, Skane University Hospital, Lund, Sweden.

Insights
Prophylactic heparin administration in very preterm infants did not show a significant reduction in intraventricular hemorrhage (IVH) or neonatal mortality. The limited data suggests that current evidence is insufficient to definitively determine heparin
Area of Science:
- Neonatal Medicine
- Pediatric Cardiology
- Hematology
Background:
- Preterm birth is a primary risk factor for intraventricular hemorrhage (IVH) in very low birth weight infants.
- IVH is believed to be venous in origin, with germinal matrix thromboses playing a potential triggering role.
- Heparin, an anticoagulant, activates antithrombin and may reduce the risk of IVH and parenchymal venous infarct.
Purpose of the Study:
- To evaluate the efficacy of prophylactic heparin in reducing germinal matrix-intraventricular hemorrhage (GMH-IVH) in very preterm neonates.
- To compare heparin administration against placebo, no treatment, or other anticoagulants for IVH prevention.
Main Methods:
- Systematic review and meta-analysis of randomized controlled trials, quasi-randomized controlled trials, and cluster trials.
- Searched major databases (Cochrane, MEDLINE, EMBASE, CINAHL) and congress abstracts (2000-2015).
- Included studies involved very preterm infants (gestational age < 32 weeks) receiving early heparin administration (within 24 hours of life).
Main Results:
- Two trials with 155 infants compared low-dose heparin to no heparin in very preterm newborns requiring umbilical catheterization.
- No significant differences were found in rates of IVH (RR 0.93, 95% CI 0.61-1.41), severe IVH (RR 1.01, 95% CI 0.46-2.23), or neonatal mortality (RR 0.69, 95% CI 0.28-1.67).
- Evidence quality was very low to low, with imprecision in estimates and limitations in study designs. Limited data existed for other outcomes, and no long-term neurodevelopmental data was available.
Conclusions:
- Very limited data exists on prophylactic heparin's effect on IVH incidence and severity in very preterm neonates.
- The identified trials used heparin for umbilical line patency, not specifically for GMH-IVH prevention.
- The imprecise estimates mean results are consistent with potential benefit or harm, precluding a definitive answer on heparin's efficacy for IVH prevention.
Background:
Preterm birth remains the major risk factor for the development of intraventricular haemorrhage, an injury that occurs in 25% of very low birth weight infants. Intraventricular haemorrhage is thought to be venous in origin and intrinsic thromboses in the germinal matrix are likely to play a triggering role. Heparin activates antithrombin and promotes the inactivation of thrombin and other target proteinases. The administration of anticoagulants such as heparin may offset the increased risk of developing intraventricular haemorrhage and may also reduce the risk of developing parenchymal venous infarct, a condition known to complicate intraventricular haemorrhage.
Objectives:
To assess whether the prophylactic administration of heparin reduces the incidence of germinal matrix-intraventricular haemorrhage in very preterm neonates when compared to placebo, no treatment, or other anticoagulants.
Search Methods:
We searched the Cochrane Central Register of Controlled Trials (The Cochrane Library 2015), MEDLINE (1996 to 22 November 2015), EMBASE (1980 to 22 November 2015) and CINAHL (1982 to 22 November 2015), applying no language restrictions. We searched the abstracts of the major congresses in the field (Perinatal Society of Australia and New Zealand and Pediatric Academic Societies) from 2000 to 2015.
Selection Criteria:
Randomised controlled trials, quasi-randomised controlled trials and cluster trials comparing the administration of early, i.e. within the first 24 hours of life, heparin in very preterm infants (gestational age < 32 weeks).
Data Collection And Analysis:
For each of the included trials, two authors independently extracted data (e.g. number of participants, birth weight, gestational age, dose of heparin, mode of administration, and duration of therapy, etc.) and assessed the risk of bias (e.g. adequacy of randomisation, blinding, completeness of follow up). The primary outcomes considered in this review are intraventricular haemorrhage, severe intraventricular haemorrhage and neonatal mortality.
Main Results:
Two randomised controlled trials enrolling a total of 155 infants met the inclusion criteria of this review. Both trials compared low-dose heparin to the same solution without heparin in very preterm newborns requiring umbilical catheterisation. No trials were identified that specifically studied the use of heparin in infants at risk of germinal matrix-intraventricular haemorrhage.We found no differences in the rates of intraventricular haemorrhage (typical RR 0.93, 95% CI 0.61 to 1.41; typical RD -0.03, 95% CI -0.17 to 0.12; 2 studies, 155 infants; I² = 57% for RR and I² = 65% for RD), severe intraventricular haemorrhage (typical RR 1.01, 95% CI 0.46 to 2.23; typical RD 0.00, 95% CI -0.11 to 0.11; 2 studies, 155 infants; I² = 0% for RR and I² = 0% for RD) and neonatal mortality (typical RR 0.69, 95% CI 0.28 to 1.67; typical RD -0.04, 95% CI -0.14 to 0.06; 2 studies, 155 infants; I² = 28% for RR and I² = 50% for RD). We judged the quality of the evidence supporting these findings as very low (rates of intraventricular haemorrhage) and low (severe intraventricular haemorrhage and neonatal mortality) mainly because of limitations in the study designs and the imprecision of estimates. We found very few data on other relevant outcomes, such as bronchopulmonary dysplasia, pulmonary haemorrhage and patent ductus arteriosus; and no study assessing long-term outcomes (e.g. neurodevelopmental disability).
Authors' Conclusions:
There is very limited data on the effect of prophylactic administration of heparin on the incidence and severity of IVH in very preterm neonates. Both the identified trials used heparin in the context of maintaining umbilical line patency and not specifically as an agent to prevent germinal matrix-intraventricular haemorrhage. Given the imprecision of our estimates, the results of this systematic review are consistent with either a benefit or a detrimental effect of heparin and do not provide a definitive answer to the review question. Limited evidence is available on other clinically relevant outcomes.


Related Concept Videos
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:29
Venous Thrombosis III: Interprofessional Care