Related Experiment Video
Updated: Jun 19, 2026

Determination of the Transport Rate of Xenobiotics and Nanomaterials Across the Placenta using the ex vivo Human Placental Perfusion Model
Published on: June 18, 2013
Flurbiprofen in post-partum women: plasma and breast milk disposition
I J Smith1, J L Hinson, V A Johnson
1Department of Pharmacology, Louisiana State University Medical Center, Shreveport 71130.

The plasma and milk disposition of flurbiprofen (FB) was assessed in healthy women during the early post-partum period after multiple doses of FB. The results confirmed that a pragmatic study design is an attainable requirement for definitive statements about the excretion of FB in transitional milk. Nine doses of FB (50 mg per dose) were administered during three days. Paired milk and plasma samples were obtained during this period of dosing as well as after the last dose. The plasma data were used to derive an equation, which was then used to simulate cumulative plasma profiles for multiple doses given at unequal time intervals. The observed data corresponded to the simulated cumulative profiles of FB in plasma. The plasma elimination half-life of FB during early lactation was slightly prolonged (mean 4.8 hrs) as compared to reported values for normal adult men. The peak plasma concentrations of FB were comparable to those reported for healthy volunteers. In 10 of 12 women (3-5 days post-partum) the FB concentration in breast milk was less than 0.050 micrograms/ml. In two women the milk concentrations of FB were 0.06, 0.07 and 0.07 micrograms/ml as found in only three samples. We conclude that, on the basis of dose found in milk, FB is safe for women breast feeding their infants in the early post-partum period.
The plasma and milk disposition of flurbiprofen (FB) was assessed in healthy women during the early post-partum period after multiple doses of FB. The results confirmed that a pragmatic study design is an attainable requirement for definitive statements about the excretion of FB in transitional milk. Nine doses of FB (50 mg per dose) were administered during three days. Paired milk and plasma samples were obtained during this period of dosing as well as after the last dose. The plasma data were used to derive an equation, which was then used to simulate cumulative plasma profiles for multiple doses given at unequal time intervals. The observed data corresponded to the simulated cumulative profiles of FB in plasma. The plasma elimination half-life of FB during early lactation was slightly prolonged (mean 4.8 hrs) as compared to reported values for normal adult men. The peak plasma concentrations of FB were comparable to those reported for healthy volunteers. In 10 of 12 women (3-5 days post-partum) the FB concentration in breast milk was less than 0.050 micrograms/ml. In two women the milk concentrations of FB were 0.06, 0.07 and 0.07 micrograms/ml as found in only three samples. We conclude that, on the basis of dose found in milk, FB is safe for women breast feeding their infants in the early post-partum period.


Related Concept Videos
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:29
Drug Distribution: Plasma Protein Binding
 01:09
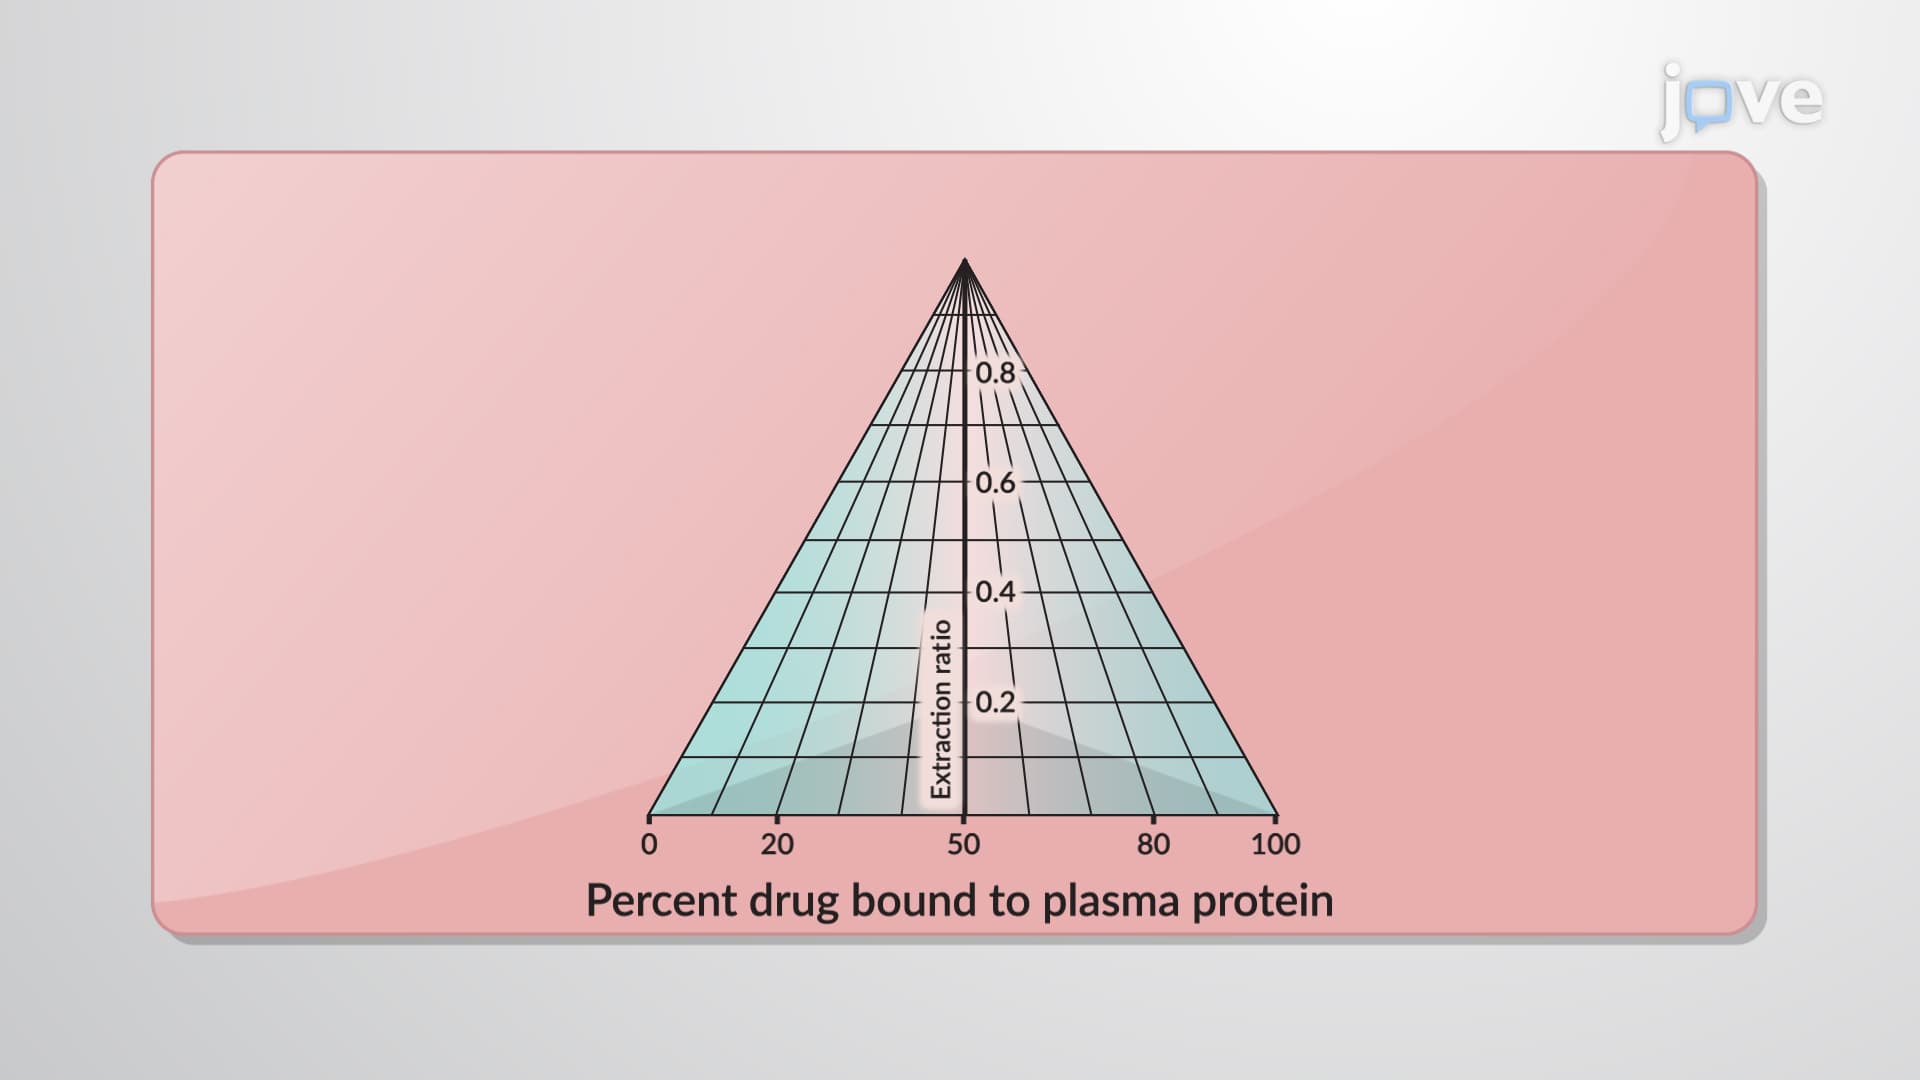
Hepatic Drug Clearance: Effect of Protein Binding
For low-extraction-ratio drugs that are less than 80% protein-bound, minor changes in protein binding...
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism