Related Experiment Video
Updated: Mar 21, 2026
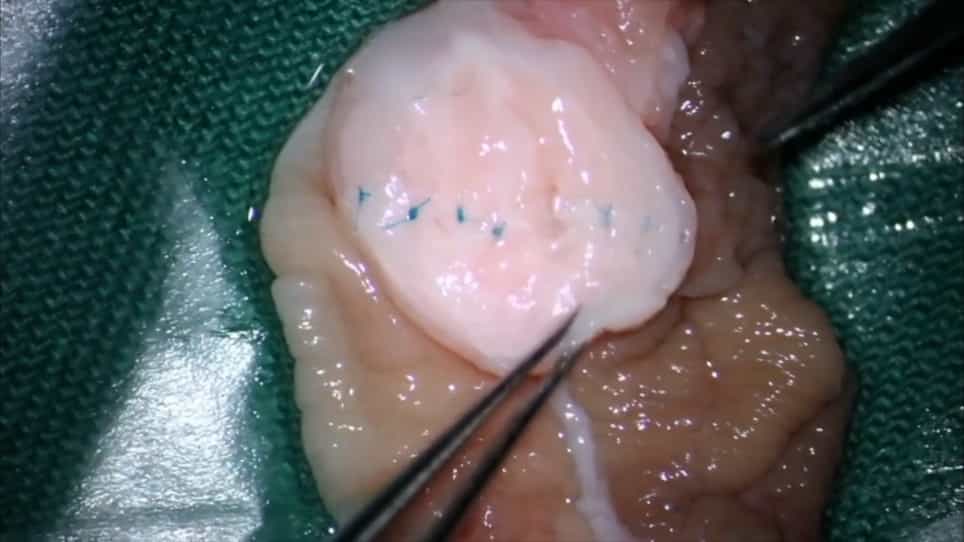

Microscopic Replantation of Penile Glans Amputation Due to Circumcision
Published on: June 3, 2022
Pediatric penile reconstruction using autologous split-thickness skin graft
E C Diaz1, J F Corcoran2, E K Johnson3
1Department of Urology, Stanford University Medical Center, 300 Pasteur Drive, Room S-287, Stanford, CA 94305, USA.

Insights
Penile entrapment after circumcision can be treated with penile reconstruction using autologous split-thickness skin grafts (STSG). Proper surgical technique and post-operative care are crucial for successful outcomes in pediatric patients.
Area of Science:
- Urology
- Pediatric Surgery
- Reconstructive Surgery
Background:
- Penile entrapment is a rare complication following circumcision, often due to excessive skin removal.
- Reconstruction may be necessary to restore penile anatomy and function.
Purpose of the Study:
- To present a case report on pediatric penile reconstruction using autologous split-thickness skin graft (STSG).
- To detail the technical aspects and key considerations for successful STSG in this context.
Main Methods:
- Autologous split-thickness skin graft (STSG) harvested from the lateral thigh using a dermatome.
- Meticulous hemostasis and elimination of redundant tissue to ensure graft adherence.
- Application of a pressure dressing or bolster for 5 days to promote graft uptake.
Main Results:
- Successful reconstruction of the penis using STSG.
- Demonstrated importance of infection prevention, graft-to-wound bed contact, and appropriate dressing techniques.
- Highlighted the risk of lymphedema with excessive distal skin excision.
Conclusions:
- Autologous STSG is a viable option for pediatric penile reconstruction after entrapment.
- Careful surgical technique, including adequate hemostasis and graft fixation, is essential.
- Preventing excessive distal skin excision is crucial to avoid complications like lymphedema.
Abstract:
This video provides a case report of penis entrapment secondary to excessive skin removal during circumcision. It highlights the technical aspects of pediatric penile reconstruction using autologous split-thickness skin graft (STSG). Key points include: 1. Infection prevention is paramount and antibiotic prophylaxis is routine. 2. The usual harvest site for the STSG is the lateral thigh because of its source of glabrous skin and convenient proximity to the penis. The lateral thigh is also outside of the diapered area, which helps lessen postoperative pain and infectious risks. 3. A dermatome is used to harvest the STSG. Skin thickness for penis coverage at this age is usually 10-12/1000 of an inch. 4. Direct contact of the graft and wound bed is essential for graft uptake. Hemostasis of the wound bed is critical to prevent hematoma formation. Elimination of redundant tissue is also important to ensure maximal contact between the graft and underlying wound bed. 5. A pressure dressing or bolster is used to prevent shear, and provide contact between the graft and wound bed for at least the first 5 days. 6. A semi-occlusive dressing, Tegaderm, was used on the donor site and it is believed that it provides a moist environment conducive for epithelial and dermal healing. 7. Lymphedema can result if excess distal penile skin is not excised. It is prudent to limit the amount of mucosal collar or consider direct anastomosis to the glans.
More Related Videos
 03:55
Urethroplasty with Pedicled Tunica Vaginalis for the Treatment of Long-segment Anterior Urethral Stricture Caused by Lichen Sclerosus of Glans Penis
Published on: October 18, 2024
 02:21
Microscopic Electric Rotary Grinding of Plaques Combined with Graft Repair in the Management of Peyronie's Disease
Published on: March 15, 2024
