Related Experiment Video
Updated: Mar 21, 2026
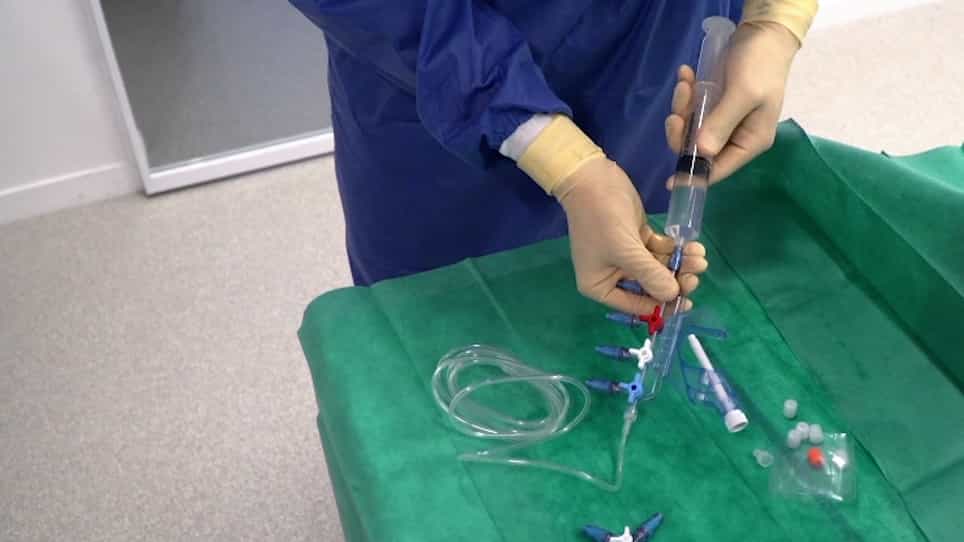

A Protocol to Set Up Needle-Free Connector with Positive Displacement on Central Venous Catheter in Intensive Care Unit
Published on: July 13, 2019
The dilemma of protein delivery in the intensive care unit
Lizl Veldsman1, Guy A Richards2, Renee Blaauw1
1Division of Human Nutrition, Faculty of Medicine and Health Sciences, Stellenbosch University, Cape Town, South Africa.

Objective:
Optimal protein delivery in the intensive care unit (ICU) may offer a significant mortality benefit, whereas energy overfeeding leads to worse outcomes. The aim of the present study was to assess actual protein versus energy delivery in a multidisciplinary adult ICU.
Methods:
We conducted a retrospective review of ICU charts to determine total protein delivery and energy delivery, inclusive of non-nutritional energy sources (NNES), from admission until a maximum of 7 d. The outcome variables were protein and energy delivery relative to targets and cumulative protein and energy balance.
Results:
We included 71 patients (49% male), with a mean age of 49.2 ± 17.1 y. Of the patients, 68% were medical and 32% surgical. Nutrition therapy was initiated within 14.5 ± 14.1 h. The majority (80%) received enteral nutrition (EN). Median protein delivery and energy delivery were 75 g/d (1.1 g·kg·d(-1), range 21-135 g/d) and 1642 kcal/d (26 kcal·kg·d(-1), range 740-2619 kcal/d), meeting 89% (range 24-103%) and 100% (range 39-133%) of target, respectively. NNES, mostly from carbohydrate-containing intravenous fluids, contributed 8% (range 0-29%) to total energy delivery (133 kcal/d, range 0-561). Protein and energy underfeeding occurred in 51% and 27% of cases, respectively. Only 59% of those with an adequate energy delivery (90-110% of target) achieved an adequate protein delivery. A significant negative correlation was found between cumulative protein and energy balance and time to initiation of NT (protein: R = -0.33, P = 0.006; energy: R = -0.28, P = 0.017).
Conclusions:
Early initiation of EN with currently available energy-rich formulas is insufficient to achieve adequate protein delivery. NNES add to total energy delivery. Novel EN formulas with a lower nonprotein energy-to-nitrogen ratio may help to optimize protein delivery without the harmful effects of energy overfeeding.
More Related Videos
 09:36
Halogenated Agent Delivery in Porcine Model of Acute Respiratory Distress Syndrome via an Intensive Care Unit Type Device
Published on: September 24, 2020
 06:59
A Novel Approach for the Administration of Medications and Fluids in Emergency Scenarios and Settings
Published on: November 9, 2016
Related Concept Videos
 01:29
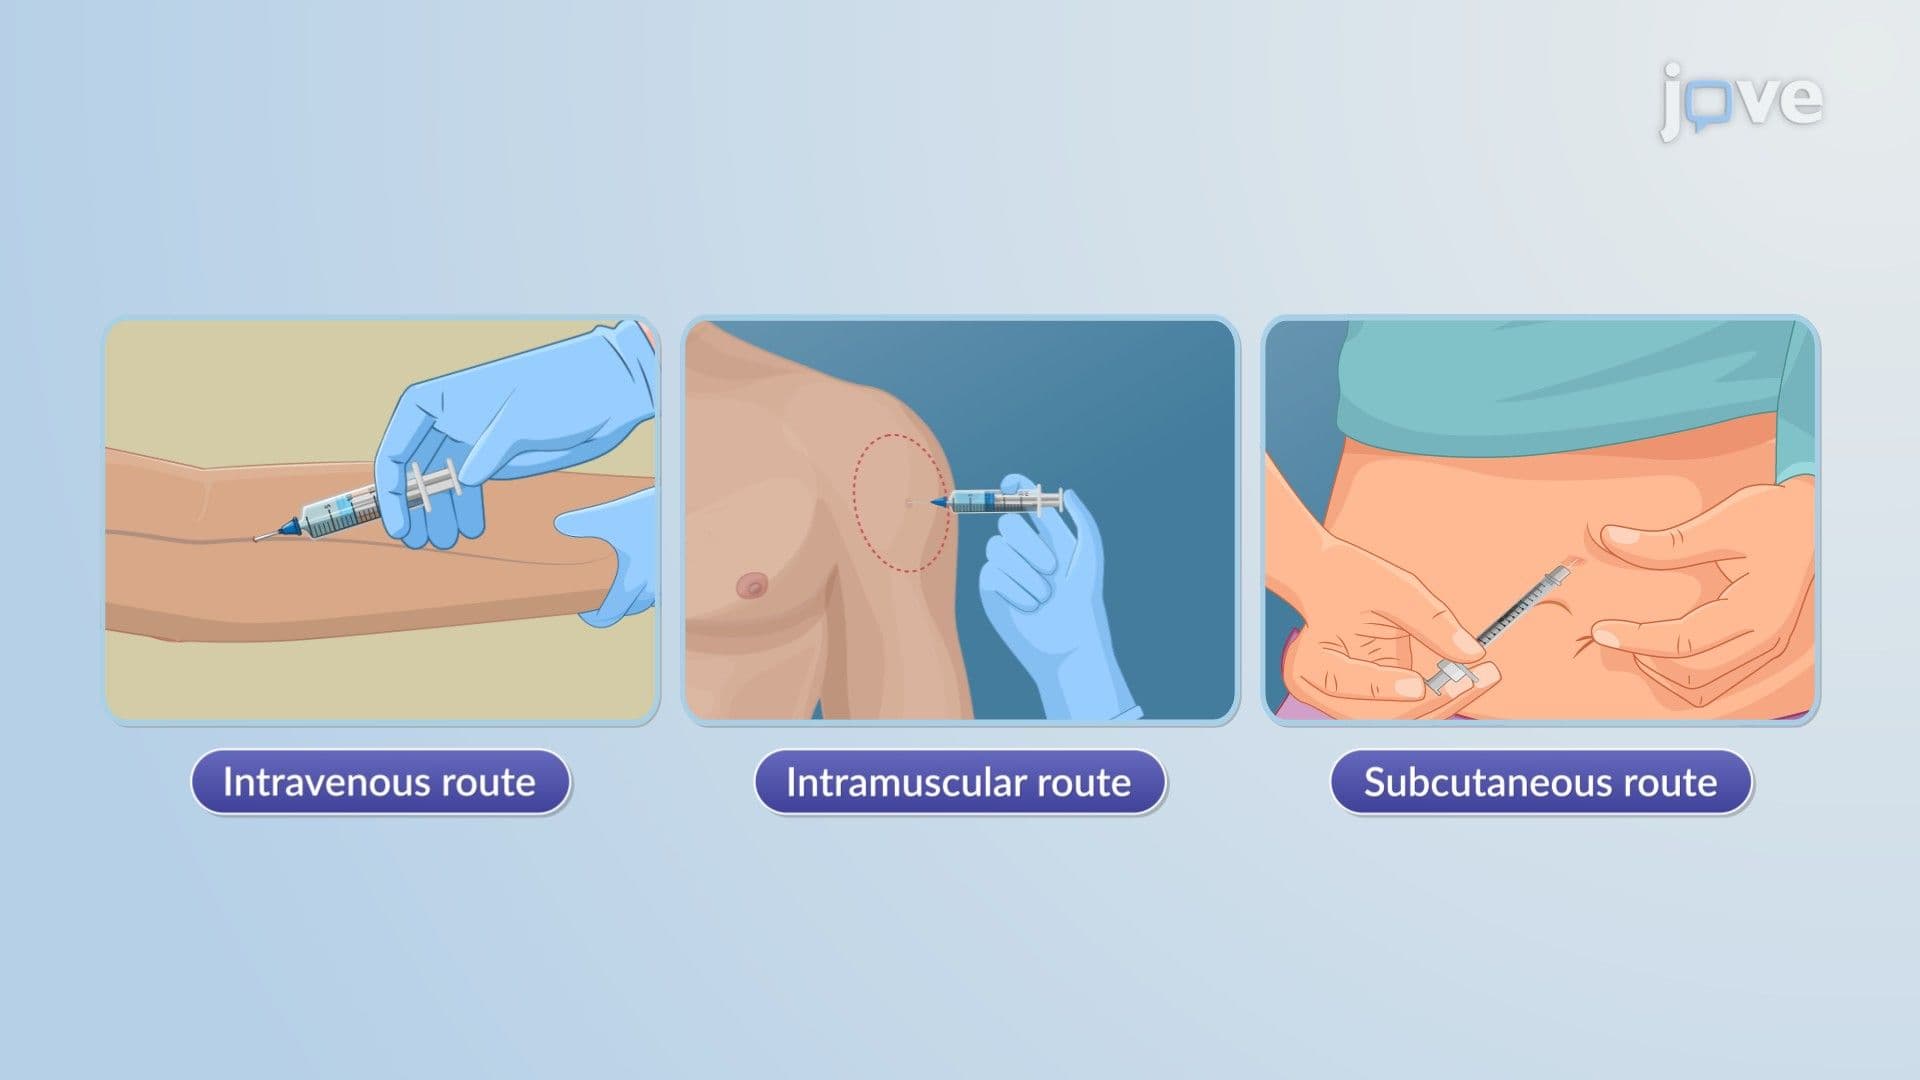
Drug Delivery: Parenteral Route
There are three primary parenteral routes: intravenous (IV), intramuscular (IM), and subcutaneous (SC). The IV route introduces the drug directly into the bloodstream, ensuring immediate action. The IM route...
 01:28
Parenteral Drug Delivery Systems: Injectables, Implants, and Infusion Devices
 01:16
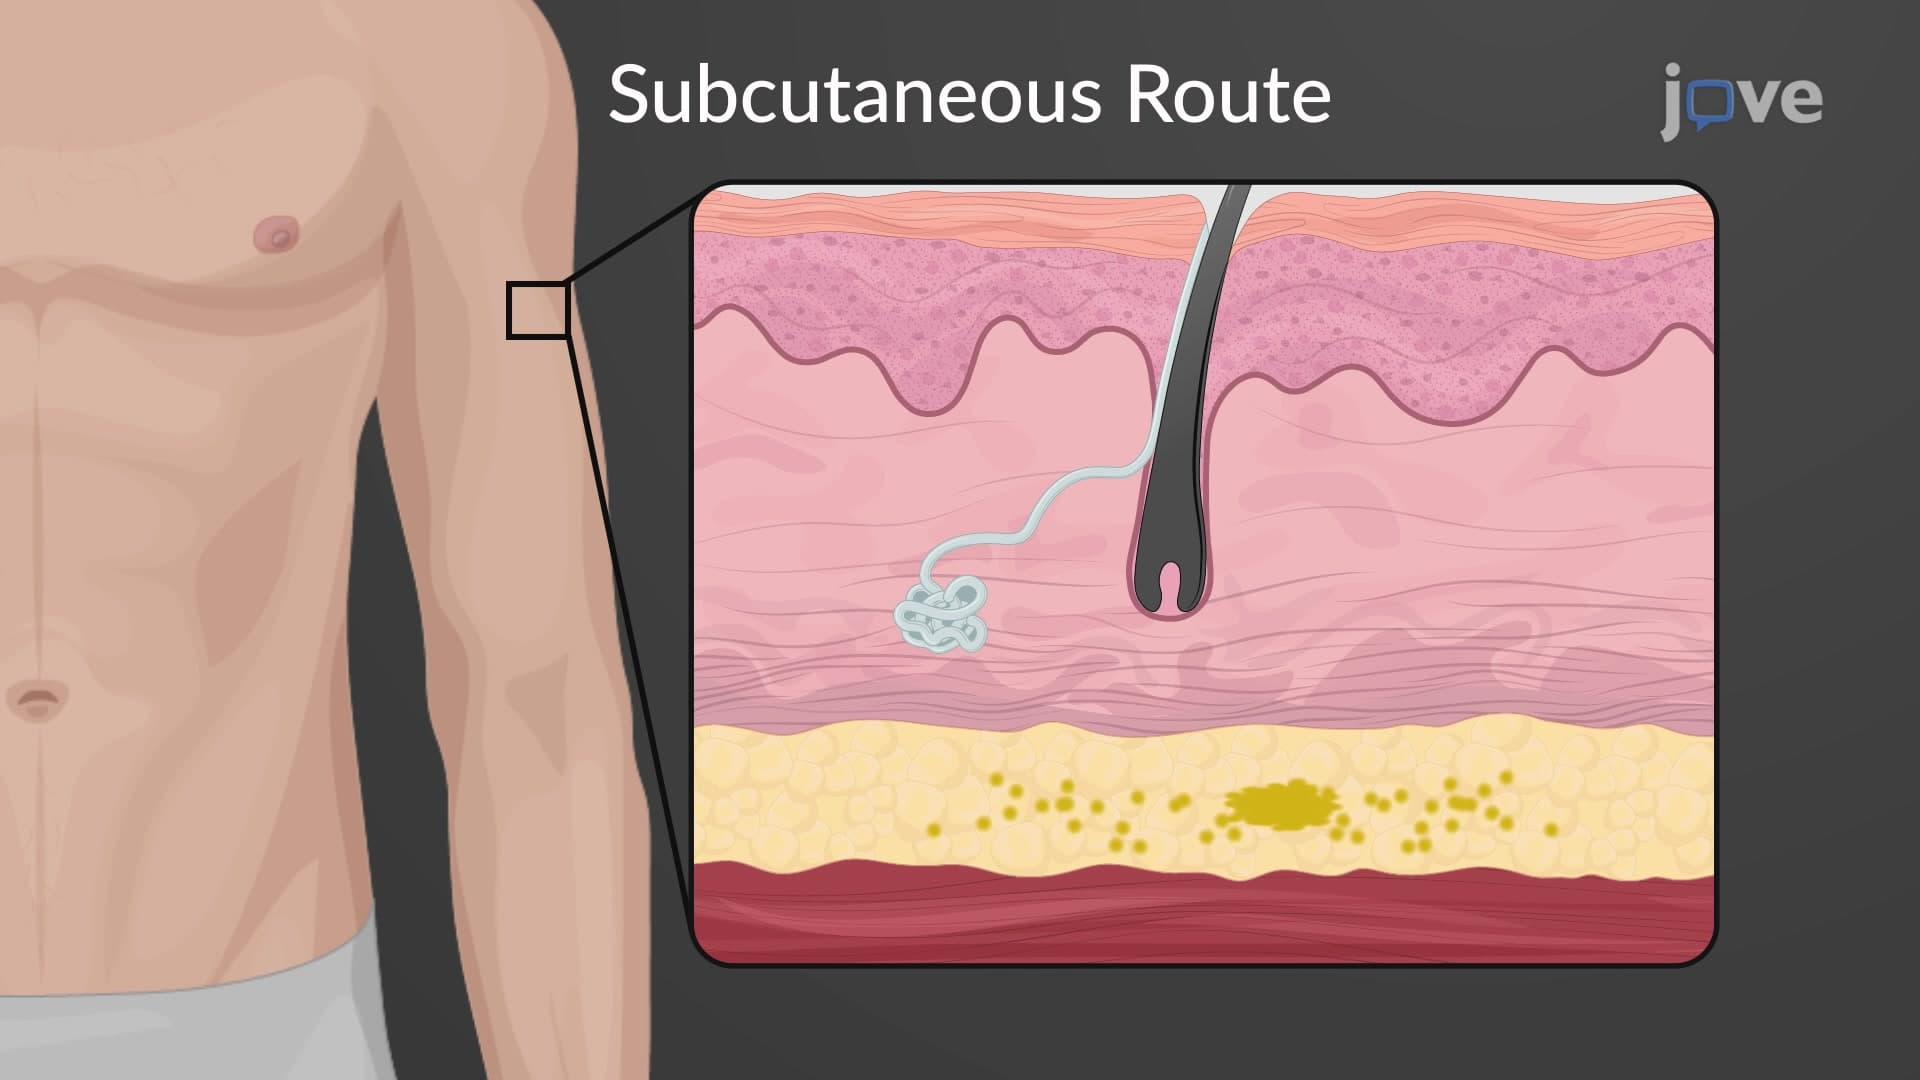
Drug Delivery: Overview
Enteral delivery involves administering drugs directly through swallowing, sublingual placement, or buccal application. Orally administered drugs predominantly navigate the...
 01:25
Routes of Drug Administration: Parenteral
The intravenous route (IV) of drug administration can be further categorized into two types. The bolus injection administers the entire dose rapidly, while an intravenous infusion slowly delivers smaller doses steadily.
The IV route is often...
 01:27
Parentral Nutrition: Centeral and Peripheral Parental Nutrition
PN can be administered through two primary routes:
1. Central Parenteral Nutrition (CPN):
CPN involves delivering a high concentration of nutrients through a large vein. This is typically achieved using a Peripherally Inserted Central Catheter (PICC) or,...
 01:18
Drug Delivery: Enteral Route