Related Experiment Video
Updated: Mar 21, 2026
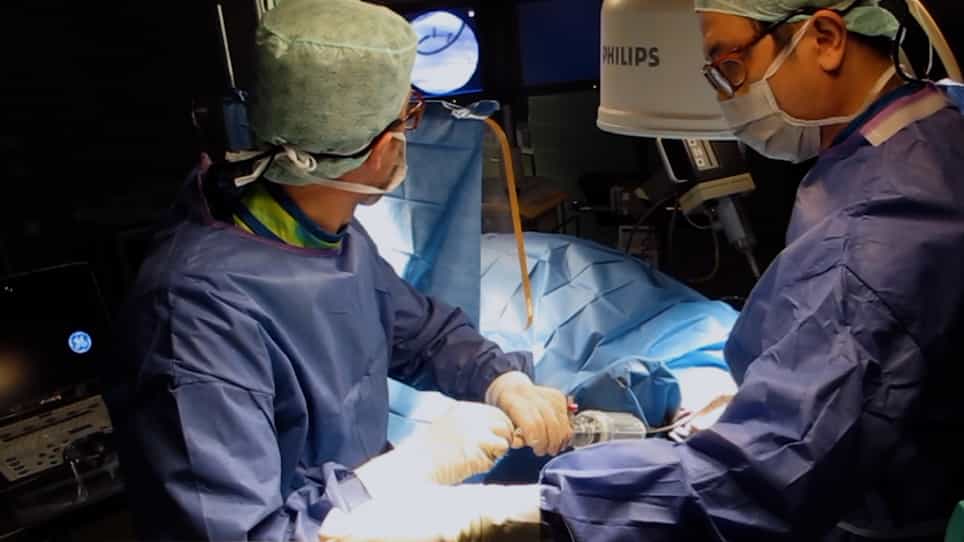
Transcatheter Pulmonary Valve Replacement from Autologous Pericardium with a Self-Expandable Nitinol Stent in an Adult Sheep Model
Published on: June 8, 2022
Prosthetic pulmonary valve and pulmonary conduit endocarditis: clinical, microbiological and echocardiographic
William R Miranda1, Heidi M Connolly2, Crystal R Bonnichsen2
1Division of Cardiovascular Diseases, Mayo Clinic, Rochester, MN, USA miranda.william@mayo.edu.

Aims:
To review clinical and microbiological findings in adults with prosthetic pulmonary valve (PPV) or right ventricle to pulmonary artery conduit (RVPAC) infective endocarditis (IE) and to assess the yield of transthoracic (TTE) and transesophageal echocardiography (TEE) as diagnostic tools.
Methods And Results:
Seventeen adults (age ≥18 years) with PPV/RVPAC who met diagnostic criteria for definite IE between 2000 and 2015 were included. Median age was 34 years and 29% were females; four patients (24%) had a previous episode of IE. IE occurred a median interval of 5.3 years after PPV/RVPAC insertion; median follow-up time was 206 days. The most common organisms were Staphylococcus aureus (29%), coagulase-negative staphylococci (24%), and streptococcal species (24%). Eleven patients (64.5%) required PPV/RVPAC replacement surgery as consequence of the IE episode. There were three deaths during follow-up; one non-operative and two post-operative. TTE was diagnostic for PPV/RVPAC IE in 10 (62%) and TEE was diagnostic in eight (57%) patients; when combined TTE/TEE were diagnostic in 15 of 17 (88%) cases. Severe PPV/RVPAC obstruction was present at the time of IE diagnosis in nine (53%) and severe regurgitation in five (29%).
Conclusion:
PPV/RVPAC IE is associated with significant morbidity, mortality and high risk of requiring operative intervention. TTE and TEE are marginal diagnostic tools when used independently; they should be used as complementary techniques in the evaluation of those patients. Severe PPV/RVPAC stenosis was more common than regurgitation in patients with IE; thus IE should be considered in patients presenting with new PPV/RVPAC obstruction.
Insights
Infective endocarditis (IE) of prosthetic pulmonary valves (PPV) or conduits (RVPAC) causes significant complications and often requires surgery. Combined transthoracic and transesophageal echocardiography improve diagnosis.
Area of Science:
- Cardiology
- Infectious Diseases
- Cardiac Surgery
Background:
- Prosthetic pulmonary valve (PPV) and right ventricle to pulmonary artery conduit (RVPAC) infective endocarditis (IE) is a serious complication.
- Understanding clinical, microbiological, and diagnostic features is crucial for patient management.
Purpose of the Study:
- To review clinical and microbiological findings of PPV/RVPAC IE in adults.
- To assess the diagnostic utility of transthoracic echocardiography (TTE) and transesophageal echocardiography (TEE).
Main Methods:
- Retrospective review of 17 adult patients with definite PPV/RVPAC IE (2000-2015).
- Analysis of clinical presentation, causative organisms, echocardiographic findings (TTE and TEE), and outcomes.
- Evaluation of diagnostic yield of TTE and TEE, individually and combined.
Main Results:
- The most common pathogens were Staphylococcus aureus, coagulase-negative staphylococci, and streptococci.
- 64.5% of patients required PPV/RVPAC replacement surgery; mortality was 17.6%.
- Combined TTE and TEE diagnosed IE in 88% of cases, while individual TTE (62%) and TEE (57%) had lower yields. Severe obstruction (53%) was more frequent than regurgitation (29%).
Conclusions:
- PPV/RVPAC IE presents with significant morbidity, mortality, and a high need for surgical intervention.
- TTE and TEE are valuable complementary diagnostic tools for PPV/RVPAC IE.
- New-onset PPV/RVPAC obstruction should raise suspicion for IE.


Related Concept Videos
 01:25
Endocarditis I: Introduction
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:18
Endocarditis III: Medical Management
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:22
Mitral Valve Prolapse II: Assessment and Management
 01:22
Mitral Stenosis I: Introduction