Related Experiment Video
Updated: Mar 21, 2026

Noninvasive Determination of Vortex Formation Time Using Transesophageal Echocardiography During Cardiac Surgery
Published on: November 28, 2018
Unexplained exertional dyspnea caused by low ventricular filling pressures: results from clinical invasive
William M Oldham1, Gregory D Lewis2, Alexander R Opotowsky3
1Pulmonary and Critical Care Medicine, Department of Medicine, Brigham and Women's Hospital, Boston, Massachusetts, USA; Heart and Vascular Center, Brigham and Women's Hospital, Boston, Massachusetts, USA; Department of Medicine, Harvard Medical School, Boston, Massachusetts, USA.

Abstract:
To determine whether low ventricular filling pressures are a clinically relevant etiology of unexplained dyspnea on exertion, a database of 619 consecutive, clinically indicated invasive cardiopulmonary exercise tests (iCPETs) was reviewed to identify patients with low maximum aerobic capacity (V̇o2max) due to inadequate peak cardiac output (Qtmax) with normal biventricular ejection fractions and without pulmonary hypertension (impaired: n = 49, V̇o2max = 53% predicted [interquartile range (IQR): 47%-64%], Qtmax = 72% predicted [62%-76%]). These were compared to patients with a normal exercise response (normal: n = 28, V̇o2max = 86% predicted [84%-97%], Qtmax = 108% predicted [97%-115%]). Before exercise, all patients received up to 2 L of intravenous normal saline to target an upright pulmonary capillary wedge pressure (PCWP) of ≥5 mmHg. Despite this treatment, biventricular filling pressures at peak exercise were lower in the impaired group than in the normal group (right atrial pressure [RAP]: 6 [IQR: 5-8] vs. 9 [7-10] mmHg, P = 0.004; PCWP: 12 [10-16] vs. 17 [14-19] mmHg, P < 0.001), associated with decreased stroke volume (SV) augmentation with exercise (+13 ± 10 [standard deviation (SD)] vs. +18 ± 10 mL/m(2), P = 0.014). A review of hemodynamic data from 23 patients with low RAP on an initial iCPET who underwent a second iCPET after saline infusion (2.0 ± 0.5 L) demonstrated that 16 of 23 patients responded with increases in Qtmax ([+24% predicted [IQR: 14%-34%]), V̇o2max (+10% predicted [7%-12%]), and maximum SV (+26% ± 17% [SD]). These data suggest that inadequate ventricular filling related to low venous pressure is a clinically relevant cause of exercise intolerance.
More Related Videos
 08:45
Echocardiographic Assessment Using Subxiphoid-Only Examination for Hypotensive Patients
Published on: April 18, 2025
 07:09
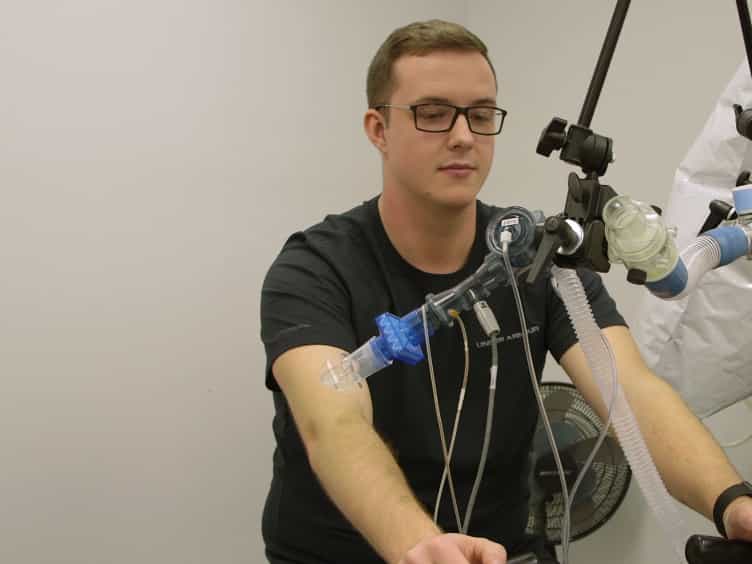
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Related Concept Videos
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:26
Heart Failure III: Clinical Manifestations
 01:29
Heart Failure II: Pathophysiology
 01:25
Hyperpnea and Hyperventilation
 01:22
Mitral Stenosis I: Introduction
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy