Related Experiment Video
Updated: Mar 21, 2026
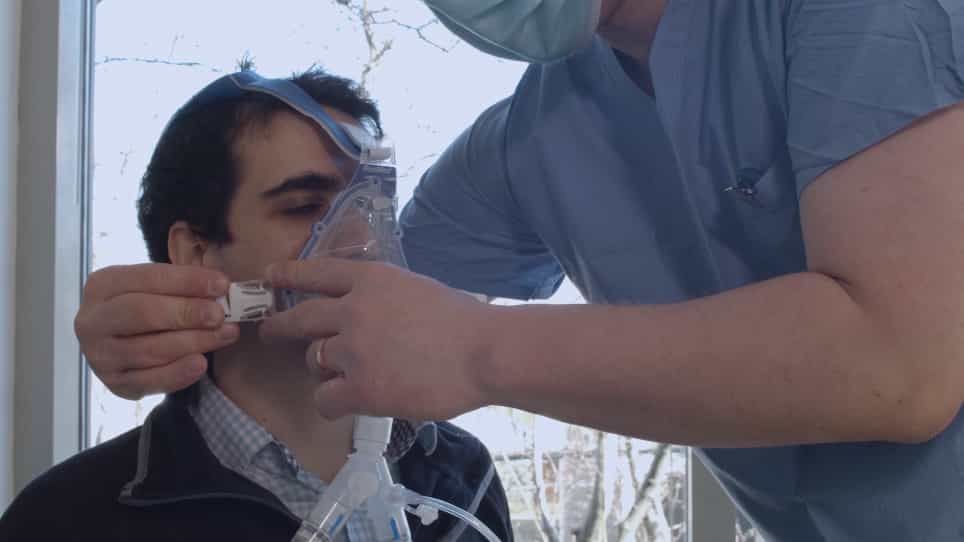

A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021
Effect of Inhaled Nitric Oxide on Outcomes in Children With Acute Lung Injury: Propensity Matched Analysis From a
Punkaj Gupta1, Troy Richardson, Matthew Hall
11Division of Pediatric Cardiology, Department of Pediatrics, University of Arkansas for Medical Sciences, Little Rock, AR.2Children's Hospital Association, Overland Park, KS.3Division of Pediatric Critical Care Medicine, Department of Pediatrics, Children's Healthcare of Atlanta, Emory University School of Medicine, Atlanta, GA.4Virtual PICU Systems, LLC, Los Angeles, CA.5Division of Critical Care Medicine, Department of Pediatrics and Anesthesiology, Children's Hospital Los Angeles, USC Keck School of Medicine, Los Angeles, CA.

Insights
Inhaled nitric oxide did not improve mortality in children with acute lung injury. This treatment was linked to increased hospital resource use and higher costs.
Area of Science:
- Pediatric Critical Care Medicine
- Respiratory Medicine
- Clinical Pharmacology
Background:
- Acute lung injury (ALI) in children presents significant challenges in critical care.
- Inhaled nitric oxide (iNO) is a therapeutic gas used in respiratory conditions.
- The efficacy of iNO in pediatric ALI remains a subject of investigation.
Purpose of the Study:
- To evaluate the impact of inhaled nitric oxide on mortality and other outcomes in pediatric patients with acute lung injury.
- To analyze the association between iNO administration and resource utilization in this patient population.
Main Methods:
- Retrospective analysis of linked data from two national pediatric databases (2009-2014).
- Inclusion of pediatric patients (<18 years) on mechanical ventilation for ALI.
- Propensity score matching to compare outcomes between patients receiving iNO (≥24 hours) and those not receiving iNO.
Main Results:
- A total of 20,106 patients were analyzed; 859 (4.3%) received iNO.
- After propensity score matching, no significant difference in mortality was observed between the iNO and no-iNO groups (22.3% vs 20.2%).
- The iNO group experienced significantly worse outcomes, including fewer ventilation-free days, longer mechanical ventilation duration, longer ICU and hospital stays, and higher hospital costs.
Conclusions:
- Inhaled nitric oxide administration in children with acute lung injury is not associated with improved survival.
- iNO use in this population correlates with increased hospital resource utilization and elevated healthcare costs.
- Further research may be needed to identify specific pediatric ALI subgroups who might benefit from iNO therapy.
Objectives:
To evaluate the effect of inhaled nitric oxide on outcomes in children with acute lung injury.
Design:
Retrospective study with a secondary data analysis of linked data from two national databases. Propensity score matching was performed to adjust for potential confounding variables between patients who received at least 24 hours of inhaled nitric oxide (inhaled nitric oxide group) and those who did not receive inhaled nitric oxide (no inhaled nitric oxide group).
Setting:
Linked data from Virtual Pediatric Systems (LLC) database and Pediatric Health Information System.
Patients:
Patients less than 18 years old receiving mechanical ventilation for acute lung injury at nine participating hospitals were included (2009-2014).
Interventions:
None.
Measurements And Main Results:
A total of 20,106 patients from nine hospitals were included. Of these, 859 patients (4.3%) received inhaled nitric oxide for at least 24 hours during their hospital stay. Prior to matching, patients in the inhaled nitric oxide group were younger, with more comorbidities, greater severity of illness scores, higher prevalence of cardiopulmonary resuscitation, and greater resource utilization. Before matching, unadjusted outcomes, including mortality, were worse in the inhaled nitric oxide group (inhaled nitric oxide vs no inhaled nitric oxide; 25.7% vs 7.9%; p < 0.001; standardized mortality ratio, 2.6 [2.3-3.1] vs 1.1 [1.0-1.2]; p < 0.001). Propensity score matching of 521 patient pairs revealed no difference in mortality in the two groups (22.3% vs 20.2%; p = 0.40; standardized mortality ratio, 2.5 [2.1-3.0] vs 2.3 [1.9-2.8]; p = 0.53). However, the other outcomes such as ventilation free days (10.1 vs 13.6 d; p < 0.001), duration of mechanical ventilation (13.8 vs 10.1 d; p < 0.001), duration of ICU and hospital stay (15.5 vs 12.2 d; p < 0.001 and 28.0 vs 24.1 d; p < 0.001), and hospital costs ($150,569 vs $102,823; p < 0.001) were significantly worse in the inhaled nitric oxide group.
Conclusions:
This large observational study demonstrated that inhaled nitric oxide administration in children with acute lung injury was not associated with improved mortality. Rather, it was associated with increased hospital utilization and hospital costs.
More Related Videos
 07:15
Preoxygenation Techniques for Tracheal Intubation in Critically Ill Adults Utilizing Oxygen Mask and Noninvasive Ventilation
Published on: December 5, 2025
 08:23
Chemiluminescence-based Assays for Detection of Nitric Oxide and its Derivatives from Autoxidation and Nitrosated Compounds
Published on: February 16, 2022
Related Concept Videos
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include: