Related Experiment Video
Updated: Mar 21, 2026


Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome ARDS
Published on: April 7, 2021
End-Expiratory Lung Volume in Patients with Acute Respiratory Distress Syndrome: A Time Course Analysis
Armin Kalenka1,2, Felix Gruner3, Christel Weiß4
1Department of Anaesthesiology and Intensive Care Medicine, Hospital Bergstraße, Heppenheim, Germany. armin.kalenka@kkh-bergstrasse.de.

Purpose:
Lung injury can be caused by ventilation and non-physiological lung stress (transpulmonary pressure) and strain [inflated volume over functional residual capacity ratio (FRC)]. FRC is severely decreased in patients with acute respiratory distress syndrome (ARDS). End-expiratory lung volume (EELV) is FRC plus lung volume increased by the applied positive end-expiratory pressure (PEEP). Measurement using the modified nitrogen multiple breath washout technique may help titrating PEEP during ARDS and allow determining dynamic lung strain (tidal volume over EELV) in patients ventilated with PEEP. In this observational study, we measured EELV for up to seven consecutive days in patients with ARDS at different PEEP levels.
Results:
Thirty sedated patients with ARDS (10 mild, 14 moderate, 6 severe) underwent decremental PEEP testing (20, 15, 10, 5 cm H2O) for up to 7 days after inclusion. At all PEEP levels examined, over a period of 7 days the measured absolute EELVs showed no significant change over time [PEEP 20 cm H2O 2464 ml at day 1 vs. 2144 ml at day 7 (p = 0.78), PEEP 15 cm H2O 2226 ml vs. 1990 ml (p = 0.36), PEEP 10 1835 ml vs. 1858 ml (p = 0.76) and PEEP 5 cm H2O 1487 ml vs. 1612 ml (p = 0.37)]. In relation to the predicted body weight (pbw), no significant change in EELV/kg pbw over time could be detected either at any PEEP level or over time [PEEP 20 36 ml/kg pbw at day 1 vs. 33 ml/kg pbw at day 7 (p = 0.66); PEEP 15 33 vs. 29 ml/kg pbw (p = 0.32); PEEP 10 27 vs. 27 ml/kg pbw (p = 0.70) and PEEP 5 22 vs. 24 ml/kg pbw (p = 0.70)]. Oxygenation significantly improved over time from PaO2/FiO2 of 169 mmHg at day 1 to 199 mmHg at day 7 (p < 0.01).
Conclusions:
EELV did not change significantly for up to 7 days in patients with ARDS. By contrast, PaO2/FiO2 improved significantly. Bedside measurement of EELV may be a novel approach to individualise lung-protective ventilation on the basis of calculation of dynamic strain as the ratio of VT to EELV.


Related Concept Videos
 01:15
Respiratory Volumes
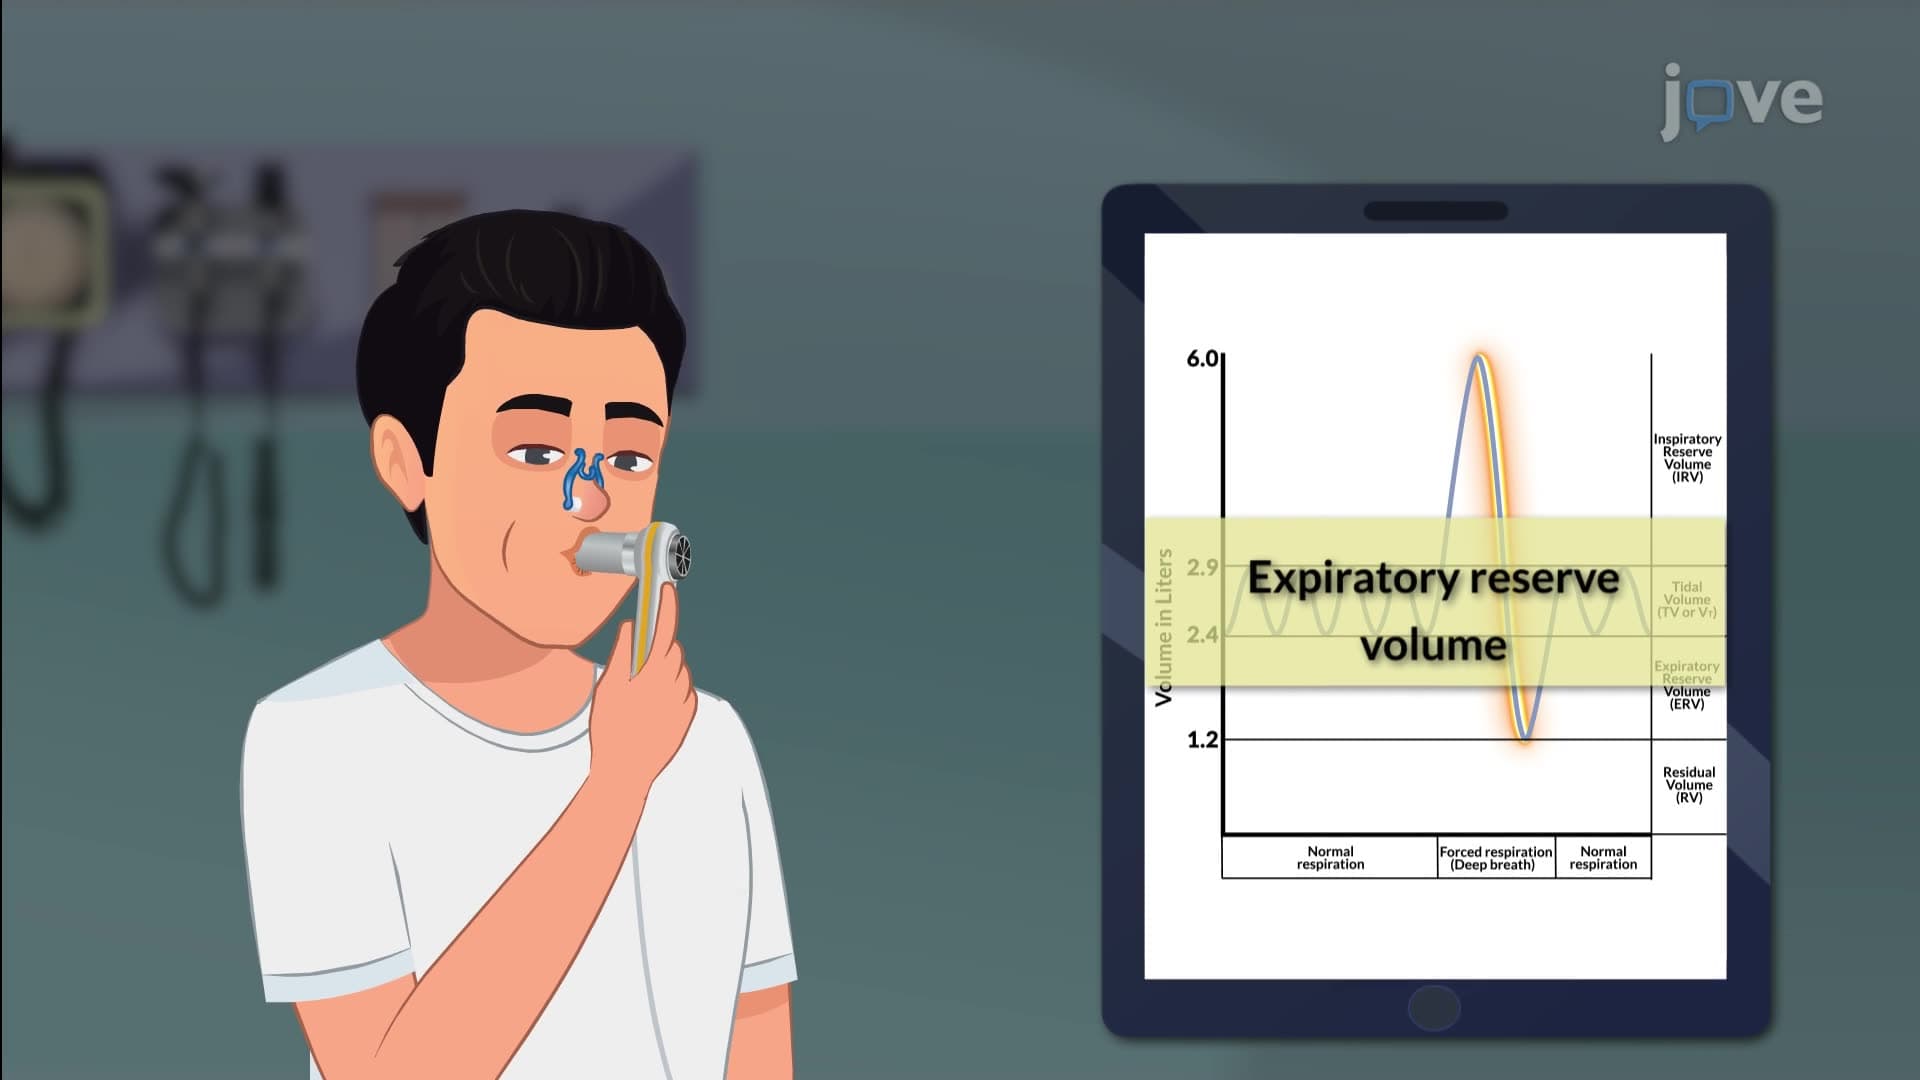
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:23
Acute Respiratory Failure-IV
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:22
Respiratory Volumes and Capacities
 01:26
Respiratory Volumes and Capacities I
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...