
Association of Early Stress Testing with Outcomes for Emergency Department Evaluation of Suspected Acute Coronary
Benjamin C Sun1, Amber Laurie, Rongwei Fu
1From the *Department of Emergency Medicine, †Division of Cardiovascular Medicine, Oregon Health and Science University, Portland, OR; ‡Department of Emergency Medicine, University of Cincinnati, Cincinnati, OH; §Department of Emergency Medicine, University of Texas Southwestern, Dallas, TX; ¶Department of Emergency Medicine, Wake Forest Baptist Medical Center, Winston-Salem, NC; ‖Department of Emergency Medicine, Thomas Jefferson University, Philadelphia, PA; **Department of Emergency Medicine, University of California Davis Medical Center, Sacramento, CA; ††Department of Emergency Medicine, Baylor College of Medicine, Houston, TX; and ‡‡Department of Emergency Medicine, Singapore General Hospital, Singapore.

Background:
Professional society guidelines suggest early stress testing (within 72 hours) after an emergency department (ED) evaluation for suspected acute coronary syndrome (ACS). However, there is increasing concern that current practice results in over-testing without evidence of benefit. We test the hypothesis that early stress testing improves outcomes.
Methods:
We analyzed prospectively collected data from 9 EDs on patients with suspected ACS, 1999-2001. We excluded patients with an ED diagnosis of ACS. The primary outcome was 30-day major adverse cardiac events (MACEs), including all-cause death, acute myocardial infarction, and revascularization. We used the HEART score to determine pretest ACS risk (low, intermediate, and high). To mitigate potential confounding, patients with and without early stress testing were matched within pretest risk strata in a 1:2 ratio using propensity scores.
Results:
Of 7127 potentially eligible patients, 895 (13%) received early stress testing. The analytic cohort included 895 patients with early stress testing matched to 1790 without early stress testing. The overall 30-day MACE rate in both the source and analytic population was 3%. There were no baseline imbalances after propensity score matching (P > 0.1 for more than 30 variables). There was no association between early stress testing and 30-day MACE [odds ratio, 1.0; 95% confidence interval (CI), 0.6-1.7]. There was no effect modification by pretest risk (low: odds ratio, 1.0; 95% CI, 0.2-3.7; intermediate: 1.2; 95% CI, 0.6-2.6; high: 0.4; 95% CI, 0.1-1.6).
Conclusions:
Early stress testing is not associated with reduced MACE in patients evaluated for suspected ACS. Early stress testing may have limited value in populations with low MACE rate.
More Related Videos
 08:25
Polar Histogram Visualization of Acute Stress Disorder Scale Scores for Comprehensive Clinical Assessment
Published on: December 6, 2024
 06:16
Signal Acquisition, Score Interpretation, and Economics of a Non-Invasive Point-of-Care Test for Coronary Artery Disease
Published on: August 9, 2024
Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:26
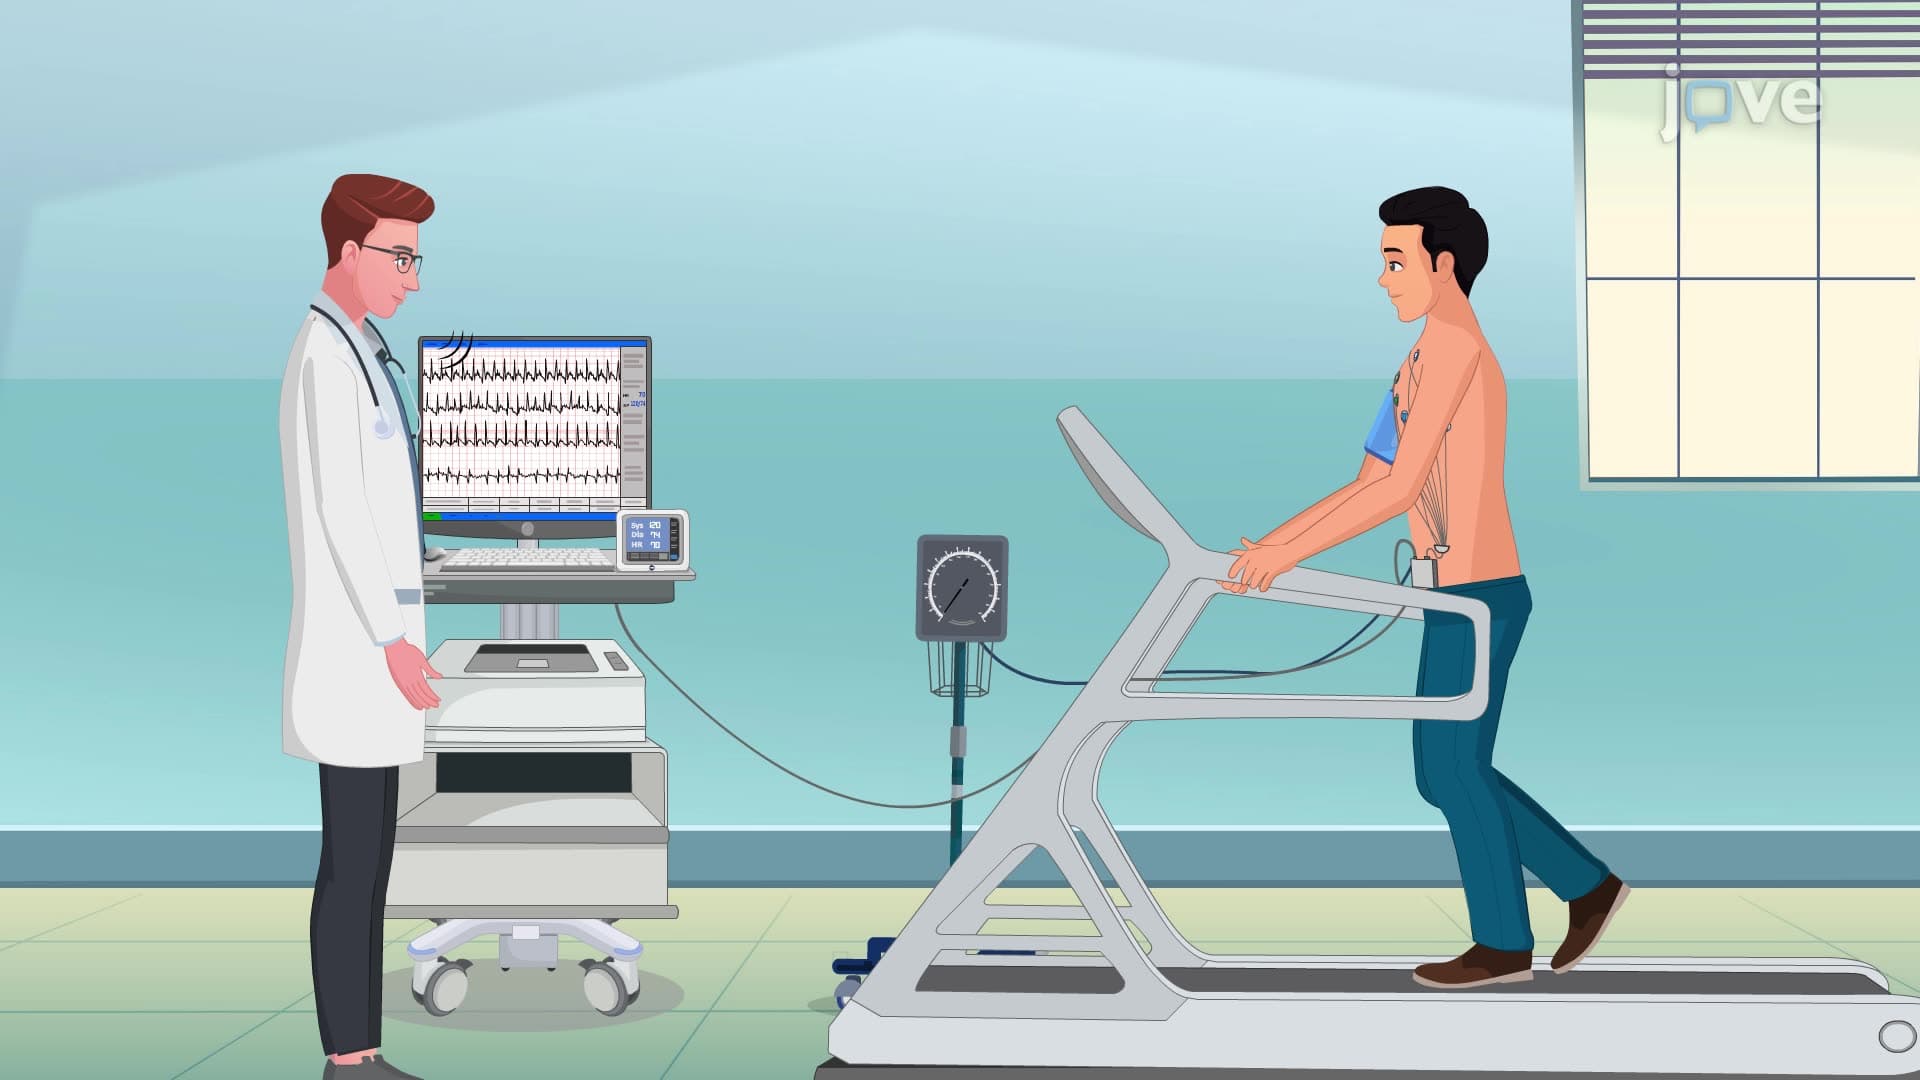
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:30
Acute Coronary Syndrome I: Introduction
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:26
Acute Coronary Syndrome V: Nursing Management