Related Experiment Video
Updated: Mar 21, 2026
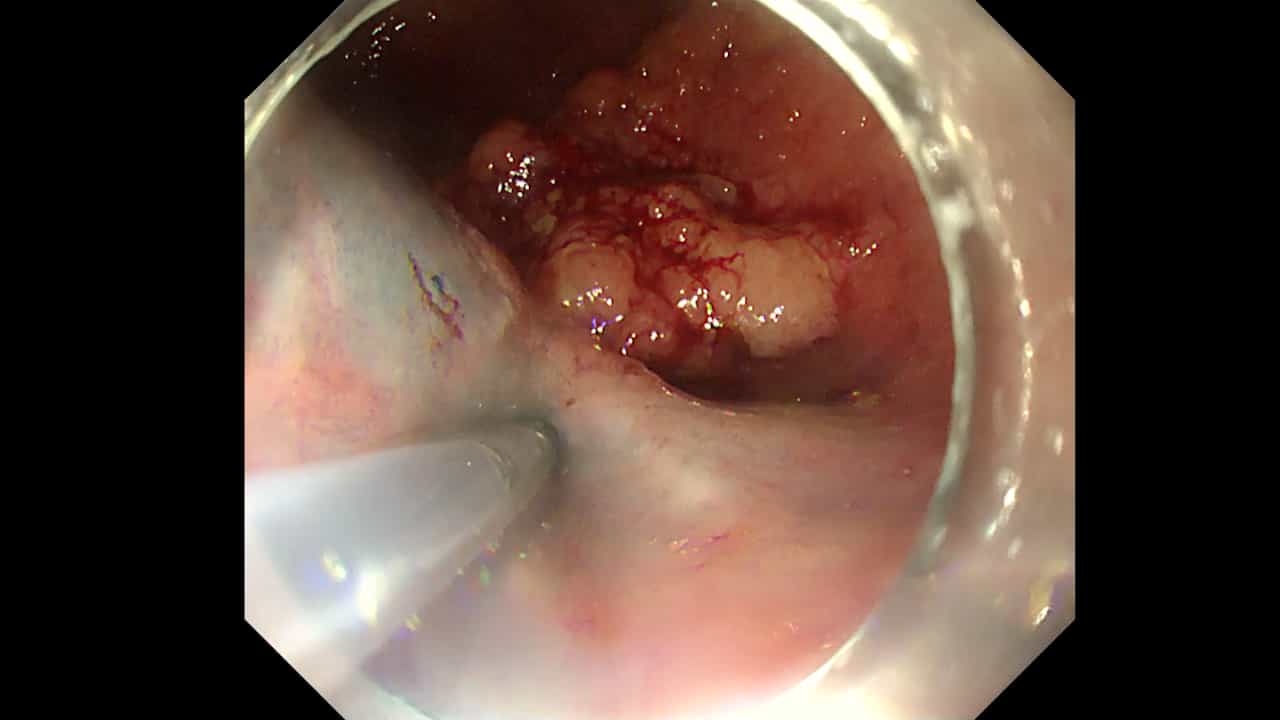

The Pocket-Creation Procedure of Endoscopic Submucosal Dissection for Large Rectal Laterally Spreading Tumors
Published on: February 13, 2026
Extended endoscopic mucosal resection does not reduce recurrence compared with standard endoscopic mucosal
Farzan F Bahin1, Maria Pellise2, Stephen J Williams2
1Department of Gastroenterology and Hepatology, Westmead Hospital, Westmead, NSW, Australia; Faculty of Medicine, University of Sydney, Sydney, NSW, Australia.

Background And Aims:
Effective interventions to prevent residual and/or recurrent adenoma (RRA) after EMR of large sessile and laterally spreading colorectal lesions (LSL) are yet to be determined. RRA may occur due to inconspicuous adenoma at the EMR margin. We aimed to determine the efficacy and safety of extended EMR (X-EMR) compared with standard EMR (S-EMR).
Methods:
A single-center post hoc analysis of LSL ≥20 mm referred for treatment was performed. S-EMR was the standard sequential inject and resect method including a 1-mm to 2-mm margin of normal mucosa around the lesion. With X-EMR, at least a 5-mm margin of normal mucosa was excised. Patient and lesion characteristics and procedural outcomes were recorded. The primary endpoint was RRA at first surveillance colonoscopy at 4 months.
Results:
Between January 2009 and May 2011, 471 lesions (mean size, 37.9 mm) in 424 patients were resected by S-EMR, and between January 2012 and December 2013, 448 lesions (mean size, 39.1 mm) in 396 patients were resected by X-EMR. Resection was successful in 92.3% and 92.6% of referred lesions in the S-EMR and X-EMR groups, respectively (P = .978). X-EMR was independently associated with a higher risk of intraprocedural bleeding (IPB) (odds ratio, 3.1; 95% confidence interval [CI], 2.0-5.0; P < .001) but not other adverse events. RRA was present in 39 of 333 patients (11.7%) and 30 of 296 patients (10.1%) in the S-EMR and X-EMR groups, respectively (P = .15). X-EMR was not related to recurrence (hazard ratio, 0.8; 95% CI, 0.5-1.3; P = .399).
Conclusions:
X-EMR does not reduce RRA and increases the risk of IPB compared with S-EMR. Alternative methods for the prevention of RRA are required.
More Related Videos
 05:16
Laparoscopy-endoscopy Cooperative Surgery for the Treatment of Gastric Gastrointestinal Stromal Tumors
Published on: February 19, 2022
 12:45
Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
