Related Experiment Video
Updated: Mar 20, 2026
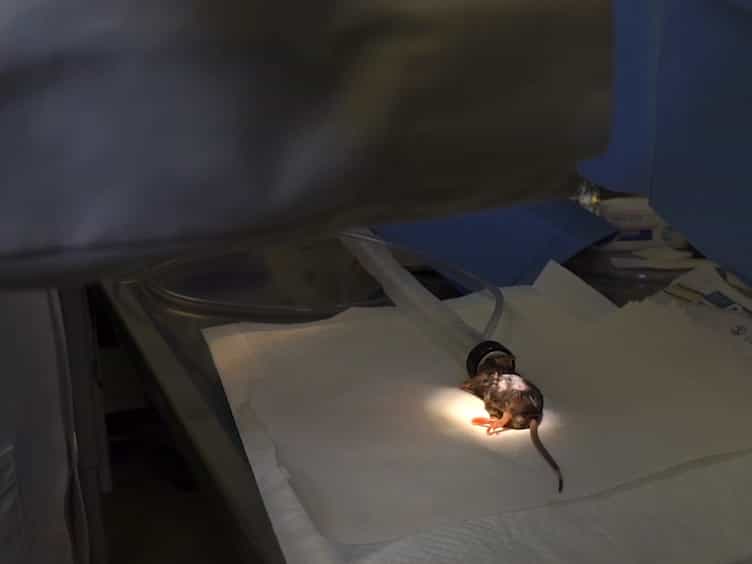
A Mouse 5/6th Nephrectomy Model That Induces Experimental Uremic Cardiomyopathy
Published on: November 7, 2017
The role of fibroblast growth factor 23 and Klotho in uremic cardiomyopathy
Alexander Grabner1, Christian Faul
1aKatz Family Drug Discovery Center and Division of Nephrology and Hypertension, Department of Medicine bDepartment of Cell Biology and Anatomy, University of Miami Leonard M. Miller School of Medicine, Miami, Florida, USA.

Insights
Fibroblast growth factor 23 (FGF23) directly causes cardiac hypertrophy in chronic kidney disease (CKD). Soluble Klotho may protect the heart, and their imbalance contributes to uremic cardiomyopathy.
Area of Science:
- Nephrology
- Cardiology
- Endocrinology
Background:
- Chronic kidney disease (CKD) is linked to cardiac hypertrophy through various systemic factors like hypertension and inflammation.
- Phosphate metabolism disturbances are emerging as key nonclassical risk factors for cardiovascular mortality in CKD patients.
- Altered levels and activity of phosphate regulators contribute to cardiac hypertrophy as kidney function declines.
Purpose of the Study:
- To review the direct and indirect effects of fibroblast growth factor 23 (FGF23) and soluble Klotho on cardiac remodeling in CKD.
- To explore the novel pathomechanisms of cardiac hypertrophy involving FGF23 and Klotho in CKD.
- To discuss the crosstalk between FGF23 and Klotho in regulating cardiac hypertrophy.
Main Methods:
- Review of recent findings on FGF23 and Klotho in CKD-related cardiac remodeling.
- Analysis of studies investigating the direct cardiac effects of FGF23 and Klotho.
- Examination of the interplay between FGF23, Klotho, and cardiac hypertrophy.
Main Results:
- FGF23 directly induces cardiac hypertrophy in myocytes via FGF receptor 4, independent of blood pressure.
- Soluble Klotho may offer direct myocardial protection against CKD-associated stress, including uremic toxins and FGF23.
- Elevated FGF23 and reduced soluble Klotho synergistically promote uremic cardiomyopathy.
Conclusions:
- FGF23 and Klotho represent a novel pathway contributing to cardiac hypertrophy in CKD.
- The balance between FGF23 and Klotho is critical for preventing uremic cardiomyopathy.
- Targeting the FGF23-Klotho axis may offer therapeutic strategies for cardiovascular complications in CKD.
Purpose Of Review:
In chronic kidney disease (CKD), multiple factors contribute to the development of cardiac hypertrophy by directly targeting the heart or indirectly by inducing systemic changes such as hypertension, anemia, and inflammation. Furthermore, disturbances in phosphate metabolism have been identified as nonclassical risk factors for cardiovascular mortality in these patients. With declining kidney function, the physiologic regulators of phosphate homeostasis undergo changes in their activity as well as their circulating levels, thus potentially contributing to cardiac hypertrophy once they are out of balance. Recently, two of these phosphate regulators, fibroblast growth factor 23 (FGF23) and Klotho, have been shown to affect cardiac remodeling, thereby unveiling a novel pathomechanism of cardiac hypertrophy in CKD. Here we discuss the potential direct versus indirect effects of FGF23 and the soluble form of Klotho on the heart, and their crosstalk in the regulation of cardiac hypertrophy.
Recent Findings:
In models of CKD, FGF23 can directly target cardiac myocytes via FGF receptor 4 and induce cardiac hypertrophy in a blood pressure-independent manner. Soluble Klotho may directly target the heart via an unknown receptor thereby protecting the myocardium from pathologic stress stimuli that are associated with CKD, such as uremic toxins or FGF23.
Summary:
Elevated serum levels of FGF23 and reduced serum levels of soluble Klotho contribute to uremic cardiomyopathy in a synergistic manner.
More Related Videos

Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:28
Role of Hematopoietic Growth Factors
Thrombopoietin (TPO), mainly released by the liver,...