[Injury of upper cervical spine]
Related Experiment Video
Updated: Mar 20, 2026
A Contusive Model of Unilateral Cervical Spinal Cord Injury Using the Infinite Horizon Impactor
Published on: July 24, 2012

Insights
Upper cervical spine injuries are common and often fatal. Early diagnosis and appropriate treatment, whether conservative or surgical, are crucial for successful outcomes in these complex cases.
Area of Science:
- Orthopedics
- Traumatology
- Neurosurgery
Context:
- Upper cervical spine injuries constitute one-third of all cervical spine injuries, with a significant mortality rate.
- Etiology varies by age, with high-energy trauma in younger individuals and falls in osteoporotic elderly patients.
- Mechanisms include axial force, hyperflexion, hyperextension, rotation, and combined forces.
Purpose:
- To review the spectrum of upper cervical spine injuries, including fractures and dislocations.
- To highlight diagnostic modalities such as X-ray, CT, and MRI.
- To discuss classification, clinical presentation, and therapeutic strategies.
Summary:
- Injuries encompass occipital condyle fractures, atlantooccipital dislocation (AOD), atlas (C1) fractures, and atlantoaxial dislocation (AAD) or C2 fractures.
- Clinical symptoms range from neck pain and restricted motion to neurological deficits including quadriplegia.
- Diagnostic imaging is essential, with CT and MRI often required for definitive assessment, especially for ligamentous injuries.
Impact:
- Accurate and timely diagnosis is paramount for effective management.
- Treatment options range from conservative management for stable fractures to surgical intervention (osteosynthesis, stabilization, fusion) for unstable injuries.
- Successful outcomes depend on prompt diagnosis and tailored treatment strategies for complex upper cervical spine trauma.
Abstract:
Injuries of the upper cervical spine represent 1/3 of all cervical spine injuries and approximately 40 % result by the death. Every level of the cervical spine can be injured - fractures of condyles of the occipital bone (CO), atlantooccipital dislocation (AOD), fractures of the Atlas (C1), atlantoaxial dislocation (AAD) and fractures of the axis (C2). Most of cases in younger patients are caused by high-energy trauma, while by elderly people, because of the osteoporosis, is needed much less energy and even simple falls can cause the injury of the cervical spine. That´s why the etiology of injuries can be different. In younger patients are caused mainly by car accidents, motorcycle and bicycle accidents and pedestrian crashes by car and in elderly populations are the main reason falls. The mechanism of the injury is axial force, hyperflexion, hyperextension, latero-flexion, rotation and combination of all. The basic diagnostic examination is X ray in AP, lateral and transoral projection. But in the most of cases is CT examination necessary and in the suspicion of the ligamentous injury and neurological deterioration must be MRI examination added. Every injury of the upper cervical spine has its own classification. Clinical symptoms can vary from the neck pain, restricted range of motion, antalgic position of the head, injury of the cranial nerves and different neurologic symptoms from the irritation of nerves to quadriplegia. A large percentage of deaths is at the time of the injury. Therapy is divided to conservative treatment, which is indicated in bone injuries with minimal dislocation. In more severe cases, with the dislocation and ligamentous injury, when is high chance of the instability, is indicated the surgical treatment. We can use anterior or posterior approach, make the osteosynthesis, stabilisation and fusion of the spine. Complex fractures and combination of different types of injuries are often present in this part of the spine. Correct and early diagnosis with the best treatment option is necessary for successful result of the cervical spine injuries.
Related Concept Videos
 01:26
Arteries of the Head and Neck
The internal carotid arteries supply blood to the anterior portion of the cerebrum. They enter the...
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...
 01:19
Muscles that Move the Head
The bilateral sternocleidomastoid, or SCM, and the suprahyoid and infrahyoid muscles are significant head flexors. The SCM muscles originate at the sternum and clavicle and attach to the mastoid process of the temporal bone. The SCM contracts bilaterally to bend the head forward, whereas...
 01:16
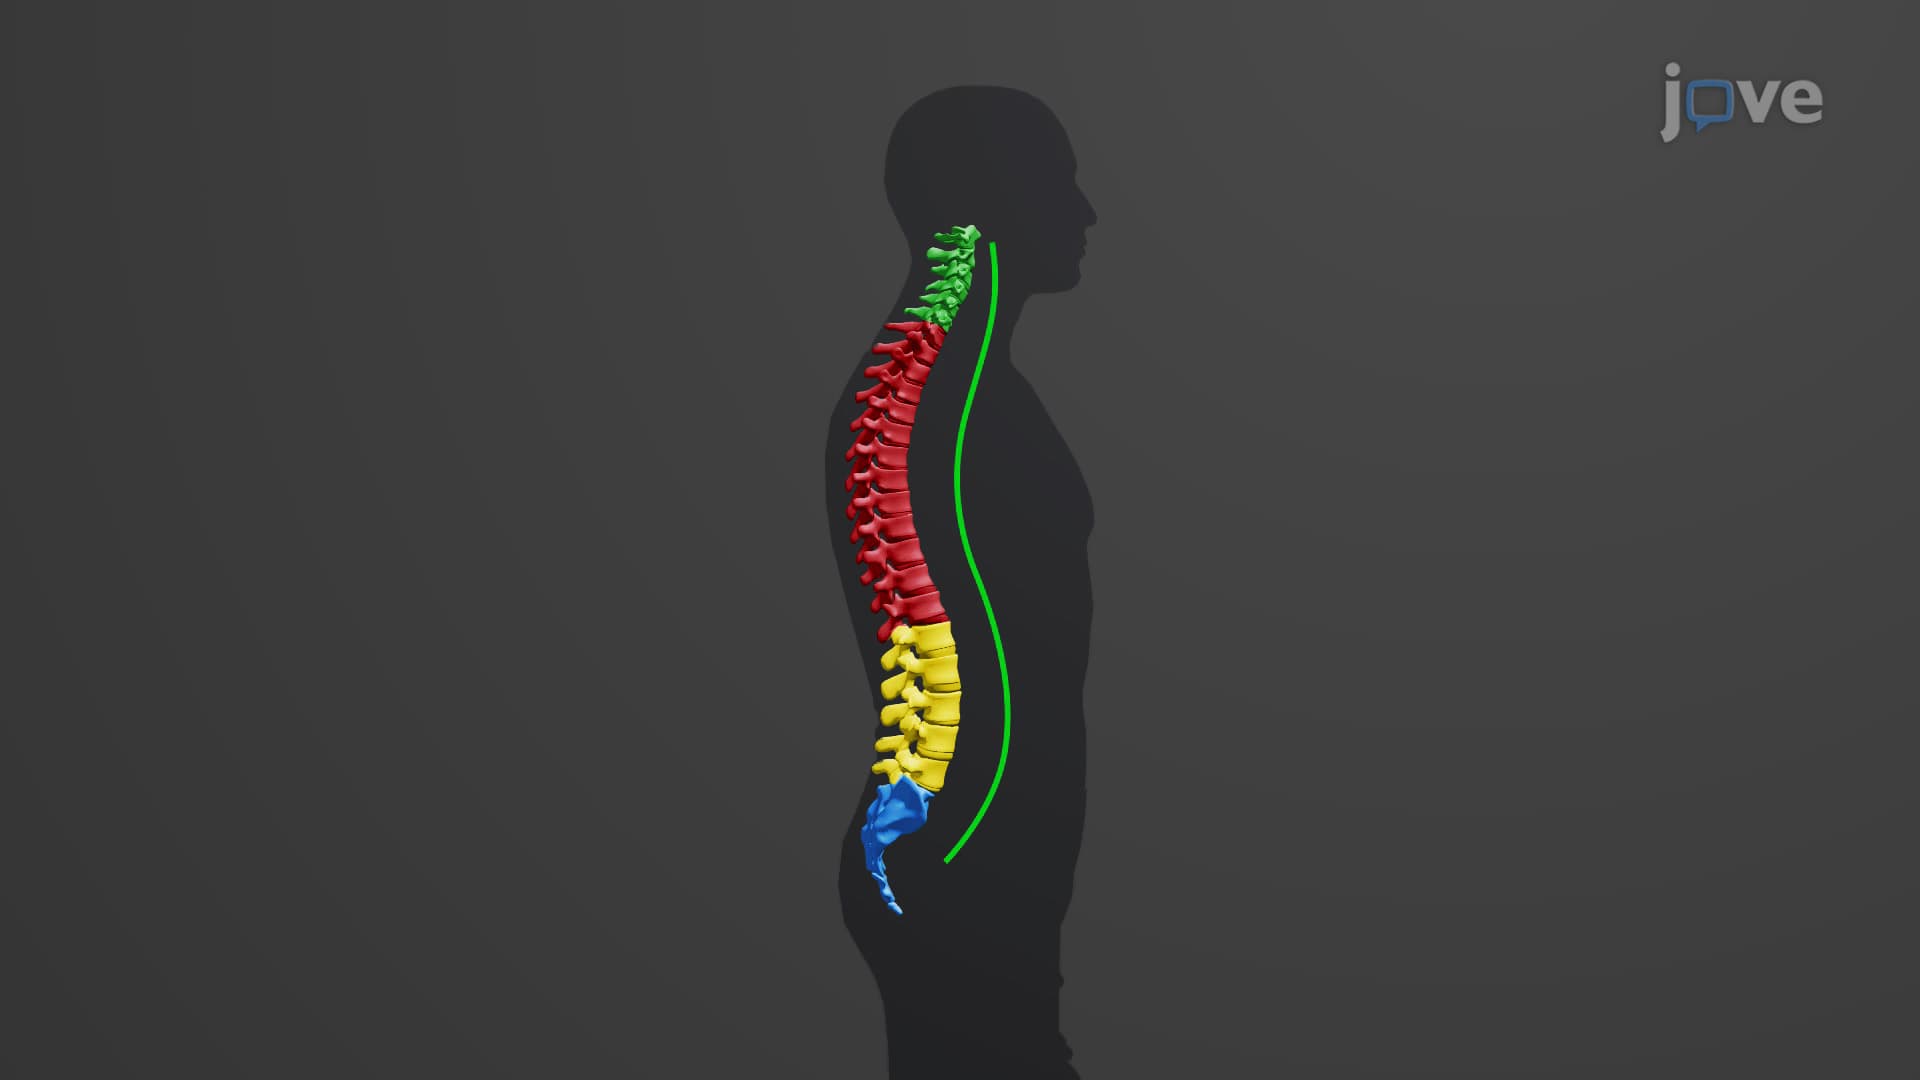
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:28
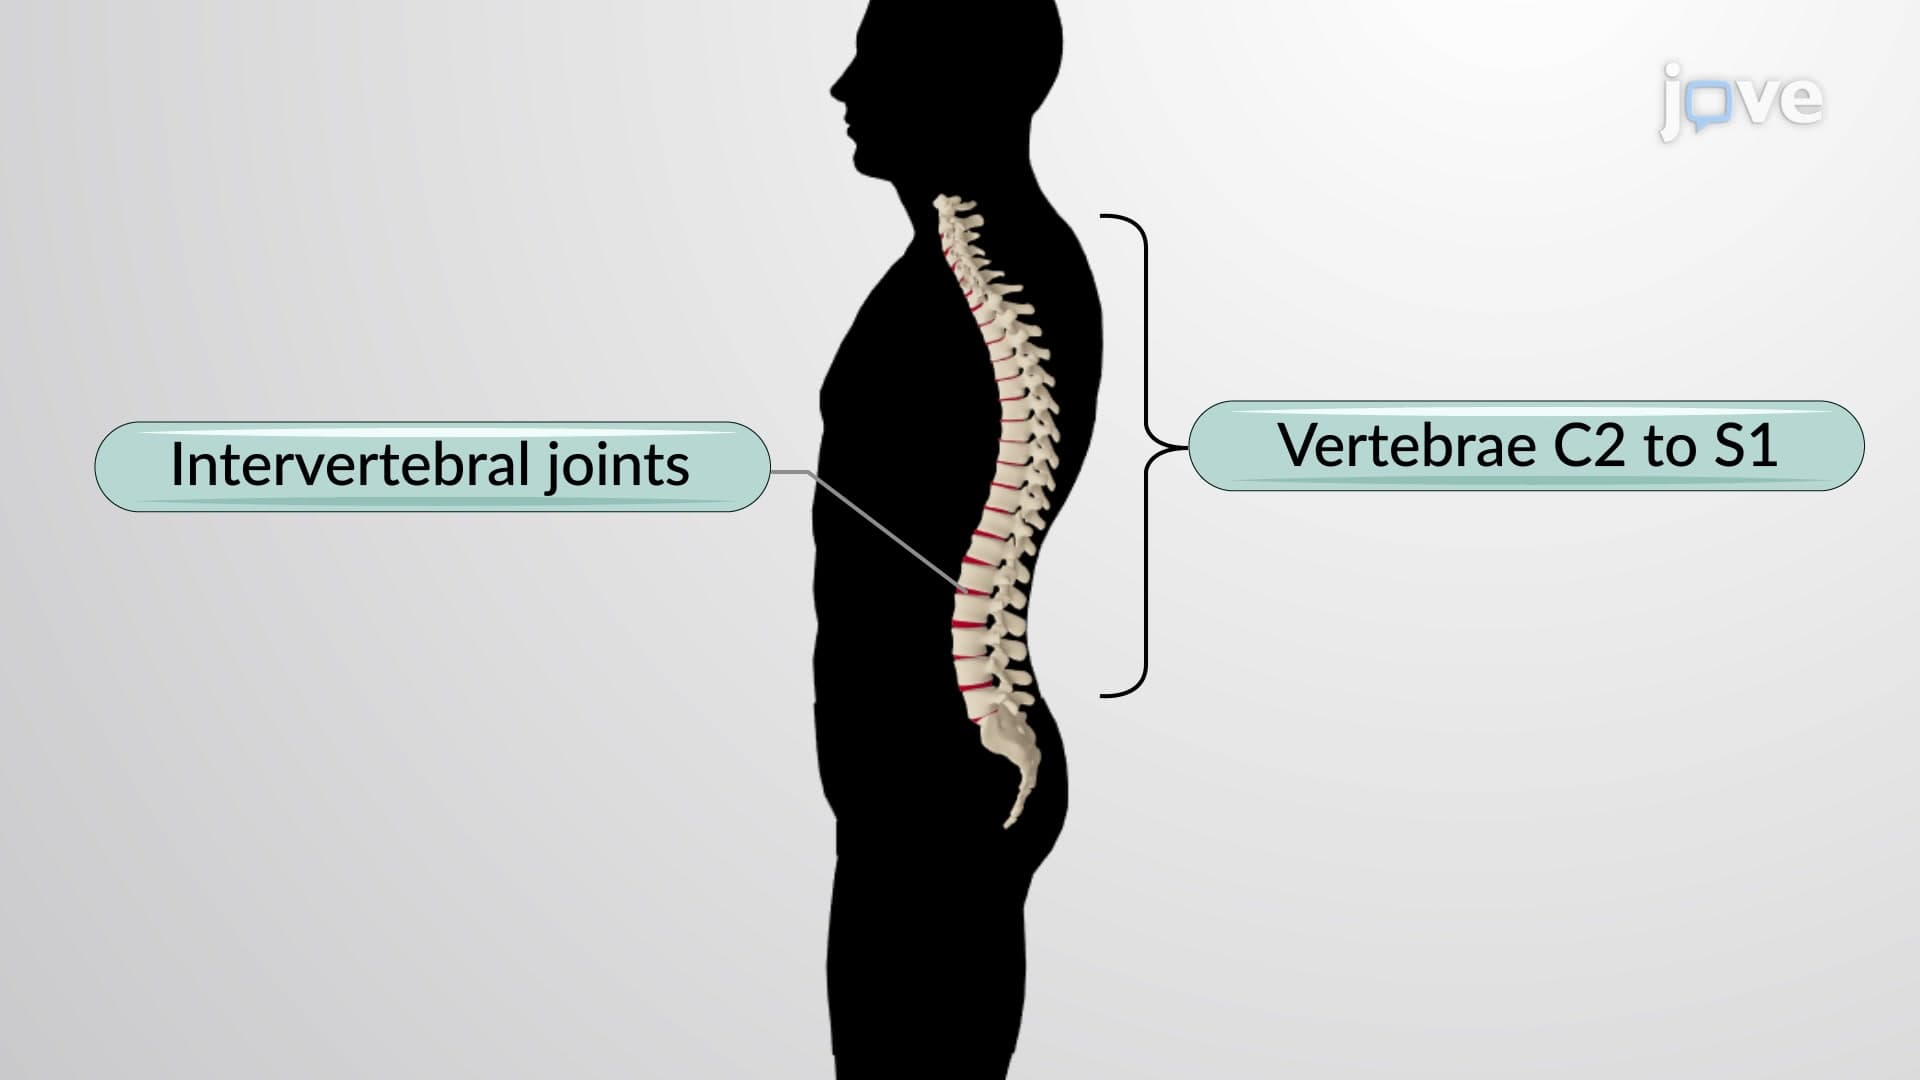
Articulations of the Vertebral Column
 01:15
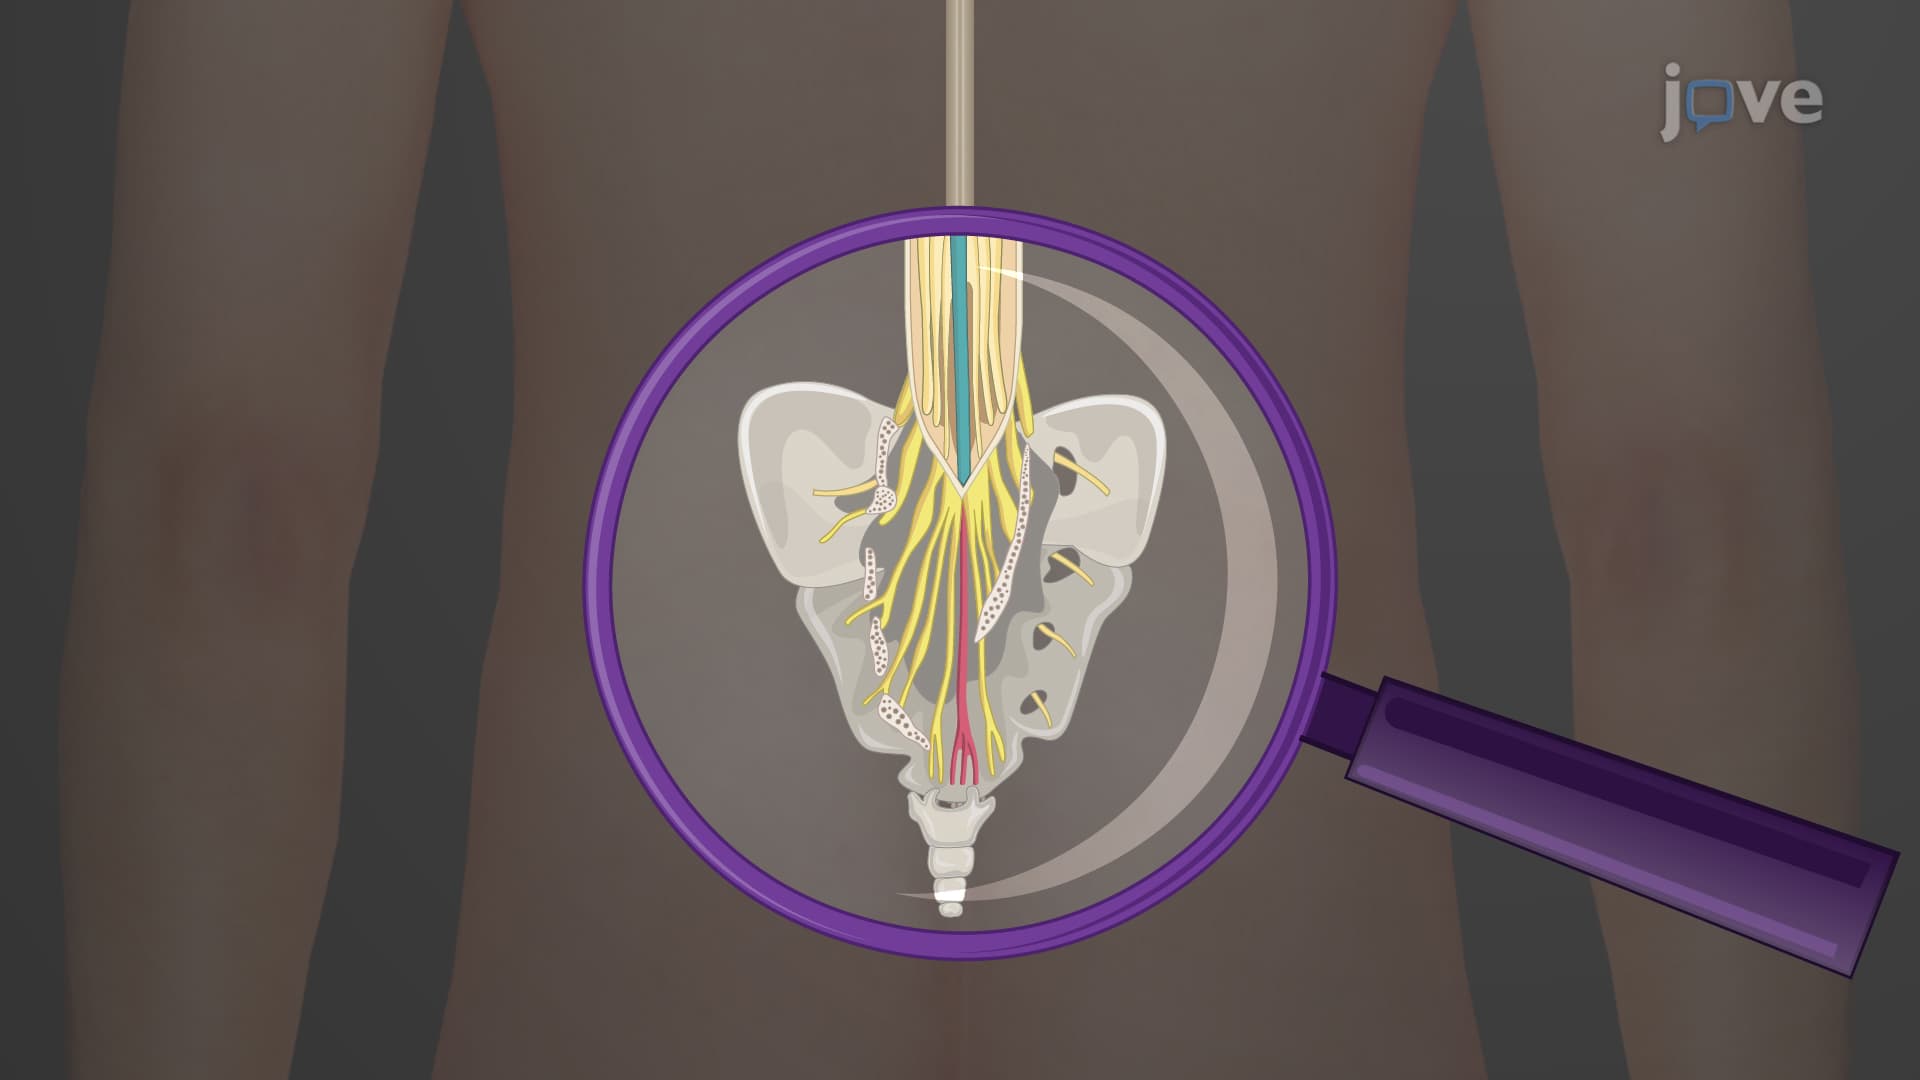
Spinal Cord: Gross Anatomy