Related Experiment Video
Updated: Mar 20, 2026


Early Detection of Drug-Induced Renal Hemodynamic Dysfunction Using Sonographic Technology in Rats
Published on: March 11, 2016
A pharmacokinetic/pharmacodynamic model capturing the time course of torasemide-induced diuresis in the dog
A Paulin1, M Schneider2, F Dron2
1Global Drug Development Division, Vétoquinol S.A., Lure, France. angelique.paulin@vetoquinol.com.

Abstract:
A pharmacokinetic/pharmacodynamic modelling approach was used to determine a dosage regimen which maximizes diuretic efficiency of torasemide in dogs. Kinetic profiles of plasma concentration, torasemide excretion rate in urine (TERU) and diuresis were investigated in 10 dogs after single oral administrations at 3 dose levels, 0.2, 0.8 and 1.6 mg/kg, and an intravenous injection of 0.2 mg/kg. Endogenous regulation was evidenced by a proteresis loop between TERU and diuresis. To describe the diuresis-time profile, TERU served as input into a turnover model with inhibition of loss of response, extended by a moderator acting on both loss and production of response. Estimated maximum inhibition of loss of response, Imax , was 0.984 showing that torasemide is an efficacious diuretic able to suppress almost total water reabsorption. A TERU50, value producing half of Imax , of 1.45 μg/kg/h was estimated from the model. Pharmacokinetic and pharmacodynamic parameters were used to simulate the torasemide dose-effect relationship after oral administration. Model predictions were in good agreement with diuresis measured in a validation study conducted in 10 dogs, which were administered oral doses of 0.15, 0.4, 0.75, 1.5 and 4.5 mg/kg for 5 days. Finally, oral dose associated with the highest daily diuretic efficiency was predicted to be 0.1 mg/kg.
More Related Videos


Related Concept Videos
 01:29
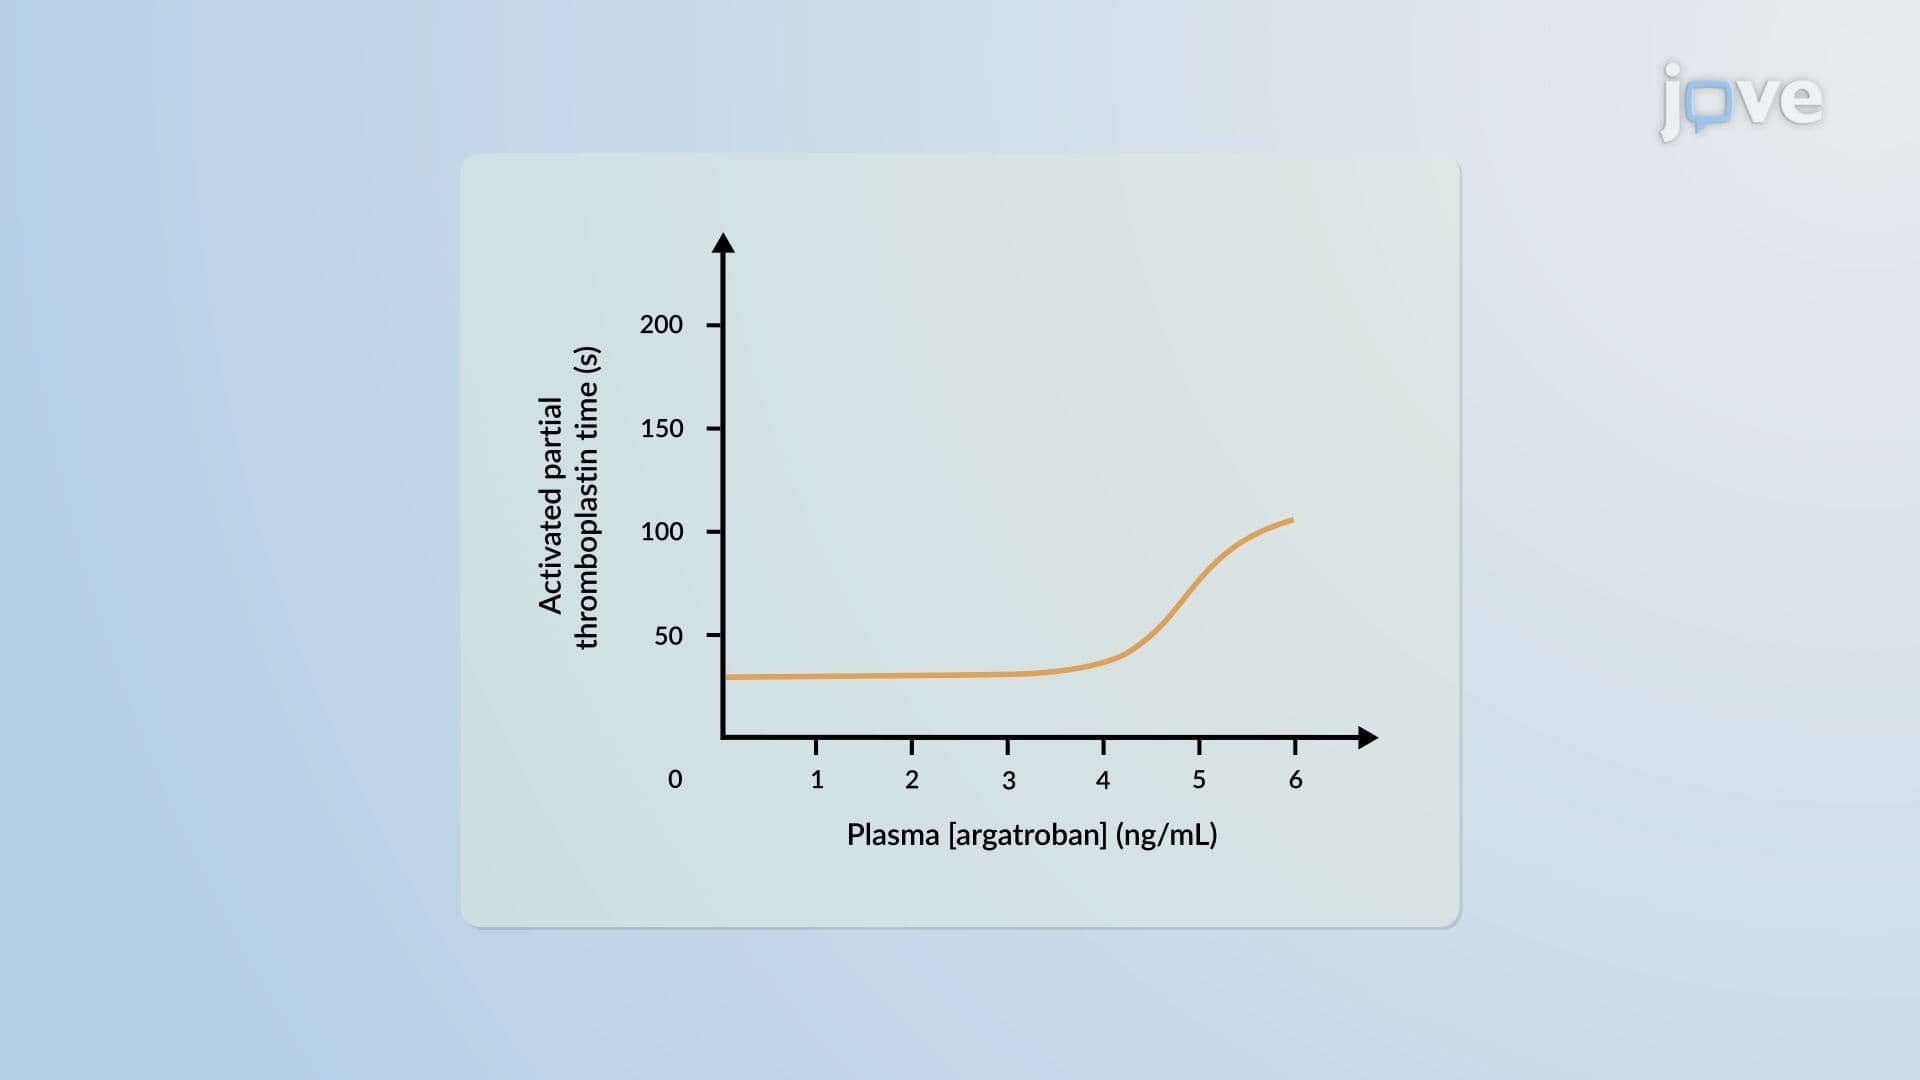
Pharmacodynamic Models: Direct Effect Model and Indirect Response Model
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions
 01:27
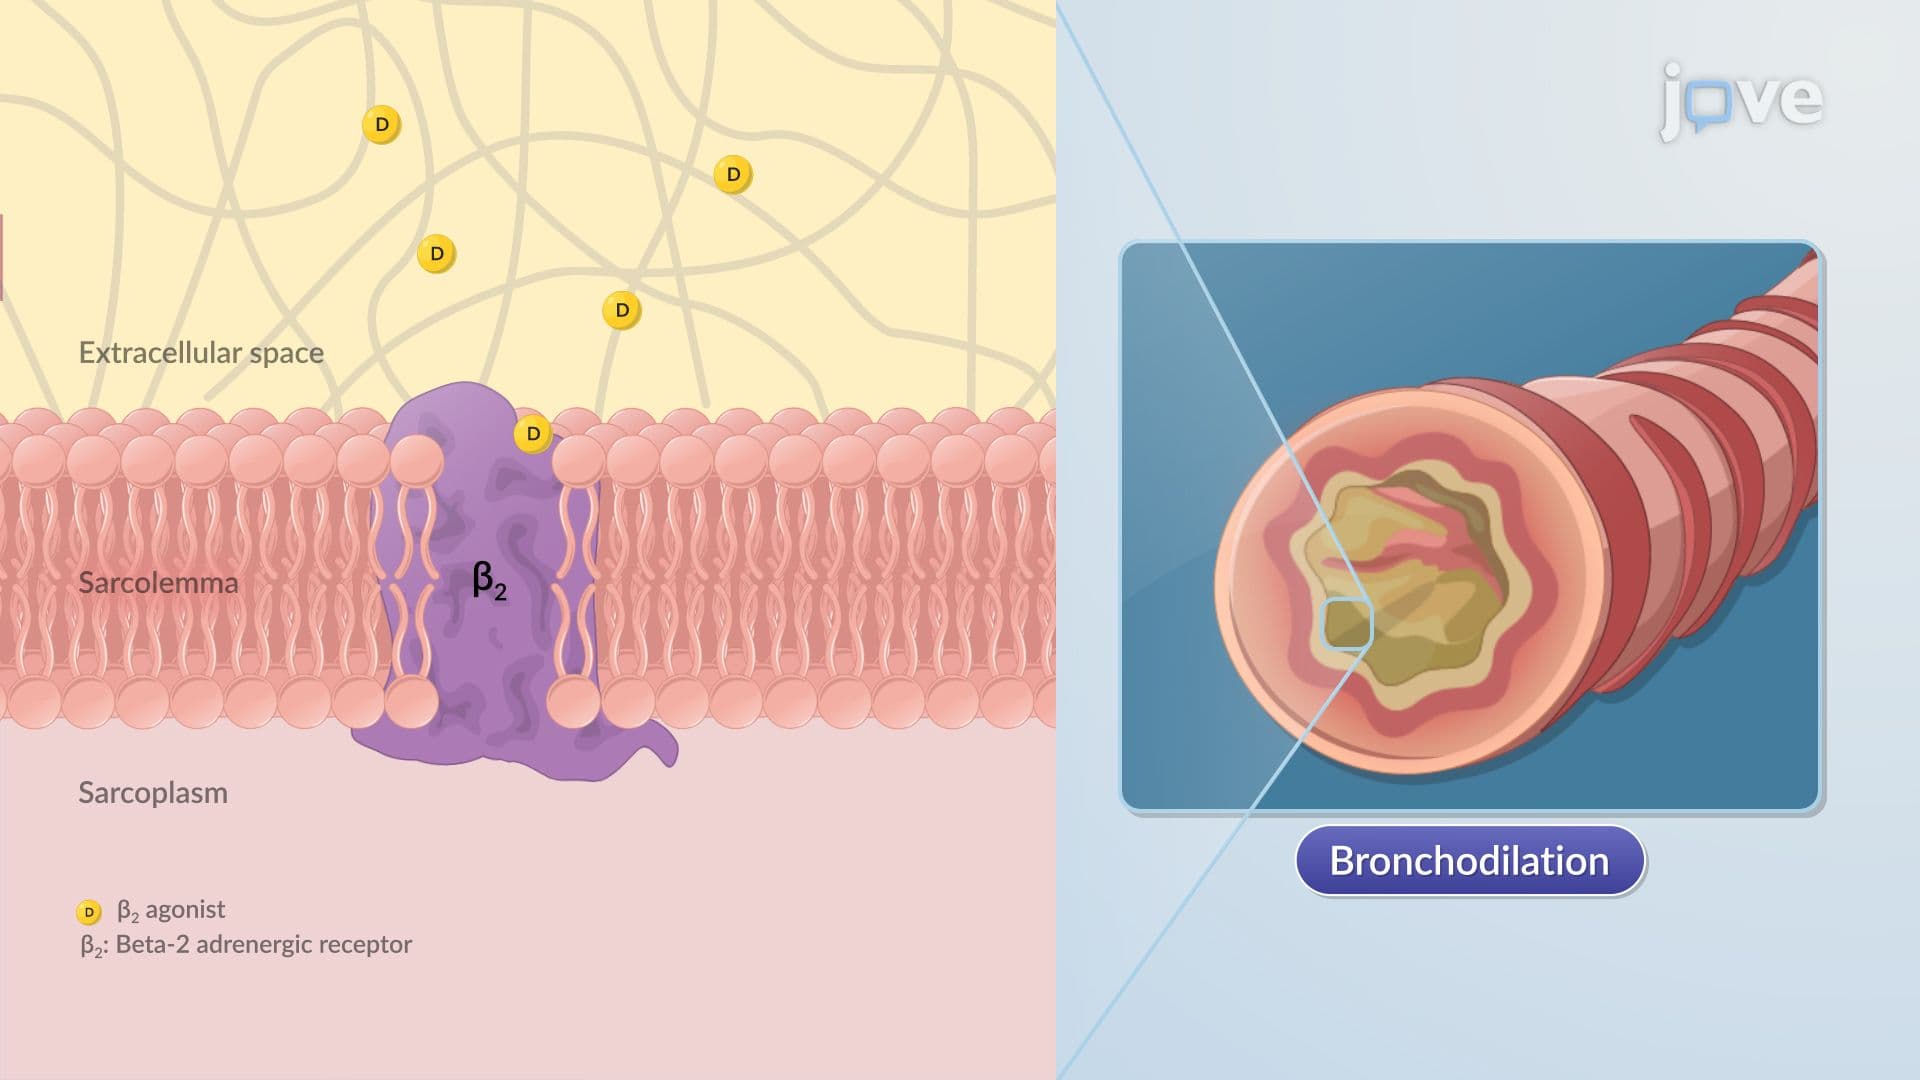
Pharmacodynamic Models: Overview
 01:24
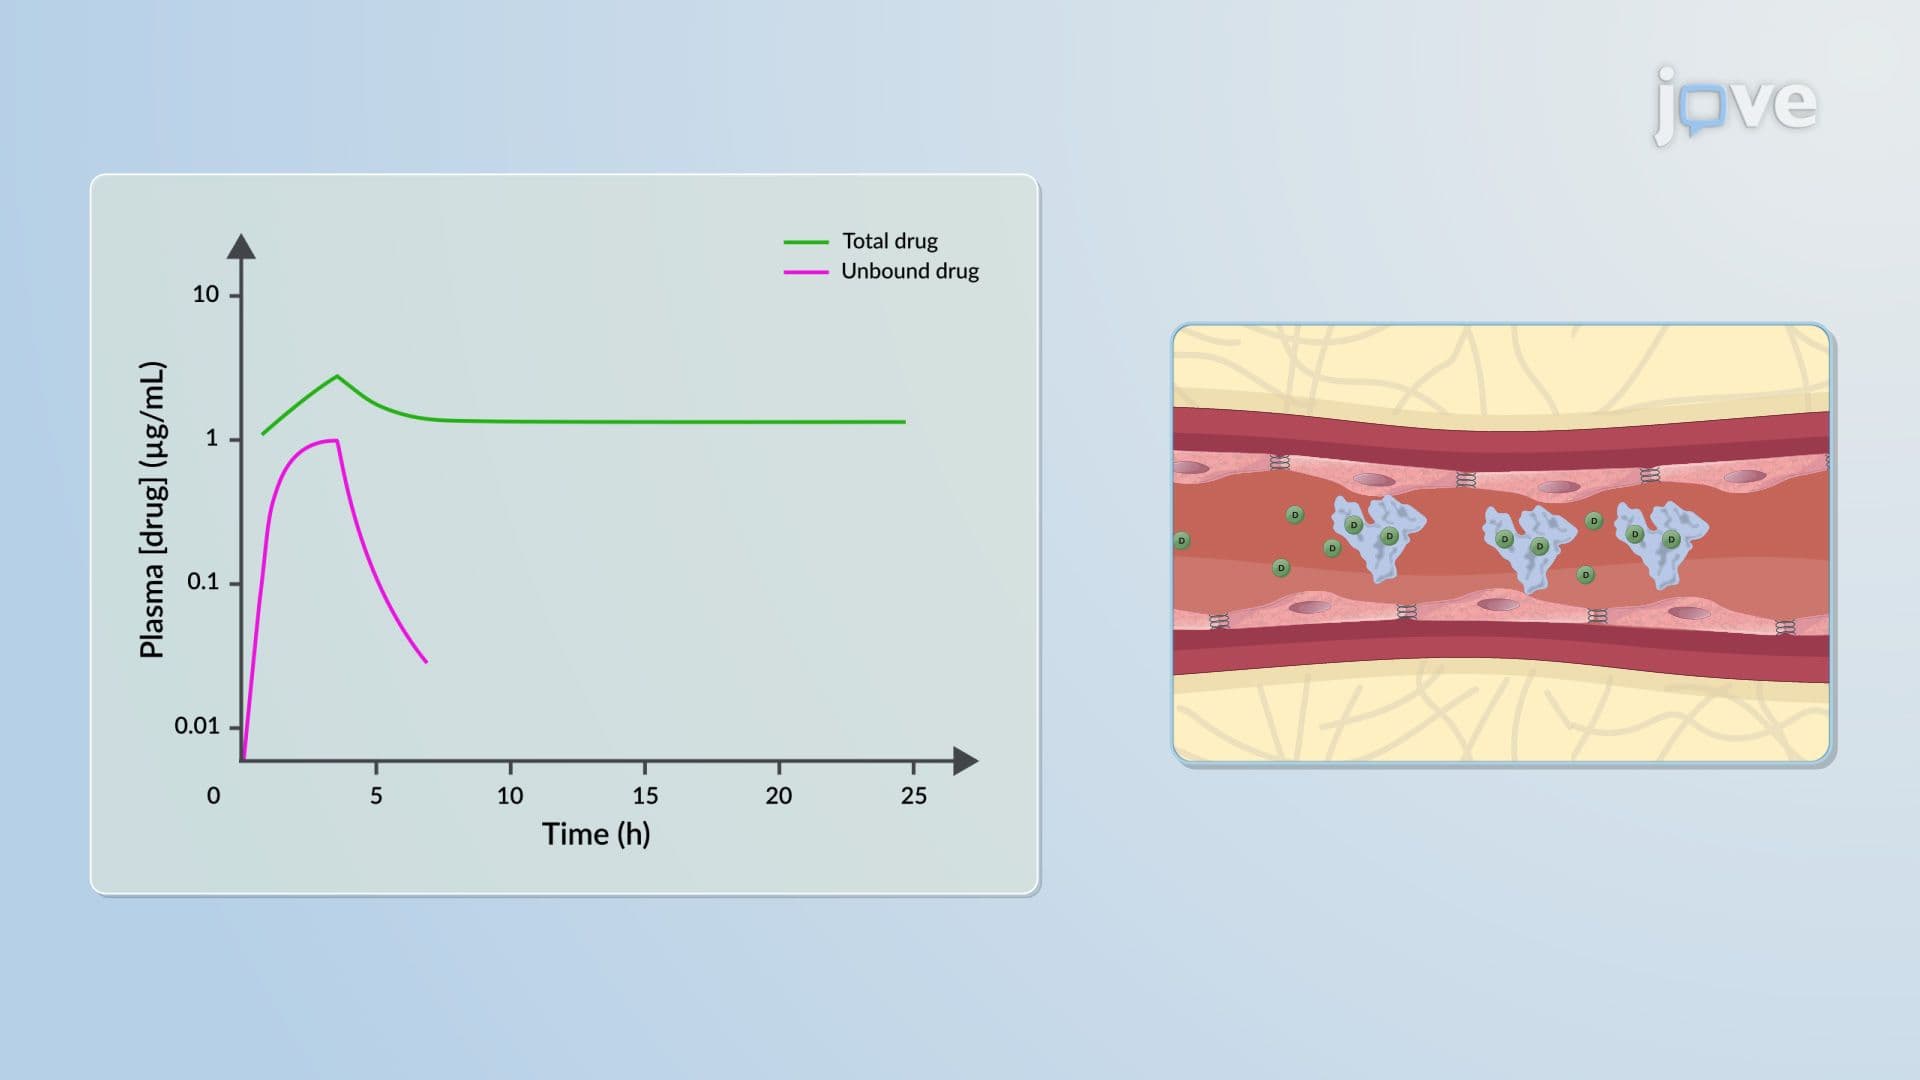
Pharmacokinetic–Pharmacodynamic Relationship: Problems
 01:14
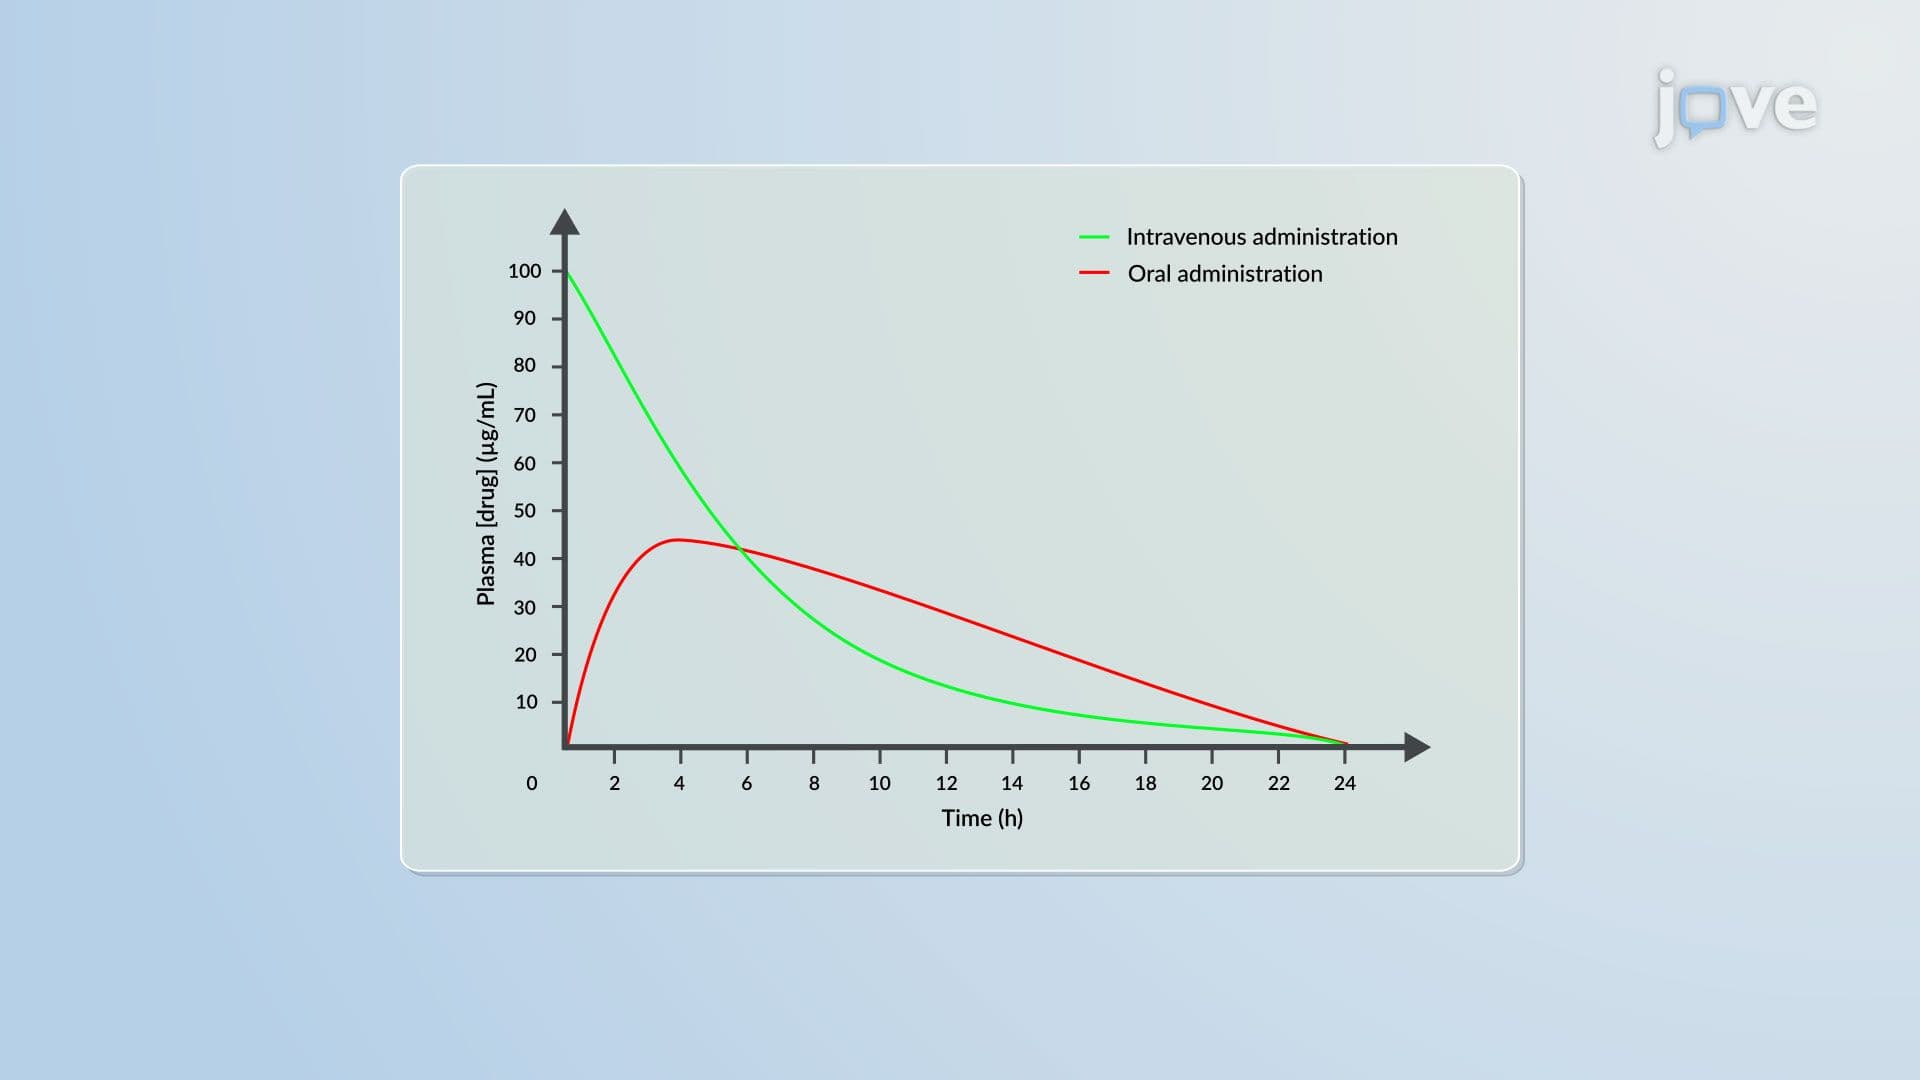
Pharmacokinetic–Pharmacodynamic Relationship: Model Components
 01:28
Renal Drug Excretion: Tubular Secretion