Related Experiment Video
Updated: Mar 20, 2026
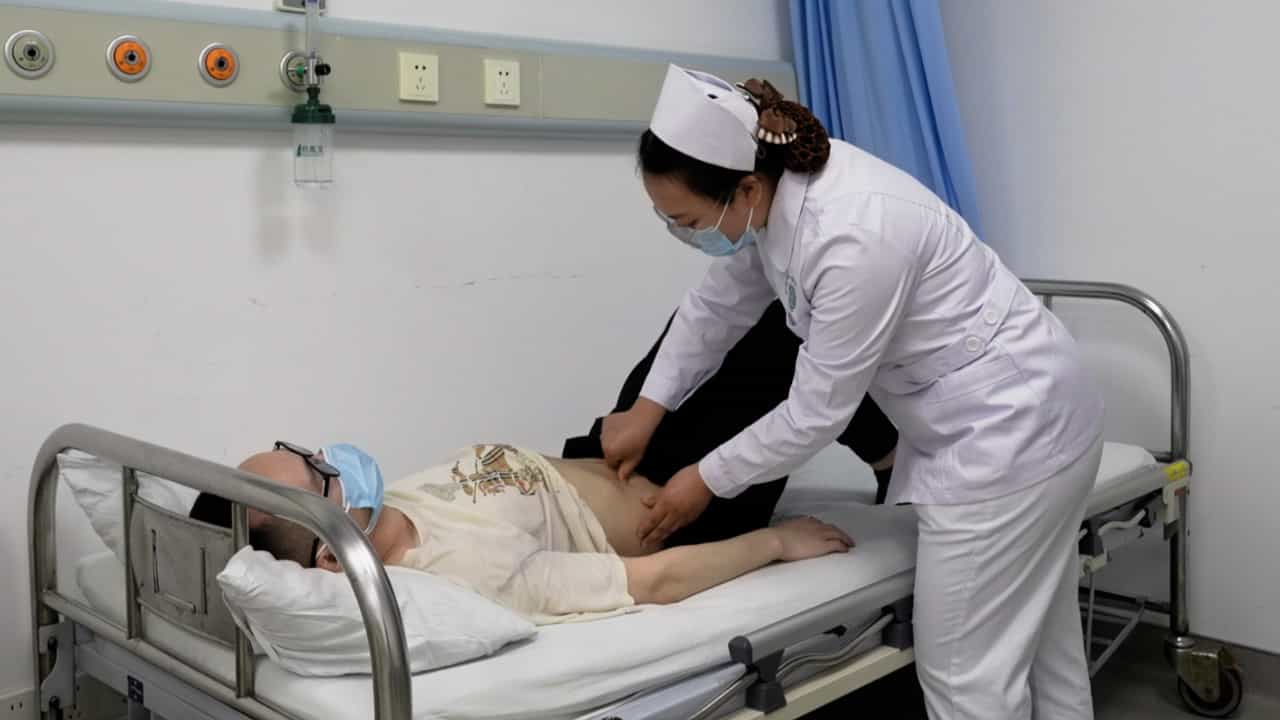

Acupoint Application Combined with Acupoint Massage for Treating Constipation in a Patient with Chronic Obstructive Pulmonary Disease
Published on: August 18, 2023
Chronic Constipation and Constipation-Predominant IBS: Separate and Distinct Disorders or a Spectrum of Disease?
Kewin T H Siah1, Reuben K Wong1, William E Whitehead1
1Dr Siah is an associate consultant in the Division of Gastroenterology and Hepatology at the University Medicine Cluster at National University Hospital and Yong Loo Lin School of Medicine at the National University of Singapore in Kent Ridge, Singapore. Dr Wong is an adjunct associate professor of medicine at Yong Loo Lin School of Medicine at the National University of Singapore. Dr Whitehead is a professor of medicine, adjunct professor of obstetrics and gynecology, and director of the Center for Functional Gastrointestinal and Motility Disorders at the University of North Carolina at Chapel Hill in Chapel Hill, North Carolina.

Abstract:
Rome III diagnostic criteria separate patients with idiopathic chronic constipation into mutually exclusive categories of constipation-predominant irritable bowel syndrome (IBS-C) or functional constipation (FC). However, several experts think that these conditions are not different disorders, but parts of a continuum. To shed light on this issue, we examined studies that compared IBS-C with FC with respect to symptoms, pathophysiologic mechanisms, and treatment response. When the Rome III requirement that patients meeting criteria for IBS cannot also be given a diagnosis of FC is suspended, most patients meet criteria for both, and, contrary to expectation, IBS-C patients have more symptoms of constipation than patients with FC. No symptoms reliably separate IBS-C from FC. Physiologic tests are not reliably associated with diagnosis, but visceral pain hypersensitivity tends to be more strongly associated with IBS-C than with FC, and delayed colonic transit tends to be more common in FC. Although some treatments are effective for both IBS-C and FC, such as prosecretory agents, other treatments are specific to IBS-C (eg, antidepressants, antispasmodics, cognitive behavior therapy) or FC (eg, prucalopride, biofeedback). Future studies should permit IBS-C and FC diagnoses to overlap. Physiologic tests comparing these disorders should include visceral pain sensitivity, colonic transit time, time to evacuate a water-filled balloon, and anal pressures or electromyographic activity from the anal canal. To date, differential responses to treatment provide the strongest evidence that IBS-C and FC may be different disorders, rather than parts of a spectrum.

Related Concept Videos
 01:21
Drugs for Treatment of Constipation-Predominant IBS
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:17
Irritable Bowel Syndrome I: Introduction
IBS is a chronic condition that can persist over a long period or recur frequently.
The pathogenesis of IBS involves a complex interplay of the following factors:
Altered...
 01:17
Drugs for Treatment of Diarrhea-Predominant IBS
Two specific drugs used in the treatment are alosetron (Lotronex) and eluxadoline (Viberzi). Alosetron, a 5-HT3 antagonist, works by slowing the movement of stools in the gut, reducing bowel...
 01:30
Irritable Bowel Syndrome III: Medical and Nursing Management