Related Experiment Video
Updated: Mar 20, 2026
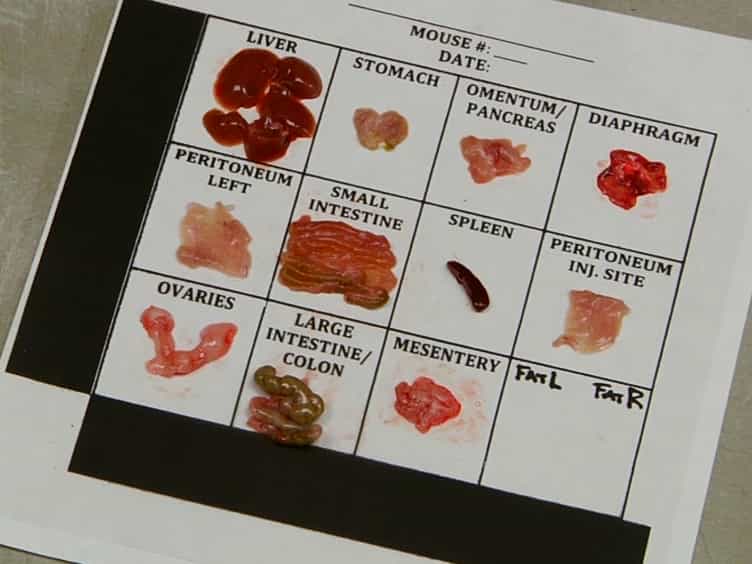

Quantitation of Intra-peritoneal Ovarian Cancer Metastasis
Published on: July 18, 2016
Centralized primary care of advanced ovarian cancer improves complete cytoreduction and survival - A population-based
Pernilla Dahm-Kähler1, Charlotte Palmqvist2, Christian Staf3
1Department of Obstetrics and Gynecology, Sahlgrenska University Hospital, Gothenburg, Sweden; Institute of clinical sciences, Sahlgrenska Academy at University of Gothenburg, Gothenburg, Sweden; Regional Cancer Center Western Sweden, Gothenburg, Sweden.

Objective:
To evaluate centralized primary care of advanced ovarian and fallopian tube cancers in a complete population cohort in relation to complete cytoreduction, time interval from surgery to chemotherapy and relative survival.
Methods:
A regional population-based cohort study of women diagnosed with primary ovarian and fallopian tube cancers and included in the Swedish Quality Registry (SQR) during 2008-2013 in a region where primary care of advanced stages was centralized in 2011. Surgical, oncological characteristics, outcomes, follow-ups and relative survivals were analyzed.
Results:
There were 817 women diagnosed with ovarian and fallopian tube cancers during 2008-2013 and 523 were classified as FIGO stage III-IV and further analyzed. Primary debulking surgery (PDS) was performed in 81% and neoadjuvant chemotherapy (NACT) followed by interval debulking surgery (IDS) in 11%. Complete cytoreduction at PDS was performed in 37% before compared to 49% after centralization (p<0.03). The chemotherapy protocols were identical in the cohorts and they received and completed the planned chemotherapy equally. The time interval between PDS and chemotherapy was 36days (median) before compared to 24days after centralization (p<0.01). The relative 3-year survival rate in women treated by PDS was 44% compared to 65% after centralization and the estimated excess mortality rate ratio (EMRR) was reduced (RR 0.58; 95% CI 0.42-0.79). Comparing the complete cohorts before and after centralization, regardless primary treatment, the relative 3-year survival rate increased from 40% to 61% with reduced EMRR (RR 0.59; 95% CI 0.45-0.76).
Conclusion:
Centralized primary care of advanced ovarian and fallopian tube cancers increases complete cytoreduction, decreases time interval from PDS to chemotherapy and improves relative survival significantly.

Related Concept Videos
 02:56
Treatment Resistant Cancers
02:56Treatment Resistent Cancers